Related Experiment Video
Updated: Jun 20, 2026
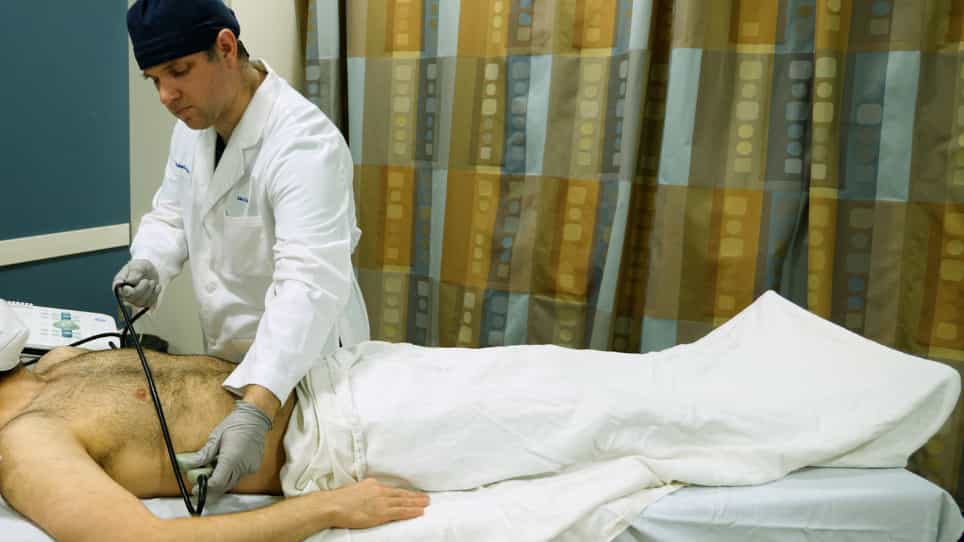
Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Personal health record reach in the Veterans Health Administration: a cross-sectional analysis
Stephanie Leah Shimada1, Cynthia A Brandt, Hua Feng
1Center for Healthcare Organization and Implementation Research / eHealth Quality Enhancement Research Initiative, Edith Nourse Rogers Memorial VA Medical Center, Bedford, MA, United States. stephanie.shimada@va.gov.

Background:
My HealtheVet (MHV) is the personal health record and patient portal developed by the United States Veterans Health Administration (VA). While millions of American veterans have registered for MHV, little is known about how a patient's health status may affect adoption and use of the personal health record.
Objective:
Our aim was to characterize the reach of the VA personal health record by clinical condition.
Methods:
This was a cross-sectional analysis of all veterans nationwide with at least one inpatient admission or two outpatient visits between April 2010 and March 2012. We compared adoption (registration, authentication, opt-in to use secure messaging) and use (prescription refill and secure messaging) of MHV in April 2012 across 18 specific clinical conditions prevalent in and of high priority to the VA. We calculated predicted probabilities of adoption by condition using multivariable logistic regression models adjusting for sociodemographics, comorbidities, and clustering of patients within facilities.
Results:
Among 6,012,875 veterans, 6.20% were women, 61.45% were Caucasian, and 26.31% resided in rural areas. The mean age was 63.3 years. Nationwide, 18.64% had registered for MHV, 11.06% refilled prescriptions via MHV, and 1.91% used secure messaging with their clinical providers. Results from the multivariable regression suggest that patients with HIV, hyperlipidemia, and spinal cord injury had the highest predicted probabilities of adoption, whereas those with schizophrenia/schizoaffective disorder, alcohol or drug abuse, and stroke had the lowest. Variation was observed across diagnoses in actual (unadjusted) adoption and use, with registration rates ranging from 29.19% of patients with traumatic brain injury to 14.18% of those with schizophrenia/schizoaffective disorder. Some of the variation in actual reach can be explained by facility-level differences in MHV adoption and by differences in patients' sociodemographic characteristics (eg, age, race, income) by diagnosis.
Conclusions:
In this phase of early adoption, opportunities are being missed for those with specific medical conditions that require intensive treatment and self-management, which could be greatly supported by functions of a tethered personal health record.


Related Concept Videos
 01:11
Purpose of Health Records I
Here's a breakdown of how health records serve these purposes:
 01:19
Purpose of Health Records II
 01:26
Methods of Documentation II: POMR
 01:30
Methods of Documentation VII: EMR
 01:06
Legal Guidelines for Documentation
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities