Related Experiment Video
Updated: Apr 19, 2026
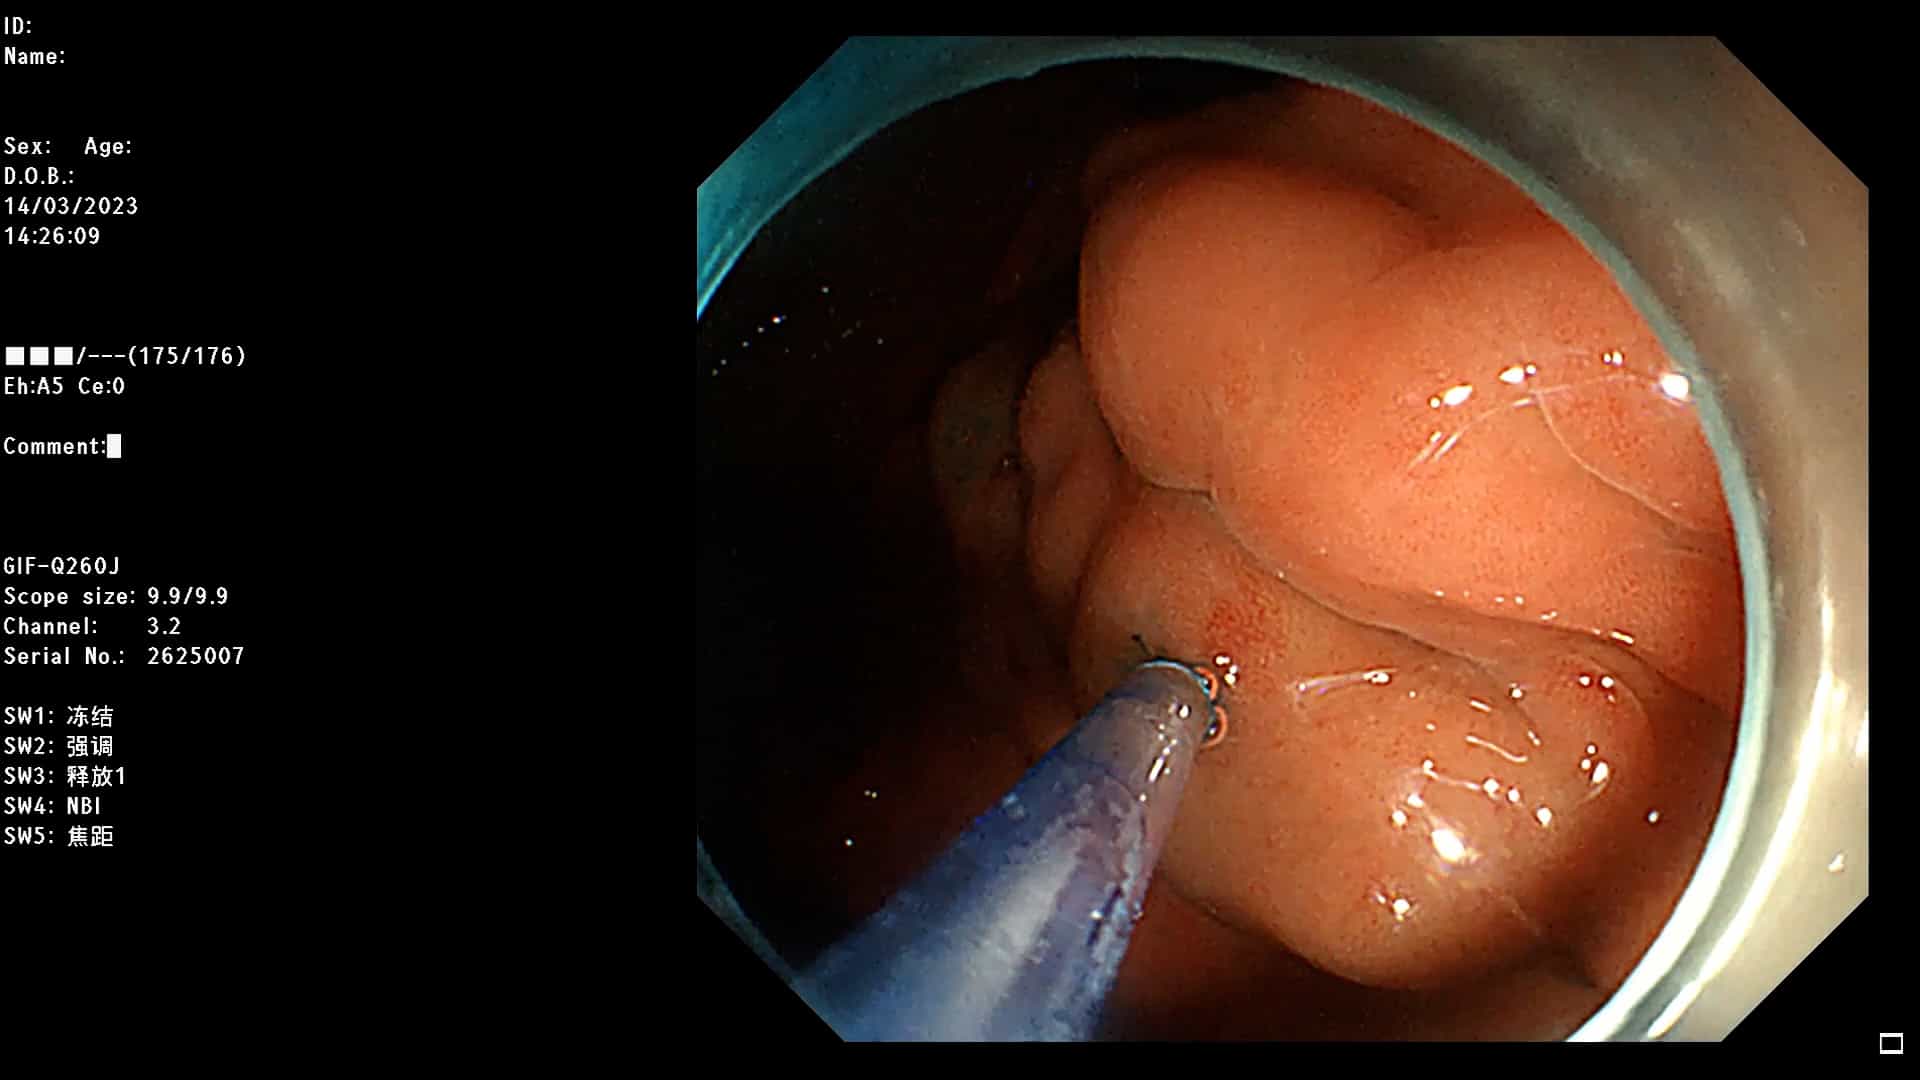
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
[Gastric vascular lesions in cirrhosis: gastropathy and antral vascular ectasia]
Meritxell Casas1, Xavier Calvet2, Mercedes Vergara2
1Servicio de Digestivo, Corporació Sanitària i Universitària Parc Taulí, Sabadell, España; Departament de Medicina, Universitat Autònoma de Barcelona, España.

Insights
Portal hypertensive gastropathy (GHP) and antral vascular ectasia (EVA) are complications of liver cirrhosis. Treatment focuses on bleeding control and reducing portal pressure, with endoscopic therapies often employed.
Area of Science:
- Gastroenterology
- Hepatology
- Internal Medicine
Background:
- Portal hypertensive gastropathy (GHP) and antral vascular ectasia (EVA) are gastrointestinal complications associated with liver cirrhosis and portal hypertension.
- The exact pathogenesis of GHP and EVA remains unclear, though portal hypertension is a key factor in GHP development.
- Clinical presentations range from asymptomatic cases to significant gastrointestinal bleeding and iron deficiency anemia.
Purpose of the Study:
- To review the current understanding of portal hypertensive gastropathy (GHP) and antral vascular ectasia (EVA) in liver cirrhosis.
- To discuss diagnostic endoscopic findings and differentiate between GHP and EVA.
- To outline current and potential treatment strategies for these conditions.
Main Methods:
- Literature review of studies on portal hypertensive gastropathy and antral vascular ectasia in liver cirrhosis.
- Analysis of endoscopic findings, clinical presentations, and treatment outcomes.
- Synthesis of information regarding medical, endoscopic, and surgical interventions.
Main Results:
- GHP lesions include mosaic patterns and red spots, predominantly in the fundus; EVA lesions are typically red spots in the antrum.
- Treatment for GHP is indicated for bleeding, utilizing drugs to decrease portal pressure (e.g., beta-blockers) and endoscopic ablative treatments (e.g., argon-beam coagulation).
- EVA management involves endoscopic ablative therapy or antrectomy for severe cases, as effective medical therapy is lacking.
Conclusions:
- Portal hypertensive gastropathy and antral vascular ectasia require specific management strategies tailored to bleeding status and location.
- Further research is needed to clarify the role of surgical interventions like TIPS or bypass surgery for GHP.
- Differentiating EVA from GHP often necessitates biopsy, and endoscopic ablation is a primary treatment for both conditions when symptomatic.
Abstract:
Portal hypertensive gastropathy (GHP) is a complication of portal hypertension usually associated with liver cirrhosis. The pathogenesis is unclear but the presence of portal hypertension is an essential factor for its development. GHP may be asymptomatic or present as gastrointestinal bleeding or iron deficiency anemia. Endoscopic lesions vary from a mosaic pattern to diffuse red spots; the most common location is the fundus. Treatment is indicated when there is acute or chronic bleeding, as secondary prophylaxis. There is insufficient evidence to recommend primary prophylaxis in patients who have never bled. Drugs that decrease portal pressure, such as non-cardioselective beta-blockers, and/or endoscopic ablative treatments, such as argon-beam coagulation, may be used. The role of transarterial intrahepatic portosystemic shunt) or bypass surgery has been insufficiently analyzed. Antral vascular ectasia (EVA) is a rare entity in liver cirrhosis, whose pathophysiology is still unknown. Clinical presentation is similar to that of GHP and endoscopy usually shows red spots in the antrum. Biopsy is often required to differentiate EVA from GHP. There is no effective medical therapy, so endoscopic ablative therapy and, in severe cases, antrectomy are recommended.
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:22
Portal Hypertension
 01:23
Cirrhosis I: Introduction
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...