Related Experiment Video
Updated: Apr 19, 2026


Ex Vivo Porcine Experimental Model for Studying and Teaching Lung Mechanics
Published on: April 19, 2024
Changes in lung volume and ventilation following transition from invasive to noninvasive respiratory support and
Pauline S van der Burg1, Martijn Miedema1, Frans H de Jongh1
1Department of Neonatology, Emma Children's Hospital, Academic Medical Center, Amsterdam, The Netherlands.

Insights
Extubating preterm infants and placing them in the prone position helps maintain end-expiratory lung volume (EELV) and increase tidal volume (VT). Prone positioning further improves EELV and shifts ventilation to the ventral lung regions, suggesting its benefit after extubation.
Area of Science:
- Neonatal Medicine
- Pediatric Pulmonology
- Respiratory Physiology
Background:
- Minimizing lung injury in ventilated preterm infants involves early extubation.
- Prone positioning is often used to enhance extubation success.
- The impact of extubation and prone positioning on lung volumes in preterm infants was previously unknown.
Purpose of the Study:
- To investigate the effects of transitioning from endotracheal to nasal continuous positive airway pressure (CPAP) on lung volumes.
- To determine the impact of subsequent prone positioning on lung volumes and ventilation distribution.
- To assess changes in end-expiratory lung volume (EELV) and tidal volume (VT) post-extubation and with prone positioning.
Main Methods:
- Electrical impedance tomography (EIT) was used to monitor EELV, VT, and ventilation distribution during the transition to nasal CPAP and after prone positioning.
- Continuous distending pressure (CDP) and fraction of inspired oxygen (FiO₂) were recorded.
- The study included 20 preterm infants with a gestational age of 28.7 ± 1.7 weeks.
Main Results:
- Following extubation, CDP decreased, while EELV and VT significantly increased without altering ventilation distribution.
- Prone positioning led to a further increase in EELV and a decrease in respiratory rate.
- Tidal volume distribution shifted towards ventral lung regions with prone positioning.
Conclusions:
- Preterm infants can maintain EELV and increase VT when transitioned to noninvasive respiratory support.
- Prone positioning enhances EELV and promotes ventral lung ventilation.
- Prone positioning is recommended for preterm infants after extubation to optimize lung function.
Background:
To minimize secondary lung injury, ventilated preterm infants are extubated as soon as possible. To maximize extubation success, they are often placed in prone position. The effect of extubation and subsequent prone positioning on lung volumes is currently unknown.
Methods:
Changes in end-expiratory lung volume (ΔEELV), tidal volume (VT), and ventilation distribution were monitored during transition from endotracheal to nasal continuous positive airway pressure and following prone positioning using electrical impedance tomography. In addition, the continuous distending pressure (CDP) and oxygen need (FiO₂) were recorded.
Results:
Twenty preterm infants (GA 28.7 ± 1.7 wk) were included. Following extubation, the CDP decreased from 7.9 ± 0.5 to 6.0 ± 0.2 cmH₂O, while the FiO₂ remained stable. Both ΔEELV and VT increased significantly (P < 0.05) after extubation, without changing ventilation distribution. Prone positioning resulted in a further increase in ΔEELV (P < 0.01) and a decrease in respiratory rate. VT remained stable but its distribution clearly shifted toward the ventral lung regions.
Conclusion:
Infants who are transitioned from invasive to noninvasive respiratory support are able to maintain their EELV and increase their VT. Prone positioning increases EELV and shifts tidal ventilation to the ventral lung regions. The latter suggests that infants should preferably be placed in prone position after extubation.


Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:15
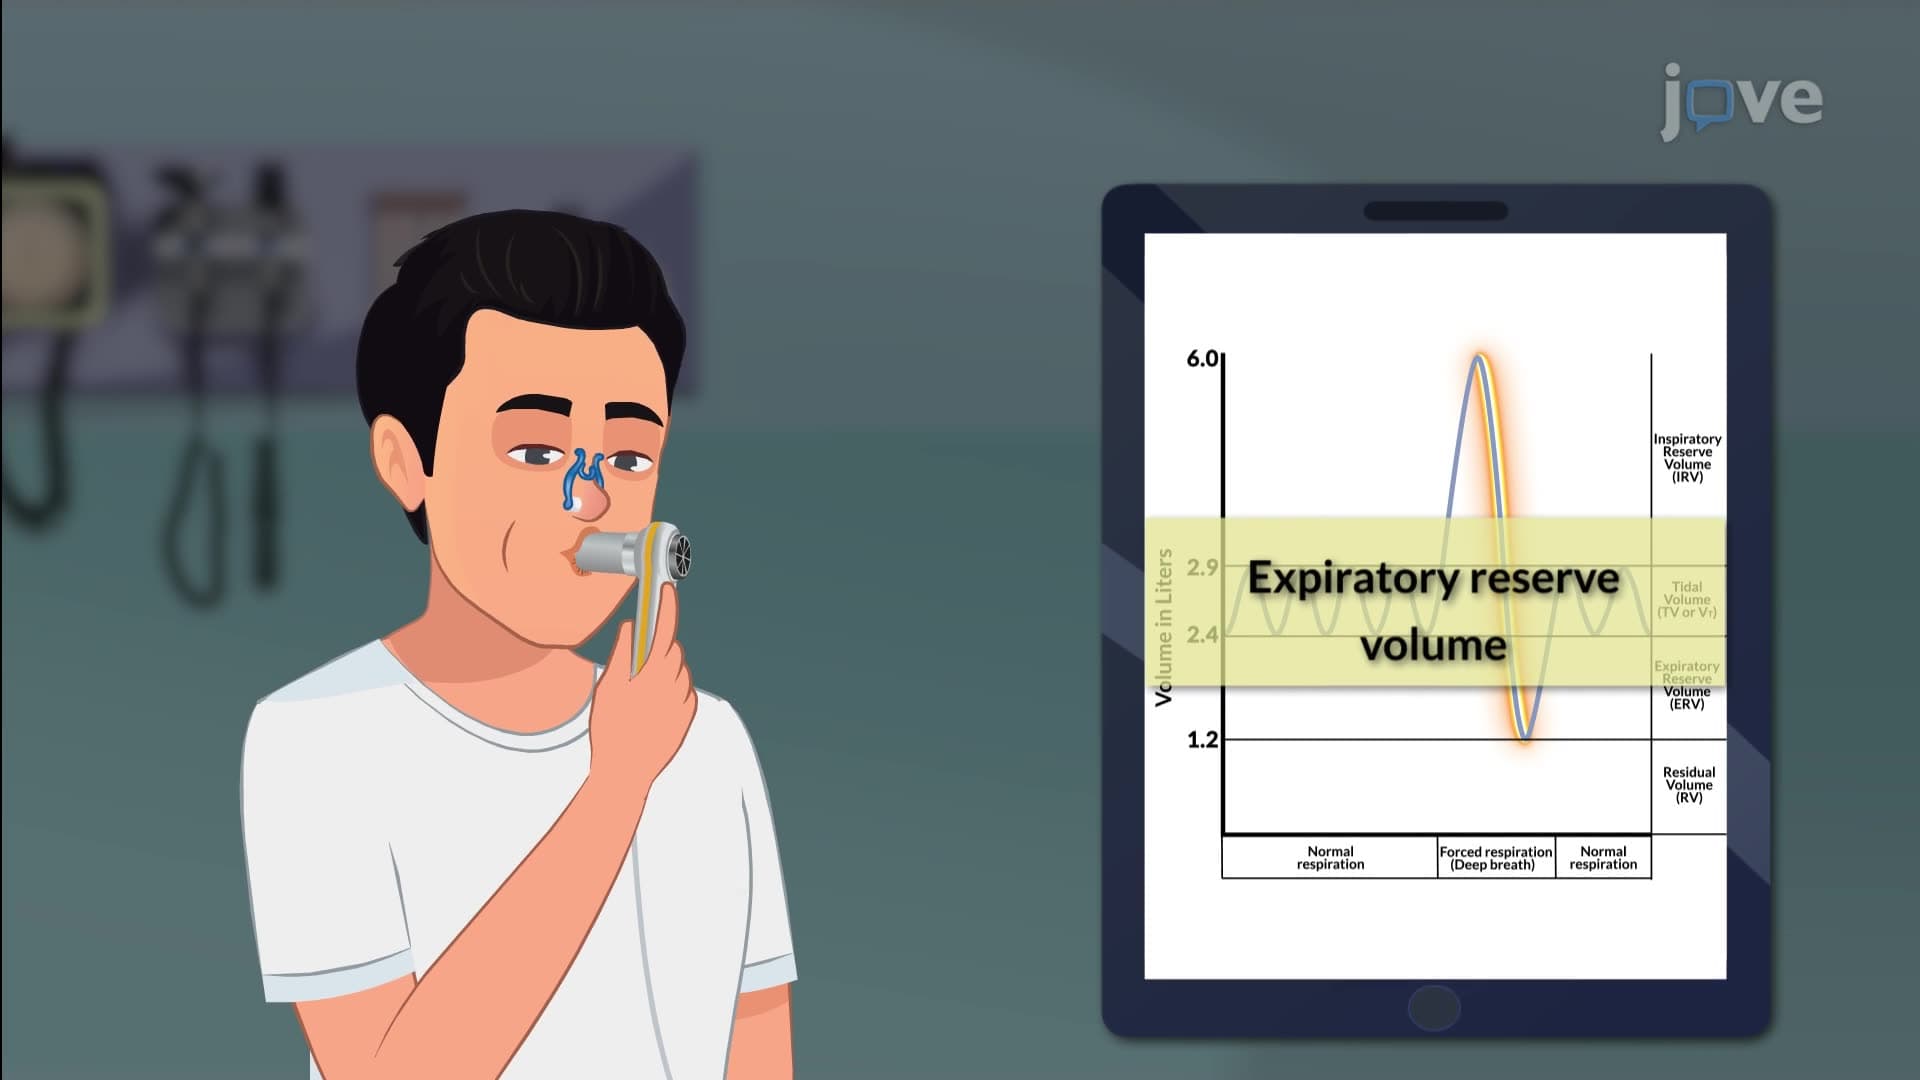
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:24
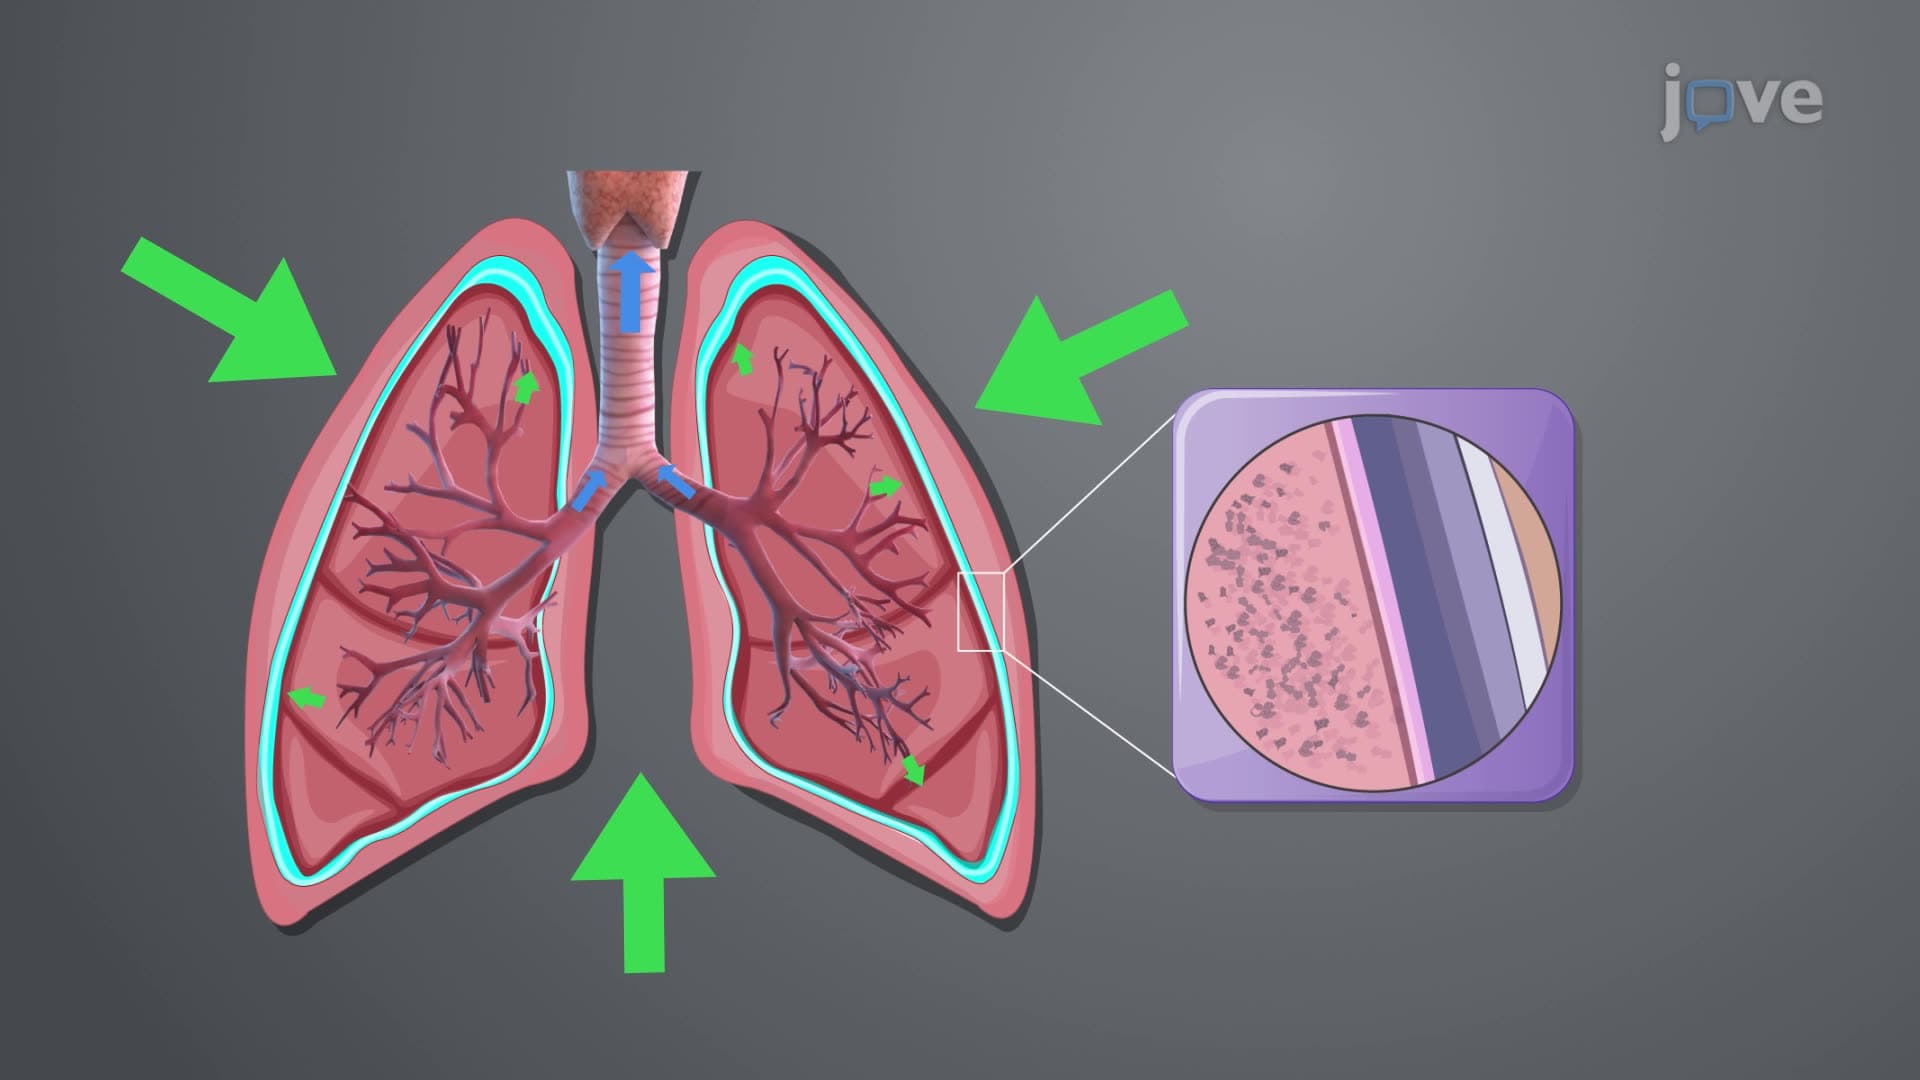
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...