Related Experiment Video
Updated: Apr 19, 2026
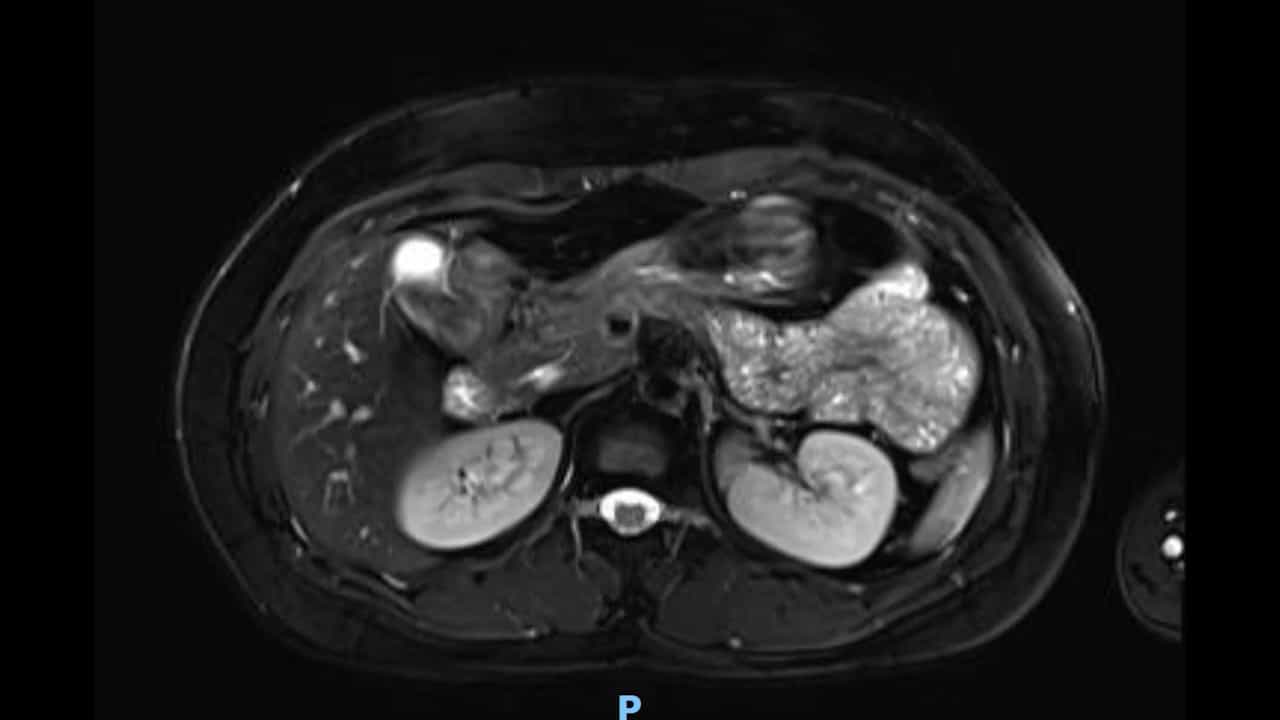

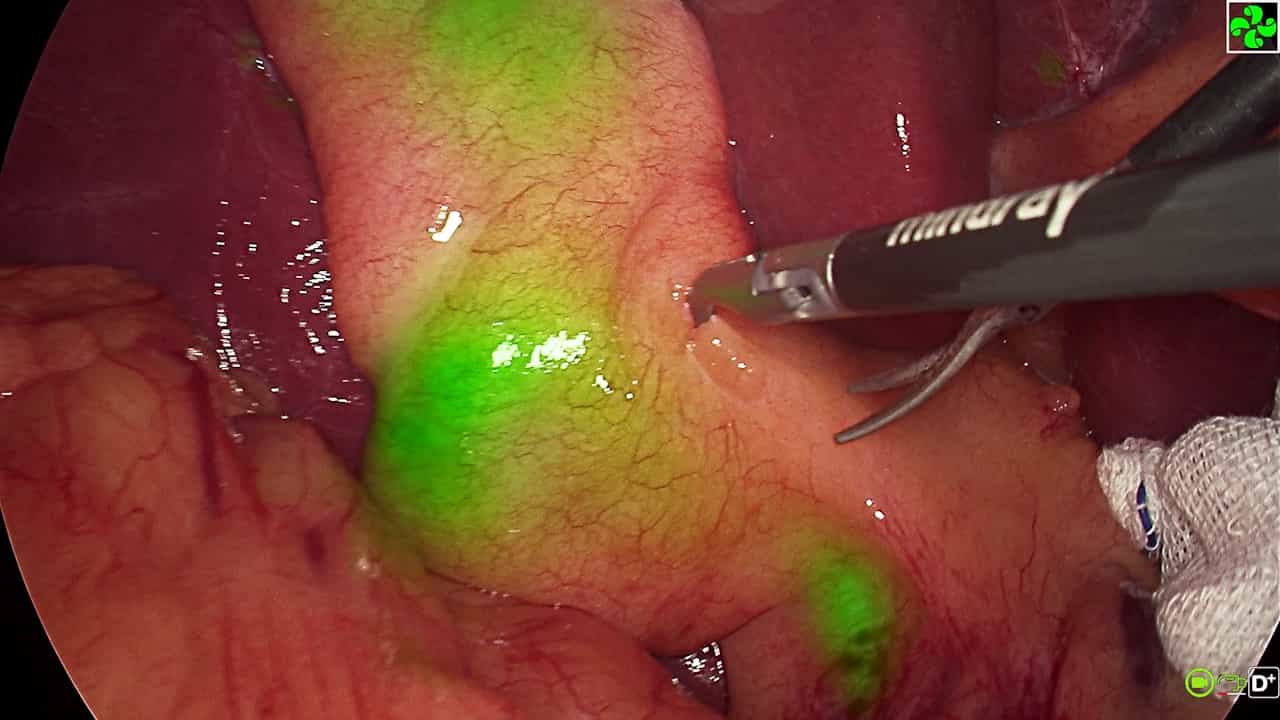
Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Minimally invasive resection of choledochal cyst: a feasible and safe surgical option
Georgios Antonios Margonis1, Gaya Spolverato, Yuhree Kim
1Department of Surgery, The Johns Hopkins University School of Medicine, Baltimore, MD, USA.

Background:
The use of minimally invasive surgery (MIS) for choledochal cyst (CC) has not been well documented. We sought to define the overall utilization and outcomes associated with the use of the open versus MIS approach for CC. We examined the factors associated with receipt of MIS for CC, as well as characterized perioperative and long-term outcomes following open versus MIS for CC.
Methods:
Between 1972 and 2014, a total of 368 patients who underwent resection for CC were identified from an international, multicenter database. A 2:1 propensity score matching was used to create comparable cohorts of patients to assess the effect of MIS on short-term outcomes.
Results:
Three hundred thirty-two patients had an open procedure, whereas 36 patients underwent an MIS approach. Children were more likely to be treated with a MIS approach (children, 24.0 % vs. adults, 2.1 %; P<0.001). Conversely, patients who had any medical comorbidity were less likely to undergo MIS surgery (open, 26.2 % vs. MIS, 2.8 %; P=0.002). In the propensity-matched cohort, MIS resection was associated with decreased length of stay (open, 7 days vs. MIS, 5 days), lower estimated blood loss (open, 50 mL vs. MIS, 17.5 mL), and longer operative time (open, 237 min vs. MIS, 301 min) compared with open surgery (all P<0.05). The overall and degree of complication did not differ between the open (grades I-II, n=13; grades III-IV, n=15) versus MIS (grades I-II, n=5; grades III-IV, n=5) cohorts (P=0.85). Five-year overall survival was 98.6 % (open, 98.0 % vs. MIS, 100.0 %; P=0.45); no patient who underwent MIS developed a subsequent cholangiocarcinoma.
Conclusions:
MIS resection of CC was demonstrated to be a feasible and safe approach with acceptable short-term outcomes in the pediatric population. MIS for benign CC disease was associated with similar perioperative morbidity but a shorter length of stay and a lower blood loss when compared with open resection.
Insights
Minimally invasive surgery (MIS) for choledochal cysts (CC) is safe and feasible, especially in children. MIS offers shorter hospital stays and less blood loss compared to open surgery, with similar complication rates.
Area of Science:
- Surgical Innovation
- Pediatric Surgery
- Gastrointestinal Surgery
Background:
- Minimally invasive surgery (MIS) for choledochal cysts (CC) is not well-documented.
- Limited data exists on the utilization and outcomes of MIS versus open approaches for CC.
- This study aims to define MIS utilization and outcomes for CC.
Purpose of the Study:
- To define the overall utilization of MIS for choledochal cyst (CC) resection.
- To compare perioperative and long-term outcomes of MIS versus open surgery for CC.
- To identify factors associated with the use of MIS for CC.
Main Methods:
- Analysis of 368 patients who underwent CC resection from 1972-2014 in an international multicenter database.
- Utilized 2:1 propensity score matching to create comparable cohorts for outcome assessment.
- Compared outcomes between open and MIS approaches for CC.
Main Results:
- MIS was more common in children (24.0%) than adults (2.1%) and less common in patients with comorbidities.
- In matched cohorts, MIS was associated with shorter length of stay (5 vs. 7 days), lower blood loss (17.5 vs. 50 mL), and longer operative time (301 vs. 237 min).
- No significant difference in complication rates or 5-year survival between MIS and open surgery; no cholangiocarcinoma developed after MIS.
Conclusions:
- Minimally invasive surgery (MIS) is a feasible and safe approach for choledochal cyst (CC) resection, particularly in pediatric patients.
- MIS for benign CC disease shows comparable perioperative morbidity to open resection.
- MIS is associated with reduced length of stay and blood loss compared to open surgery for CC.