Related Experiment Video
Updated: Apr 19, 2026
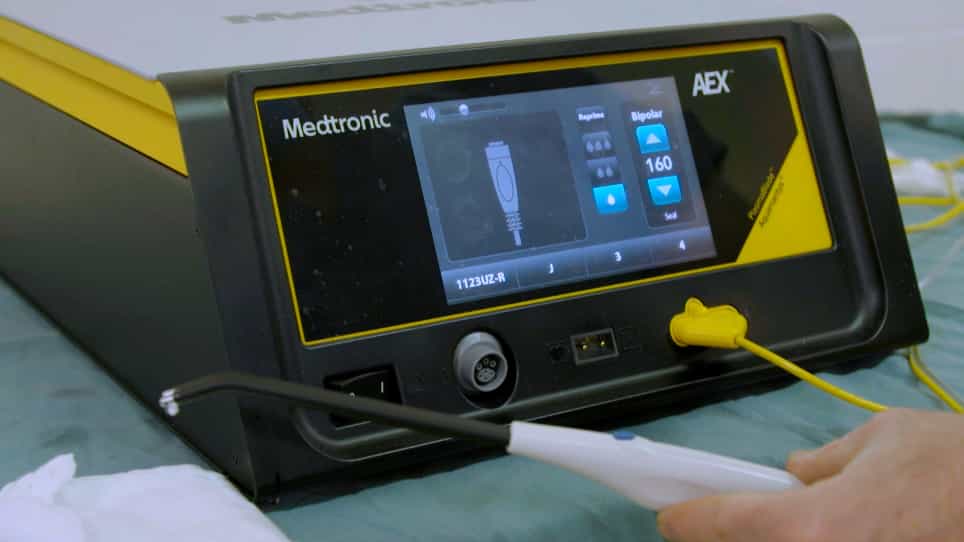
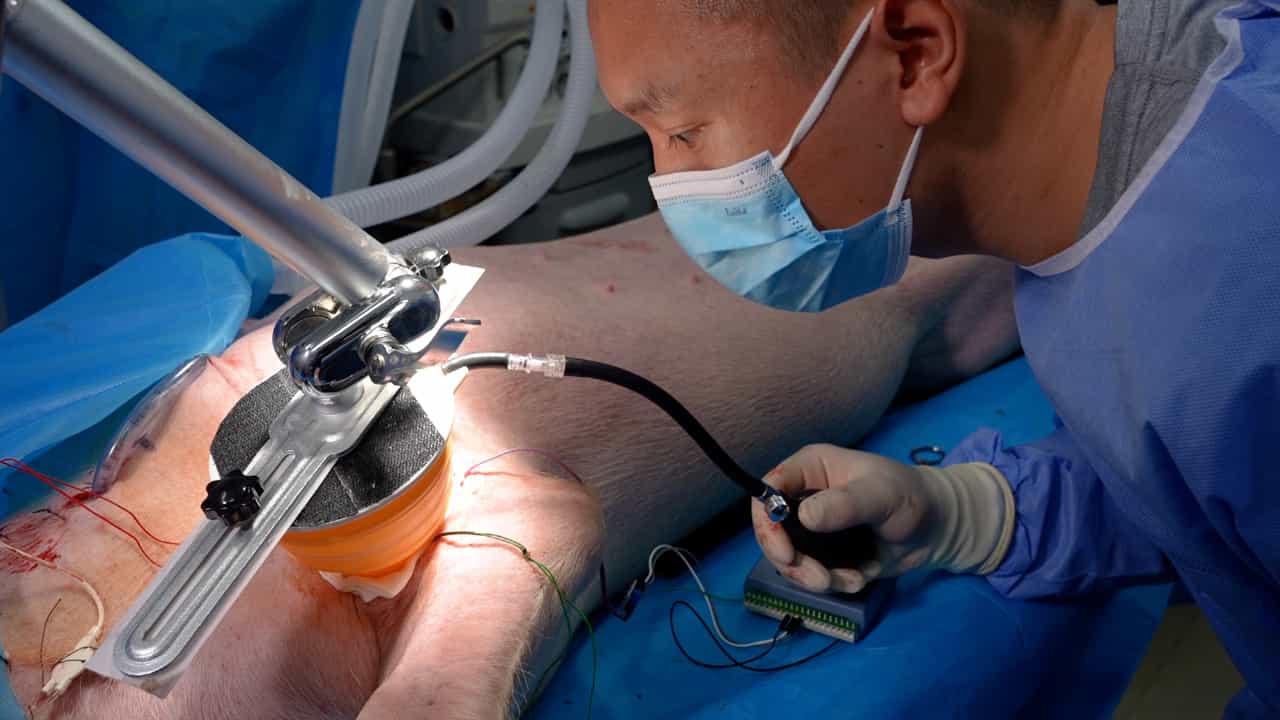
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Traumatic intra-abdominal hemorrhage control: has current technology tipped the balance toward a role for prehospital
Muzzafer Chaudery1, James Clark, Mark H Wilson
1From The Hamlyn Centre for Robotic Surgery (M.C., J.C., G.-Z.Y., A.D.), and Department of Surgery and Cancer (M.H.W., D.B.), Imperial College London; and Department of Trauma Surgery (D.B.), Kings College Hospital NHS Foundation Trust, London, United Kingdom.

Background:
The identification and control of traumatic hemorrhage from the torso remains a major challenge and carries a significant mortality despite the reduction of transfer times. This review examines the current technologies that are available for abdominal hemorrhage control within the prehospital setting and evaluates their effectiveness.
Methods:
A systematic search of online databases was undertaken. Where appropriate, evidence was highlighted using the Oxford levels of clinical evidence. The primary outcome assessed was mortality, and secondary outcomes included blood loss and complications associated with each technique.
Results:
Of 89 studies, 34 met the inclusion criteria, of which 29 were preclinical in vivo trials and 5 were clinical. Techniques were subdivided into mechanical compression, endovascular control, and energy-based hemostatic devices. Gas insufflation and manual pressure techniques had no associated mortalities. There was one mortality with high intensity focused ultrasound. The intra-abdominal infiltration of foam treatment had 64% and the resuscitative endovascular balloon occlusion of the aorta had 74% mortality risk reduction. In the majority of cases, morbidity and blood loss associated with each interventional procedure were less than their respective controls.
Conclusion:
Mortality from traumatic intra-abdominal hemorrhage could be reduced through early intervention at the scene by emerging technology. Manual pressure or the resuscitative endovascular balloon occlusion of the aorta techniques have demonstrated clinical effectiveness for the control of major vessel bleeding, although complications need to be carefully considered before advocating clinical use. At present, fast transfer to the trauma center remains paramount.
Level Of Evidence:
Systematic review, level IV.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:14
Prevention of Further Absorption of Poison
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction