Related Experiment Video
Updated: Apr 19, 2026
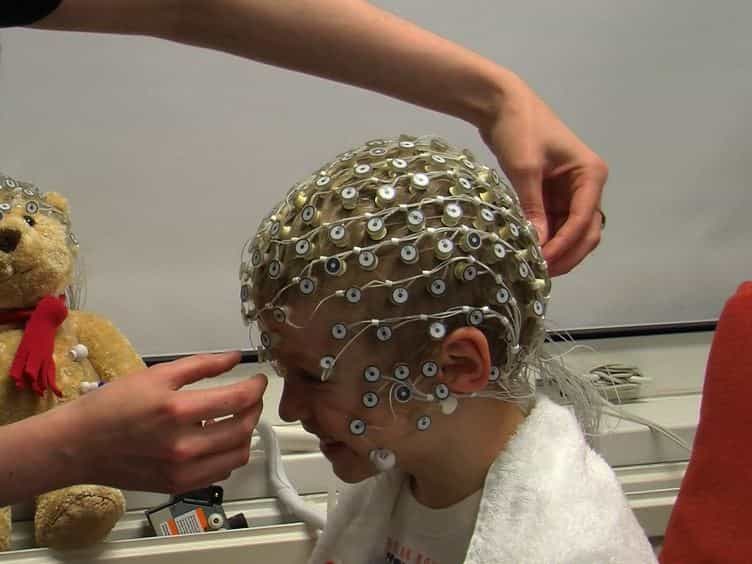
Cortical Source Analysis of High-Density EEG Recordings in Children
Published on: June 30, 2014
Respiratory cortical processing to inspiratory resistances during wakefulness in children with the obstructive sleep
Ignacio E Tapia1, Joseph M McDonough2, Jingtao Huang2
1Sleep Center, The Children's Hospital of Philadelphia, Perelman School of Medicine at the University of Pennsylvania, Philadelphia, Pennsylvania; tapia@email.chop.edu.

Insights
Children with obstructive sleep apnea syndrome (OSAS) show delayed cortical processing of breathing signals while awake. Treatment for OSAS improves this respiratory afferent processing, indicating a reversible neurological effect.
Area of Science:
- Neurology
- Pediatrics
- Sleep Medicine
Background:
- Obstructive sleep apnea syndrome (OSAS) in children is linked to impaired respiratory control during sleep.
- Previous research indicates this impairment persists post-treatment, but its presence during wakefulness and response to treatment remained unclear.
Purpose of the Study:
- To investigate if children with OSAS exhibit abnormal cortical processing of respiratory stimuli during wakefulness.
- To determine if this processing normalizes after OSAS treatment.
Main Methods:
- Respiratory-related evoked potentials (RREP) were measured in children with OSAS and controls during wakefulness.
- RREP were elicited using inspiratory occlusions and resistive loads before and after OSAS treatment (adenotonsillectomy).
Main Results:
- Children with OSAS showed delayed cortical responses (Nf latency) to inspiratory occlusion at baseline compared to controls.
- Following treatment, latencies for resistive loads significantly decreased, and the amplitude of N1 at Cz to occlusion increased.
Conclusions:
- Children with OSAS exhibit partial delays in respiratory afferent cortical processing during wakefulness.
- These processing delays are partially reversible and improve after treatment for OSAS.
Abstract:
Children with the obstructive sleep apnea syndrome (OSAS) have impaired respiratory afferent cortical processing during sleep that persists after treatment of OSAS. However, it is unknown whether this impairment is present during wakefulness and, if so, whether it improves after OSAS treatment. We hypothesized that children with OSAS, during wakefulness, have abnormal cortical processing of respiratory stimuli manifested by blunted respiratory-related evoked potentials (RREP) and that this resolves after OSAS treatment. We measured RREP during wakefulness in 26 controls and 21 children with OSAS before and after treatment. Thirteen participants with OSAS repeated testing 3-6 mo after adenotonsillectomy. RREP were elicited by interruption of inspiration by total occlusion and 30 and 20 cmH2O/l per s resistances. Nf at Fz latency elicited by occlusion was longer in children with OSAS at baseline compared with controls (78.8 ± 24.8 vs. 63.9 ± 19.7 ms, P = 0.05). All other peak amplitudes and latencies were similar between the two groups. After OSAS treatment, Nf at Fz latency elicited by 30 cmH2O/l per s decreased significantly (before, 88 ± 26 vs. after, 71 ± 25 ms, P = 0.02), as did that elicited by 20 cmH2O/l per s (85 ± 27 vs. 72 ± 24 ms, P = 0.004). The amplitude of N1 at Cz elicited by occlusion increased from -3.4 ± 5.6 to -7.4 ± 3 μV (P = 0.049) after treatment. We concluded that children with OSAS have partial delay of respiratory afferent cortical processing during wakefulness that improves after treatment.
Related Concept Videos
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:23
Acute Respiratory Failure-IV
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:25
Hyperpnea and Hyperventilation
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...