Related Experiment Video
Updated: Apr 19, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Fundamental differences in axial and appendicular bone density in stress fractured and uninjured Royal Marine
Trish Davey1, Susan A Lanham-New2, Anneliese M Shaw1
1Institute of Naval Medicine, Alverstoke, Gosport PO12 2DL, UK.

Abstract:
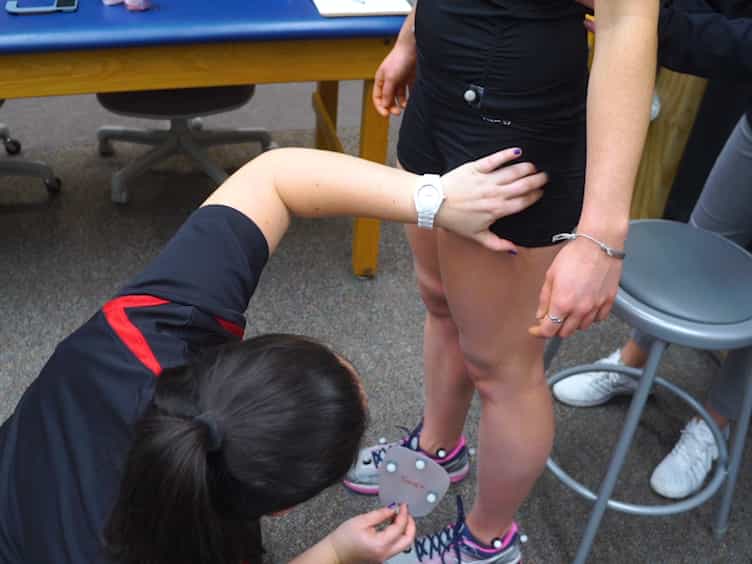
Stress fracture is a common overuse injury within military training, resulting in significant economic losses to the military worldwide. Studies to date have failed to fully identify the bone density and bone structural differences between stress fractured personnel and controls due to inadequate adjustment for key confounding factors; namely age, body size and physical fitness; and poor sample size. The aim of this study was to investigate bone differences between male Royal Marine recruits who suffered a stress fracture during the 32 weeks of training and uninjured control recruits, matched for age, body weight, height and aerobic fitness. A total of 1090 recruits were followed through training and 78 recruits suffered at least one stress fracture. Bone mineral density (BMD) was measured at the lumbar spine (LS), femoral neck (FN) and whole body (WB) using Dual X-ray Absorptiometry in 62 matched pairs; tibial bone parameters were measured using peripheral Quantitative Computer Tomography in 51 matched pairs. Serum C-terminal peptide concentration was measured as a marker of bone resorption at baseline, week-15 and week-32. ANCOVA was used to determine differences between stress fractured recruits and controls. BMD at the LS, WB and FN sites was consistently lower in the stress fracture group (P<0.001). Structural differences between the stress fracture recruits and controls were evident in all slices of the tibia, with the most prominent differences seen at the 38% tibial slice. There was a negative correlation between the bone cross-sectional area and BMD at the 38% tibial slice. There was no difference in serum CTx concentration between stress fracture recruits and matched controls at any stage of training. These results show evidence of fundamental differences in bone mass and structure in stress fracture recruits, and provide useful data on bone risk factor profiles for stress fracture within a healthy military population.

Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:27
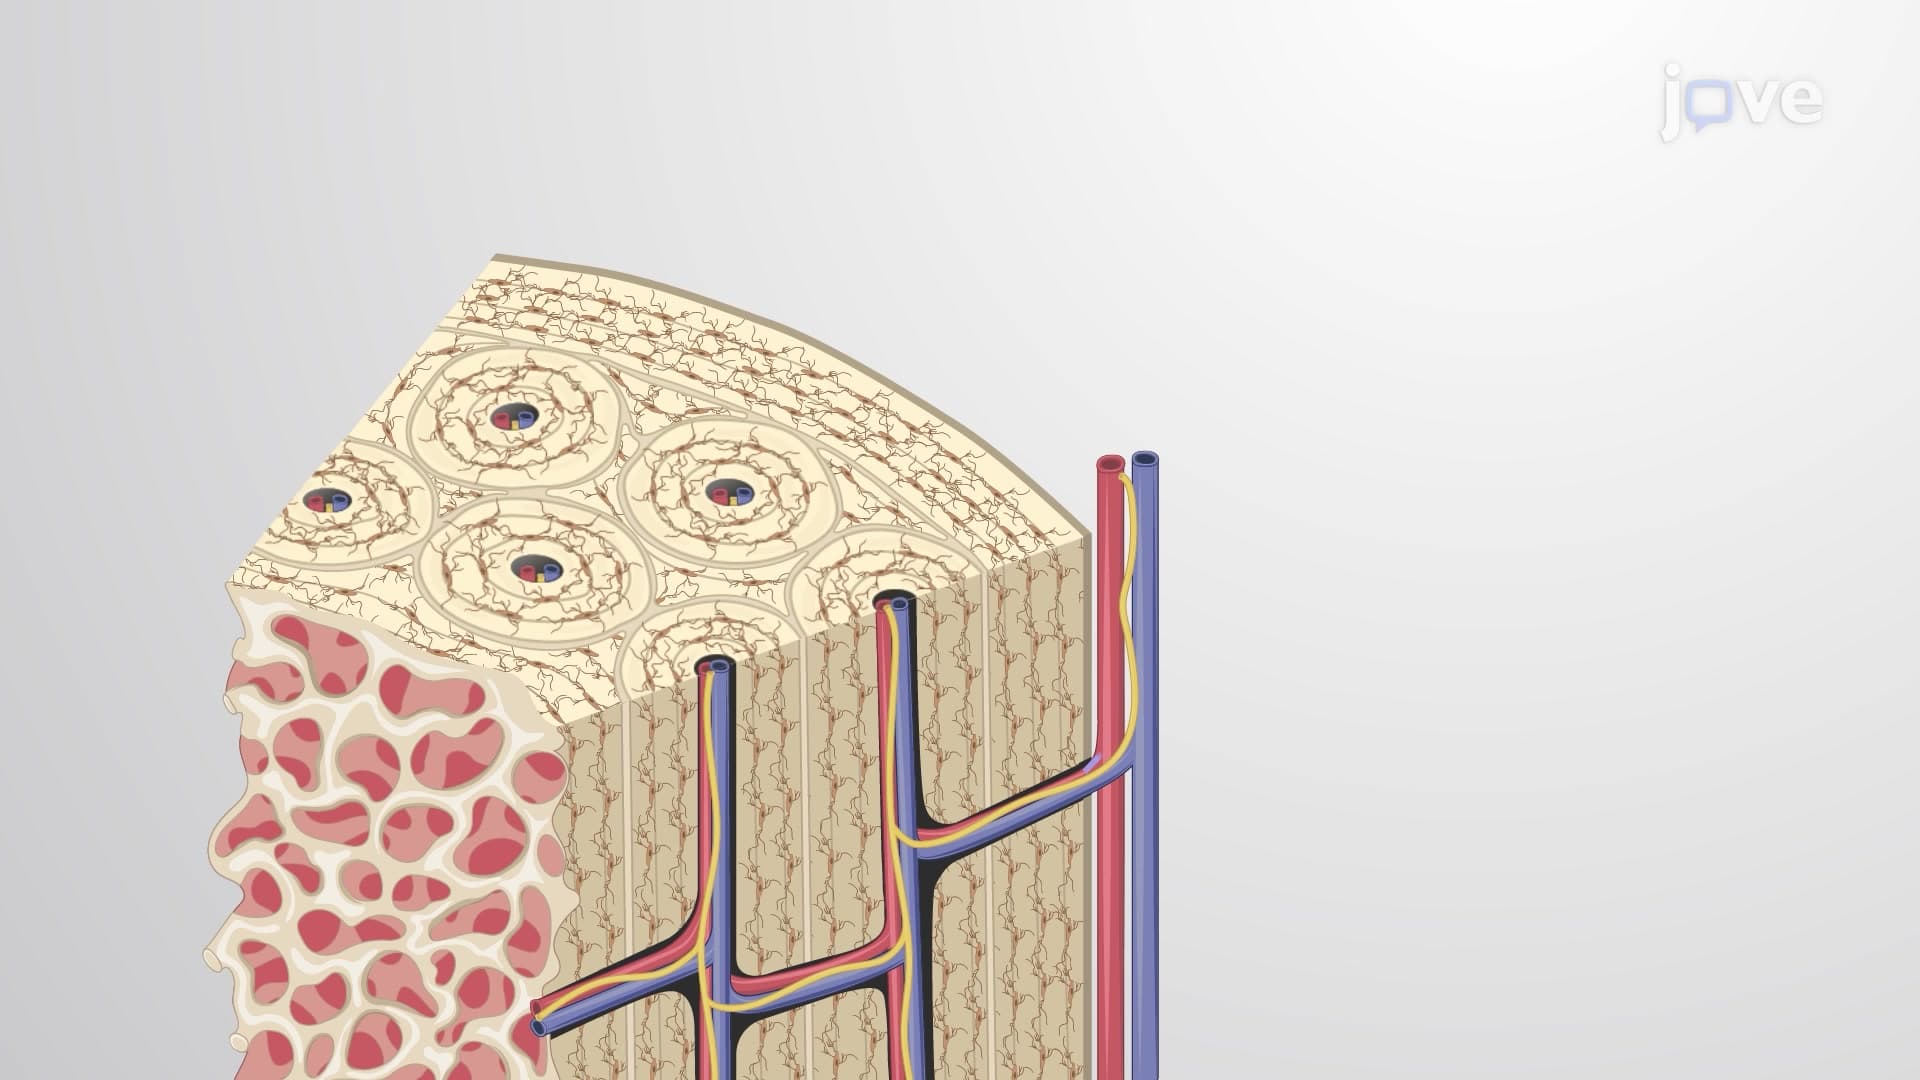
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:09
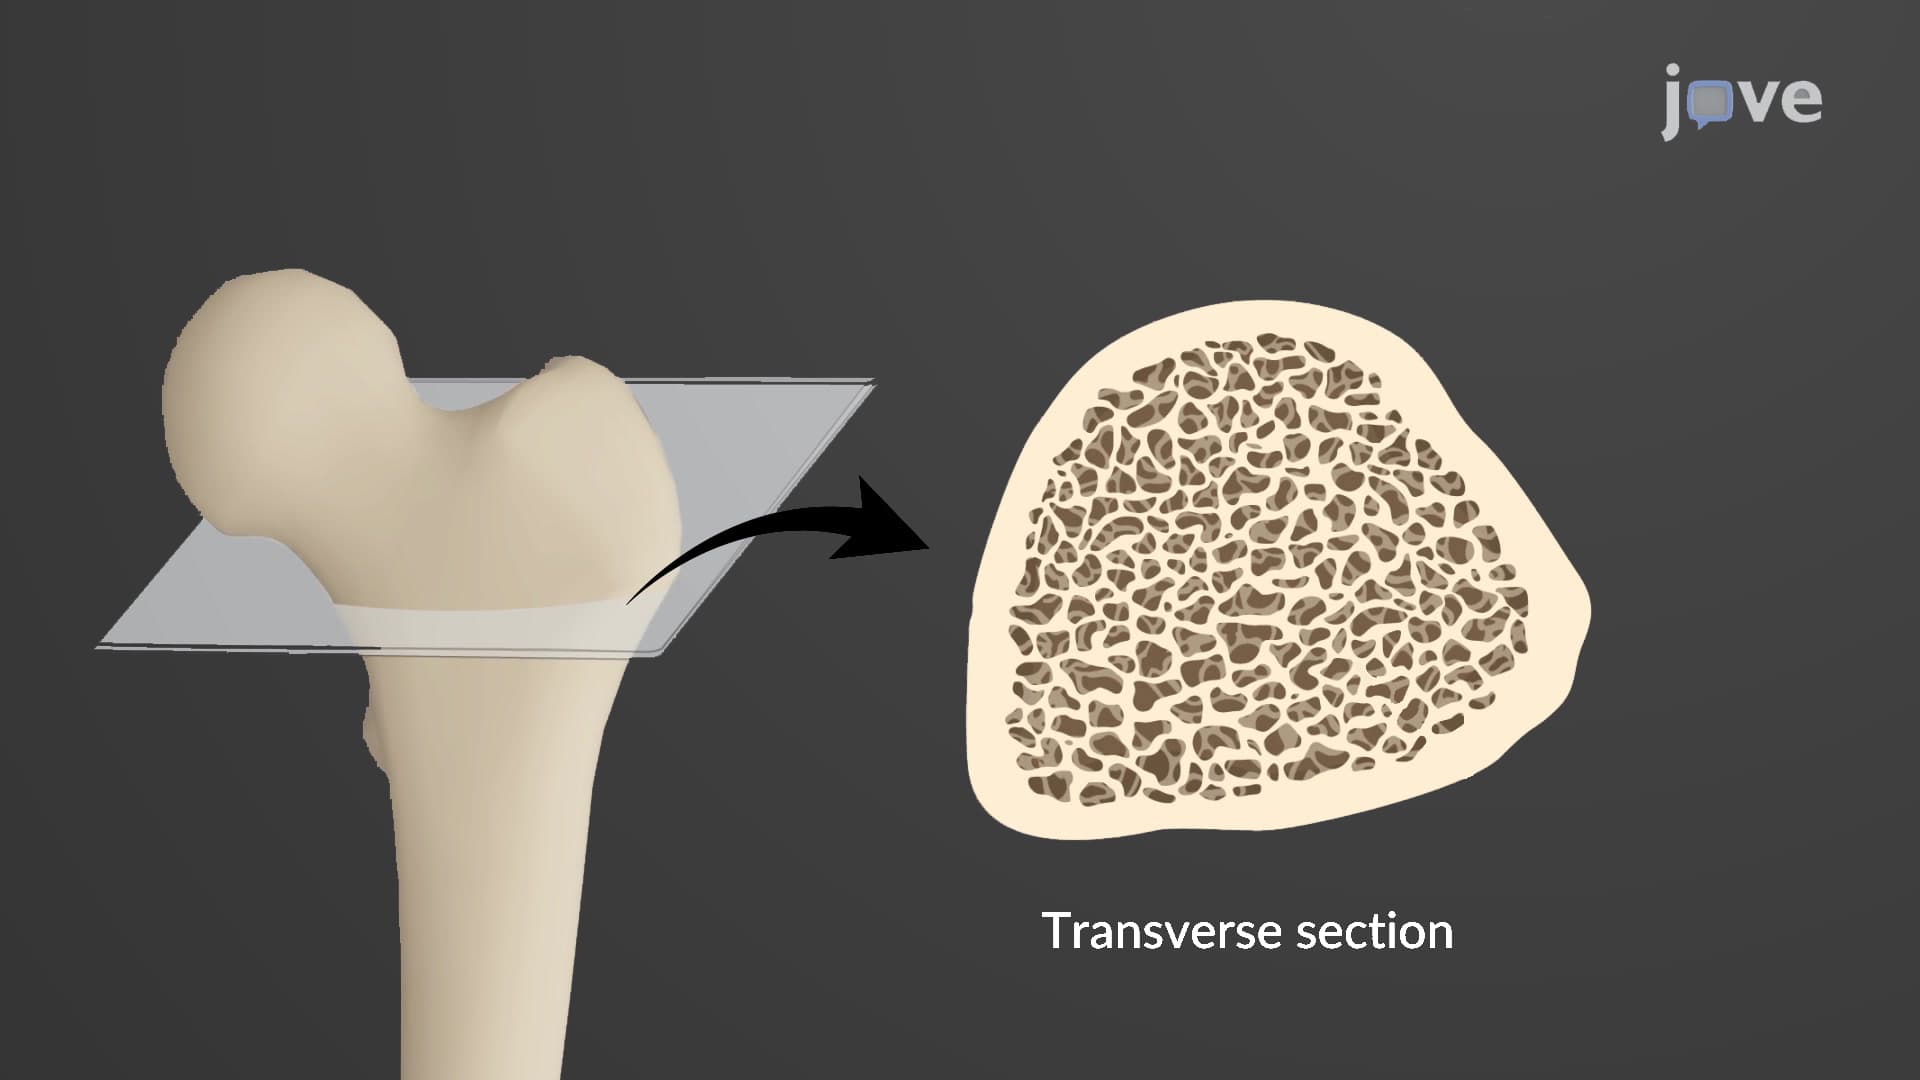
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
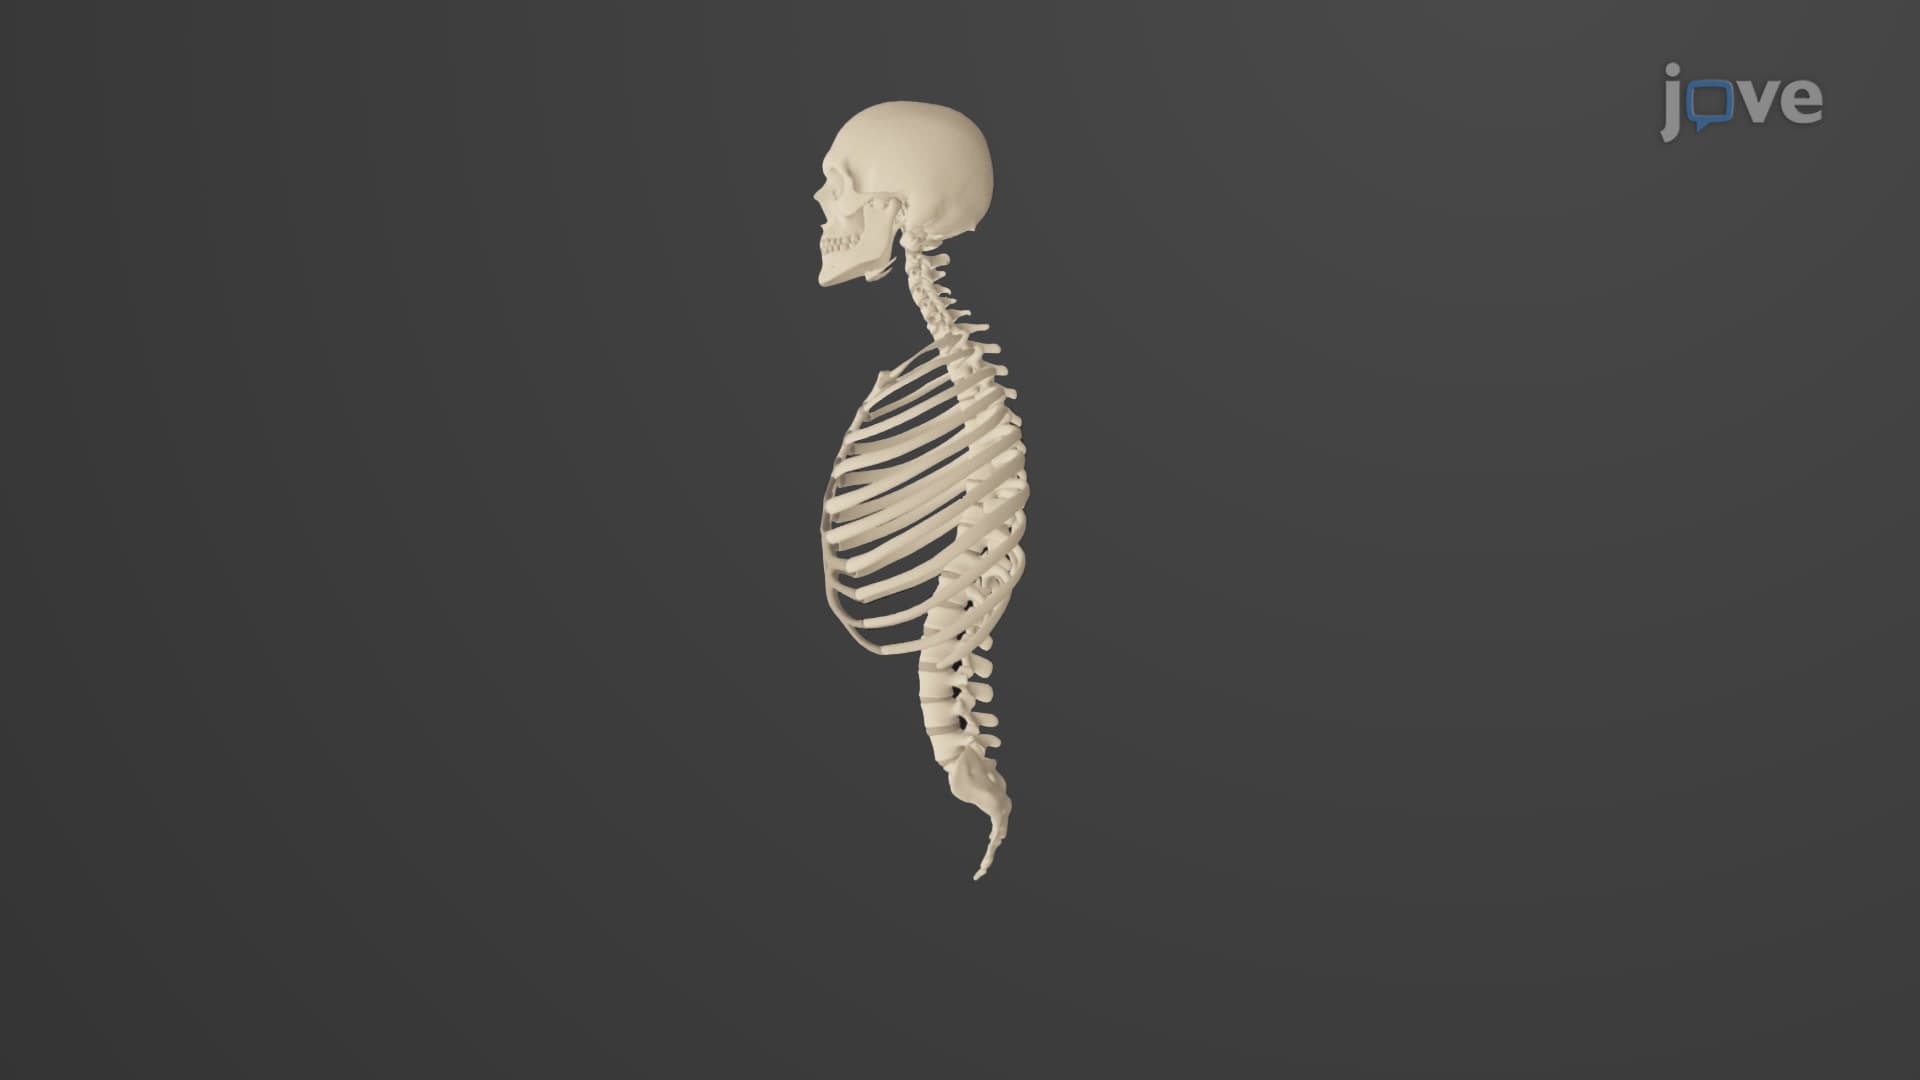
Overview of the Axial Skeleton
The axial skeleton of the...