Related Experiment Video
Updated: Apr 19, 2026
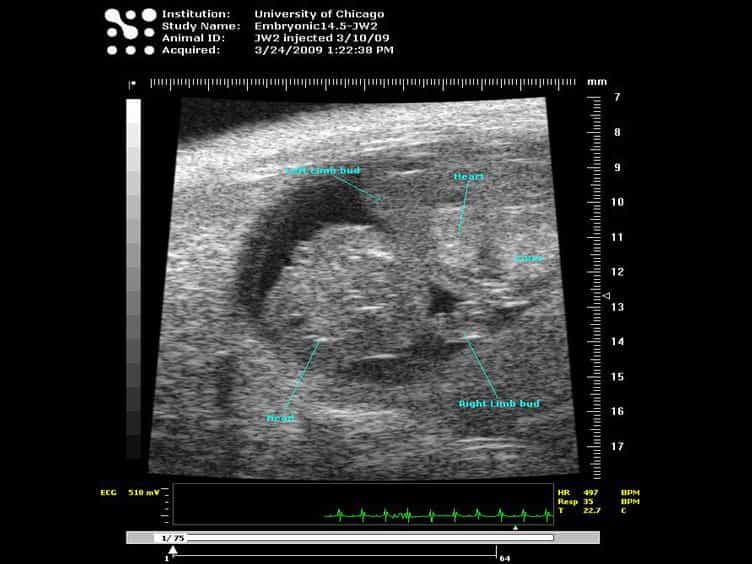

Murine Fetal Echocardiography
Published on: February 15, 2013
Exercises in anatomy: holes between the ventricles
Robert H Anderson1, Anne E Sarwark2, Diane E Spicer3
1Institute of Genetic Medicine, Newcastle University, Newcastle-upon-Tyne, UK.

Insights
Ventricular septal defects (VSDs) are common congenital heart issues. A new classification system considers defect location, phenotypic features, and septal alignment for surgical planning.
Area of Science:
- Cardiac Anatomy
- Congenital Heart Disease
- Surgical Anatomy
Background:
- Ventricular septal defects (VSDs) represent the most frequent congenital cardiac malformations.
- Current classification systems lack consensus, hindering effective surgical planning.
- Understanding the detailed anatomy of the ventricular septum is crucial for VSD categorization.
Purpose of the Study:
- To propose a comprehensive classification for ventricular septal defects.
- To analyze the normal and malformed cardiac anatomy relevant to VSDs.
- To correlate anatomical features with surgical considerations.
Main Methods:
- Detailed analysis of normal cardiac anatomy, focusing on the ventricular septum and its components.
- Examination of malformed hearts to identify VSD locations and characteristics.
- Illustration of phenotypic features and septal malalignment in VSDs.
Main Results:
- The ventricular septum is primarily muscular, with a small membranous portion.
- VSDs can occur centrally, inlet, outlet, or within the apical septum.
- Phenotypic features and septal malalignment provide critical surgical information, especially regarding the conduction axis.
Conclusions:
- A classification integrating geographical location, phenotypic features, and septal malalignment is essential for surgical guidance.
- This approach enhances understanding of VSDs and aids in preoperative planning.
- Accurate anatomical description is key to improving outcomes for congenital cardiac malformations.
Abstract:
Holes between the ventricles are the commonest congenital cardiac malformations. As yet, however, there is no consensus as to how they can best be described and categorized. In this, our third exercise in cardiac anatomy, we address the issue of classification of ventricular septal defects. We begin our demonstration by analysing the normal heart. We show that the larger part of the ventricular septum is made up of its muscular component. The membranous part accounts for only a small portion, which is located centrally within the cardiac base. This small membranous part forms a boundary between the right-sided chambers and the aortic root. Holes at this site, therefore, which account for the commonest defects closed surgically, will open centrally in the cardiac base, being located postero-inferiorly relative to the supraventricular crest. We then show that the larger part of the crest itself is a free-standing muscular sleeve, which lifts the leaflets of the pulmonary valve away from the cardiac base. Only a very small part of the muscle forming the right ventricular outlet is located in the septal position. Turning our attention to malformed hearts, we show how holes between the ventricles can open centrally at the cardiac base, open to the inlet or outlet of the right ventricle or open within the substance of the apical muscular septum. We demonstrate, however, that description of such geographical location of the defects does not paint the full picture, since lesions with markedly different phenotypic features can open in comparable geographic locations. We illustrate how it is the phenotypic features, as seen from the right ventricle, which convey the crucial information for the surgeon with regard to the location of the atrioventricular conduction axis, using hearts with holes opening to the inlet of the right ventricle with muscular as opposed to partially fibrous borders to emphasize this point. We continue by showing how holes with different phenotypes can also open to the outlet of the right ventricle, the key feature in this regard being malalignment between the apical muscular septum relative to the muscular outlet septum or its fibrous remnant. Malalignment can also be found between the apical ventricular septum and the atrial septum, this being shown in a defect opening to the inlet of the right ventricle. We conclude by emphasizing that, so as to bring together all the information of surgical significance, it is necessary to take note of the geographical location of holes between the ventricles, their phenotypic features and the presence or absence of malalignment between the septal components.


Related Concept Videos
 01:27
Anatomy of the Heart
 01:20
Anatomy of the Heart
The heart has three layers: the innermost endocardium, the muscular myocardium, and the outer epicardium, all working together for optimal cardiac function.
Chambers of the Heart
The heart is made up of four...
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:15
Aortic Regurgitation I: Introduction
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...
 01:18
Anatomy of the Brain: Ventricles