Related Experiment Video
Updated: Apr 19, 2026
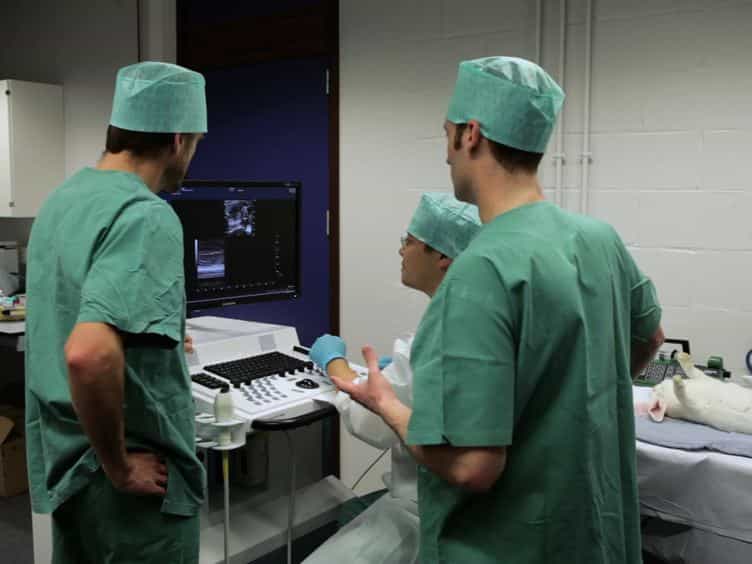
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
Shining light in dark corners: diagnosis and management of late-onset fetal growth restriction
Teresa M MacDonald1, Elizabeth A McCarthy, Susan P Walker
1The Northern Hospital, Melbourne, Victoria, Australia; Department of Obstetrics and Gynaecology, University of Melbourne, Melbourne, Victoria, Australia.

Fetal growth restriction (FGR) is the single biggest risk factor for stillbirth. In the absence of any effective treatment for fetal growth restriction, the mainstay of management is close surveillance and timely delivery. While such statements are almost self-evident, the daily clinical challenge of late-onset fetal growth restriction remains; the competing priorities of minimising stillbirth risk, while avoiding excessive obstetric intervention and the neonatal sequelae of iatrogenic preterm birth. This dilemma is made harder because the tools for late-onset FGR diagnosis and surveillance compare poorly to those used in early-onset FGR; screening tests in early pregnancy have limited predictive value; most cases escape clinical detection, a phenomenon set to worsen given the obesity epidemic; there is a failure of consensus on the definition of small for gestational age, and ancillary tools, such as umbilical artery Doppler--of value in identification of preterm FGR--are less useful in the late-preterm period and at term. Most importantly, the problem is common; 96% of all births occur after 32 weeks. This means a poor noise/signal ratio of any test or management algorithm will inevitably have large clinical consequences. Into such a dark corner, we cast some light; a summary on diagnostic criteria, new developments to improve the diagnosis of late-onset FGR and a suggested approach to management.
Fetal growth restriction (FGR) is the single biggest risk factor for stillbirth. In the absence of any effective treatment for fetal growth restriction, the mainstay of management is close surveillance and timely delivery. While such statements are almost self-evident, the daily clinical challenge of late-onset fetal growth restriction remains; the competing priorities of minimising stillbirth risk, while avoiding excessive obstetric intervention and the neonatal sequelae of iatrogenic preterm birth. This dilemma is made harder because the tools for late-onset FGR diagnosis and surveillance compare poorly to those used in early-onset FGR; screening tests in early pregnancy have limited predictive value; most cases escape clinical detection, a phenomenon set to worsen given the obesity epidemic; there is a failure of consensus on the definition of small for gestational age, and ancillary tools, such as umbilical artery Doppler--of value in identification of preterm FGR--are less useful in the late-preterm period and at term. Most importantly, the problem is common; 96% of all births occur after 32 weeks. This means a poor noise/signal ratio of any test or management algorithm will inevitably have large clinical consequences. Into such a dark corner, we cast some light; a summary on diagnostic criteria, new developments to improve the diagnosis of late-onset FGR and a suggested approach to management.

Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...