Related Experiment Video
Updated: Apr 19, 2026


Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Effect of cardiogenic shock hospital volume on mortality in patients with cardiogenic shock
Shahzad Shaefi1, Brian O'Gara1, Robb D Kociol2
1Department of Anesthesia, Critical Care and Pain Medicine, Cardiovascular Institute, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, MA (S.S., B.G., A.M., J.N., E.M., D.T., S.S.).

Insights
Higher hospital volume for cardiogenic shock (CS) is linked to better patient survival. Centers treating more CS patients use advanced therapies more often, reducing in-hospital mortality.
Area of Science:
- Cardiology
- Health Services Research
Background:
- Cardiogenic shock (CS) carries high morbidity and mortality rates (40-60%).
- Effective CS treatment requires complex, goal-oriented therapies, including early revascularization and supportive care.
- The relationship between hospital CS case volume and patient mortality remains unclear.
Purpose of the Study:
- To investigate the association between hospital cardiogenic shock (CS) case volume and in-hospital mortality.
- To determine if higher volume centers utilize advanced CS treatments more frequently.
Main Methods:
- Analysis of 533,179 weighted patient discharges from 2,675 hospitals between 2004-2011 using the Nationwide Inpatient Sample.
- Patients were stratified into quartiles based on mean annual hospital CS case volume.
- Multivariate regression models adjusted for illness severity, comorbidities, hospital characteristics, and treatment variations.
Main Results:
- Hospitals in the lowest CS volume quartile (≤27 cases/year) had a 1.27 odds ratio for inpatient mortality compared to the highest volume quartile.
- In-hospital mortality decreased from 41.97% in the lowest volume quartile to 37.01% in the highest volume quartile.
- Higher volume centers demonstrated significantly increased use of coronary artery bypass grafting, percutaneous coronary intervention, intra-aortic balloon pump counterpulsation, and mechanical circulatory support.
Conclusions:
- Lower cardiogenic shock (CS) case volume is associated with increased inpatient mortality.
- Higher volume hospitals utilize standard supportive and revascularization techniques more frequently.
- Future research should explore optimal management strategies for patients with CS at lower volume centers, potentially involving early stabilization and transfer.
Background:
Cardiogenic shock (CS) is associated with significant morbidity, and mortality rates approach 40% to 60%. Treatment for CS requires an aggressive, sophisticated, complex, goal-oriented, therapeutic regimen focused on early revascularization and adjunctive supportive therapies, suggesting that hospitals with greater CS volume may provide better care. The association between CS hospital volume and inpatient mortality for CS is unclear.
Methods And Results:
We used the Nationwide Inpatient Sample to examine 533 179 weighted patient discharges from 2675 hospitals with CS from 2004 to 2011 and divided them into quartiles of mean annual hospital CS case volume. The primary outcome was in-hospital mortality. Multivariate adjustments were performed to account for severity of illness, relevant comorbidities, hospital characteristics, and differences in treatment. Compared with the highest volume quartile, the adjusted odds ratio for inpatient mortality for persons admitted to hospitals in the lowest-volume quartile (≤27 weighted cases per year) was 1.27 (95% CI 1.15 to 1.40), whereas for admission to hospitals in the low-volume and medium-volume quartiles, the odds ratios were 1.20 (95% CI 1.08 to 1.32) and 1.12 (95% CI 1.01 to 1.24), respectively. Similarly, improved survival was observed across quartiles, with an adjusted inpatient mortality incidence of 41.97% (95% CI 40.87 to 43.08) for hospitals with the lowest volume of CS cases and a drop to 37.01% (95% CI 35.11 to 38.96) for hospitals with the highest volume of CS cases. Analysis of treatments offered between hospital quartiles revealed that the centers with volumes in the highest quartile demonstrated significantly higher numbers of patients undergoing coronary artery bypass grafting, percutaneous coronary intervention, or intra-aortic balloon pump counterpulsation. A similar relationship was demonstrated with the use of mechanical circulatory support (ventricular assist devices and extracorporeal membrane oxygenation), for which there was significantly higher use in the higher volume quartiles.
Conclusions:
We demonstrated an association between lower CS case volume and higher mortality. There is more frequent use of both standard supportive and revascularization techniques at the higher volume centers. Future directions may include examining whether early stabilization and transfer improve outcomes of patients with CS who are admitted to lower volume centers.


Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
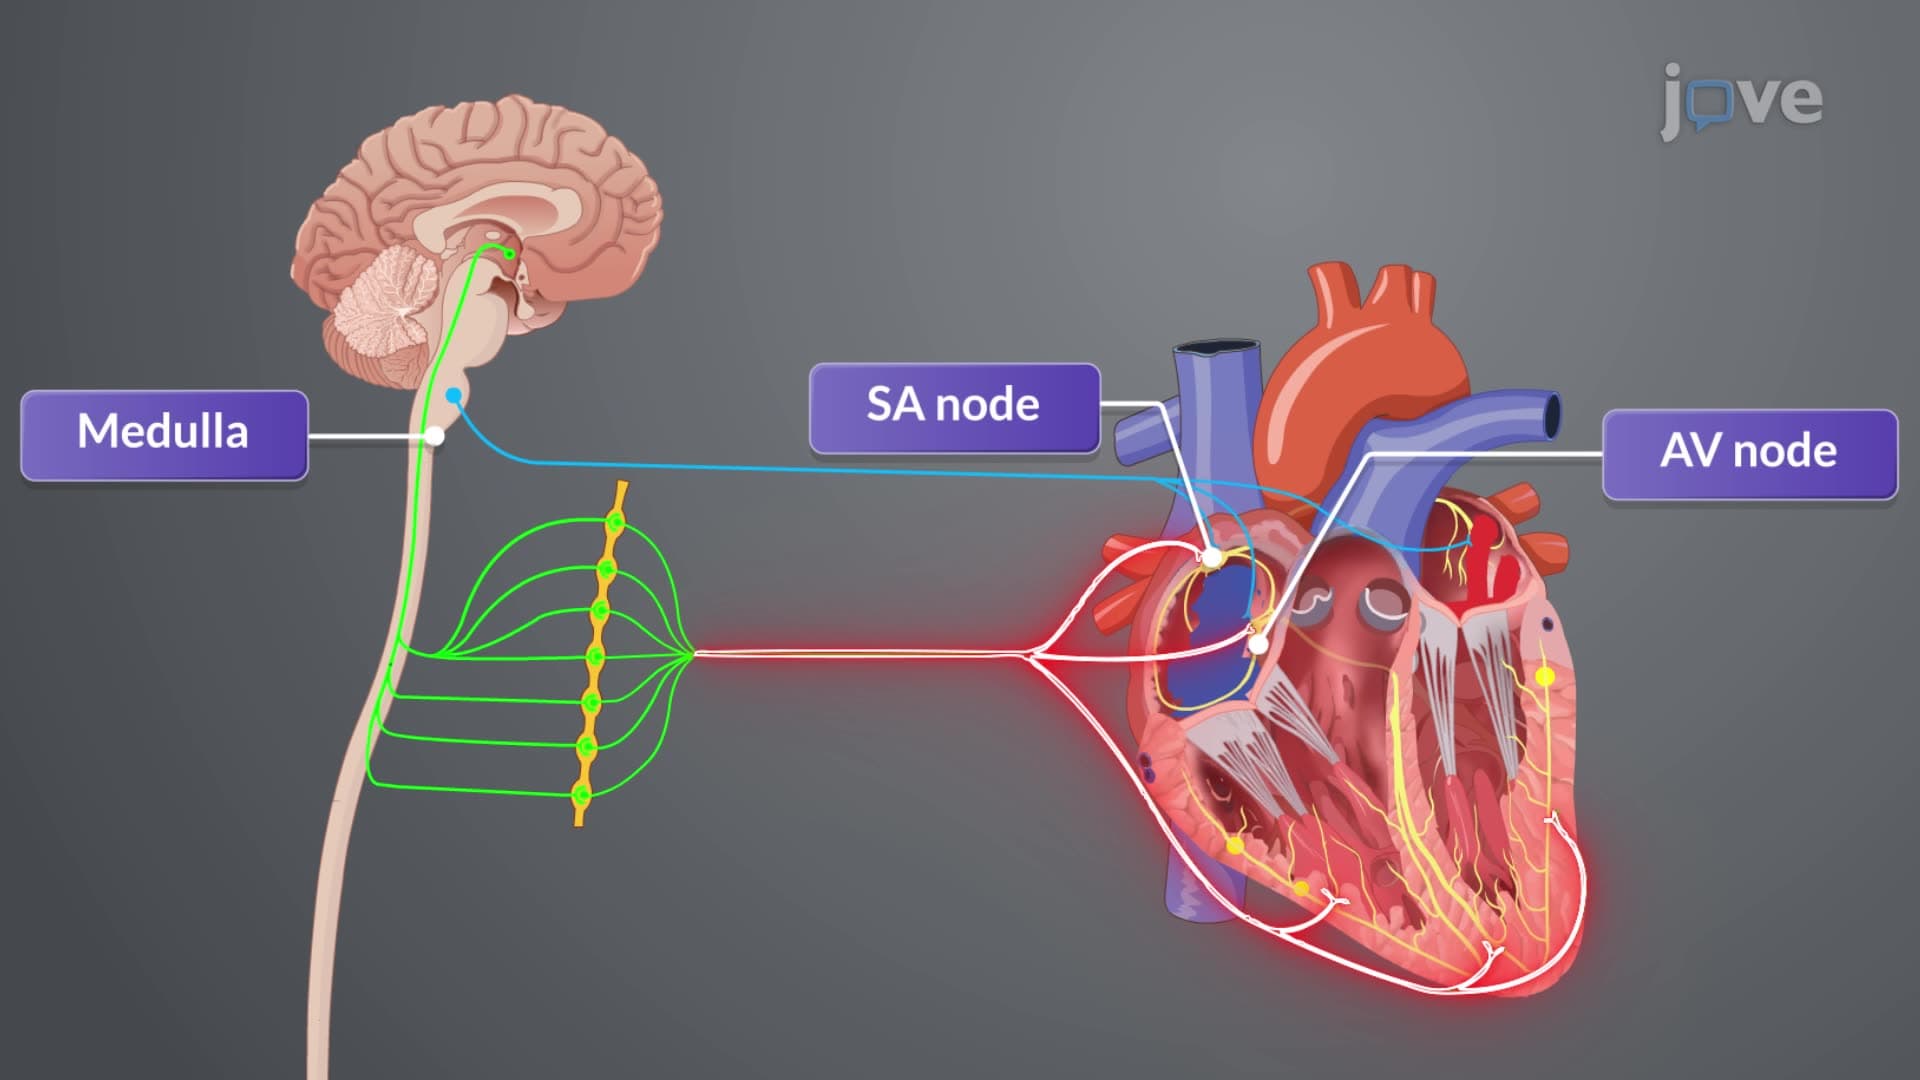
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...