Related Experiment Video
Updated: Apr 18, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Patient cost sharing and receipt of erythropoiesis-stimulating agents through medicare part D
Amy J Davidoff1, Franklin B Hendrick2, Amer M Zeidan1
1Yale School of Public Health, Yale University; Yale Cancer Center, Yale School of Medicine, New Haven, CT; University of Maryland School of Pharmacy; Marlene and Stewart Greenebaum Cancer Center, University of Maryland School of Medicine, Baltimore, MD; and US Health Outcomes and Medical Policy, GlaxoSmithKline, Durham, NC.

Purpose:
Medicare Part D prescription benefits cover injected medications, normally covered under Part B, when administered outside of physician offices. Erythropoiesis-stimulating agents (ESAs) used for chronic anemia management in patients with myelodysplastic syndromes (MDS) are commonly injected in a physician office but can be administered safely at home. In this study, we explored out-of-pocket (OOP) costs and receipt of Part D-covered ESAs in Medicare beneficiaries with MDS.
Materials And Methods:
Patients with MDS enrolled in Medicare Parts A, B, and D were identified using diagnosis codes from 100% claims from 2006 to 2008. OOP costs for the mean erythropoietin alfa claim were compared for Parts B and D. Multivariable models examined the effect of low-income subsidy (LIS) and other Part D cost sharing on receipt of any ESA and any Part D-covered ESA.
Results:
A total of 13,117 (62.9%) of 20,848 patients received ESAs, but only 1,436 (6.9%) had any Part D claim. OOP payment was $348 under Part D versus $161 under Part B. Among patients with ESA use, those with LIS were 4× more likely to receive Part D ESAs (P < .01).
Conclusion:
Few patients with MDS received ESAs through Part D. OOP payments required under Part D were substantially higher than under Part B. Cost sharing, as reflected by LIS receipt, likely affected decisions to prescribe ESAs outside of the physician office. Improved coordination between Part B and D benefits regarding issues of home injection of medications may create incentives that improve patient access and convenience and reduce costs associated with administration.

Related Concept Videos
 01:30
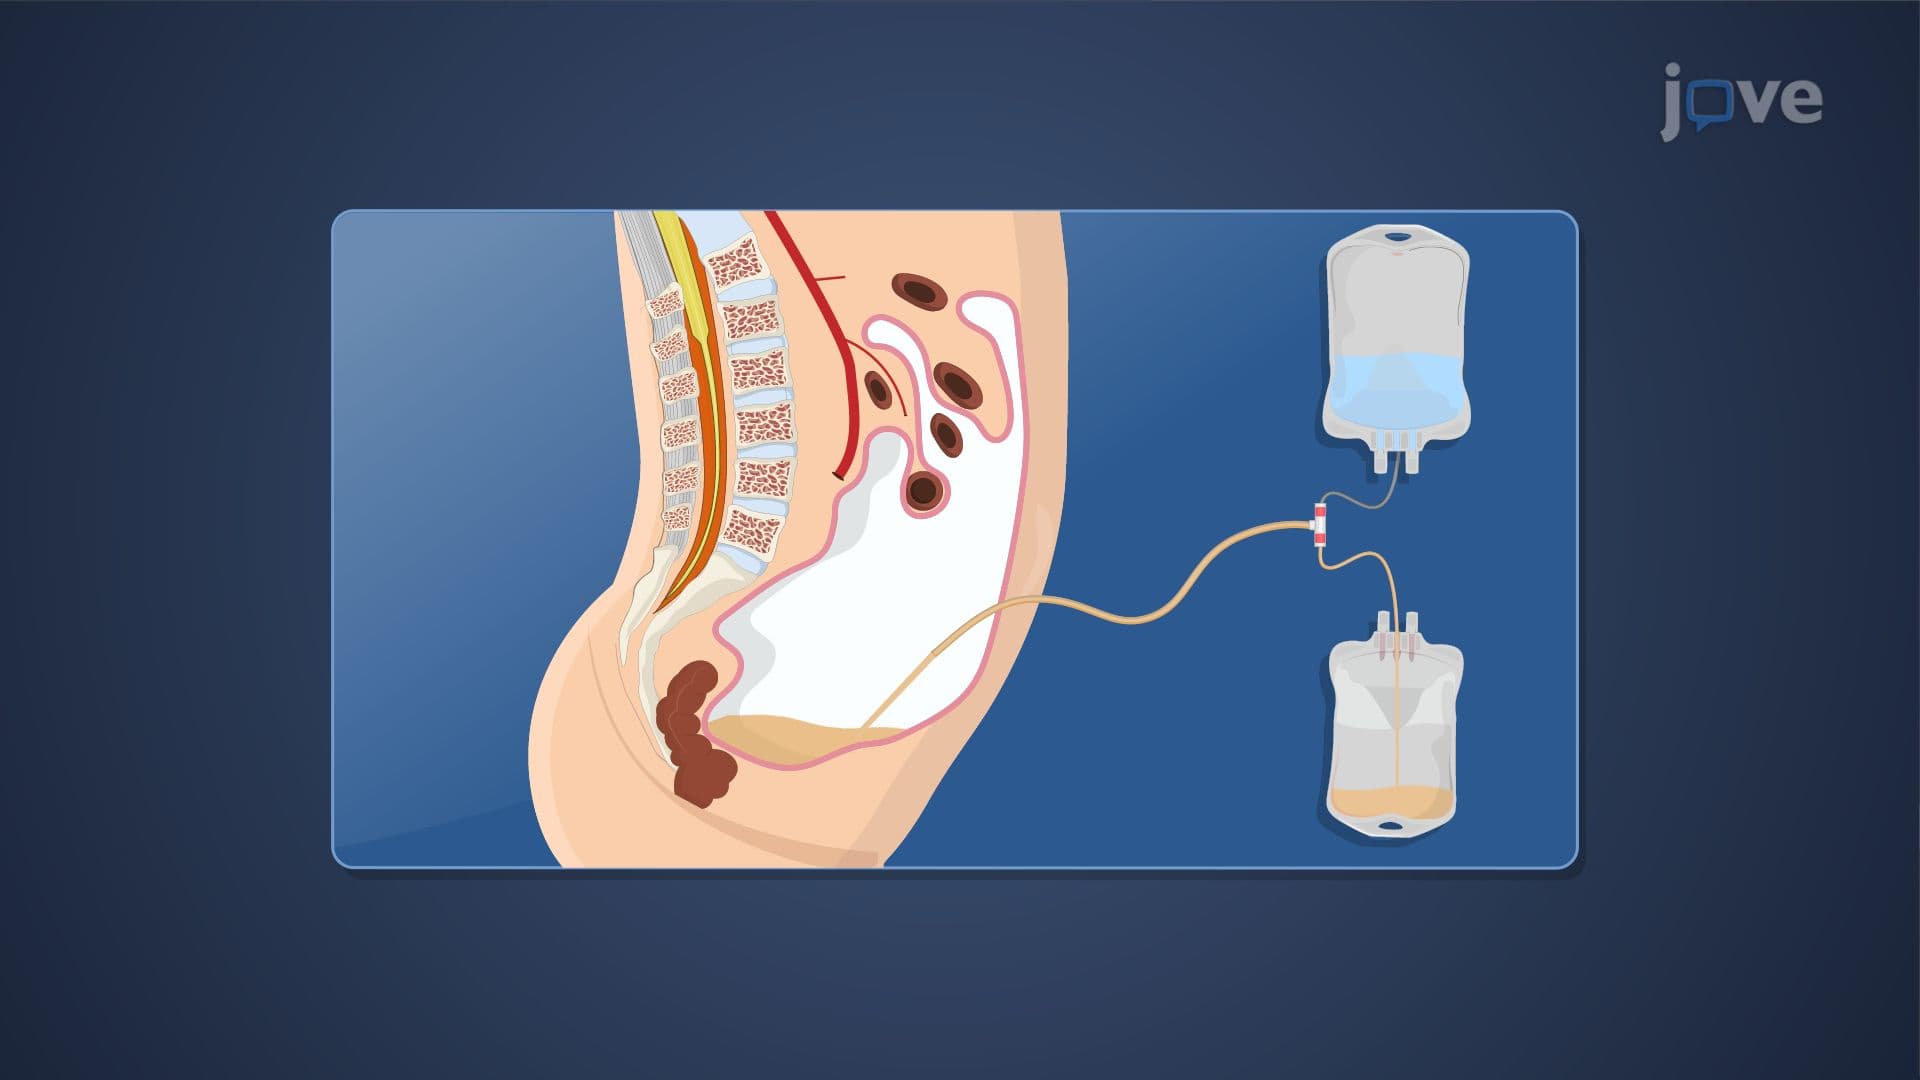
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:25
Peritoneal Dialysis III: Nursing Management
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment