Related Experiment Video
Updated: Apr 18, 2026
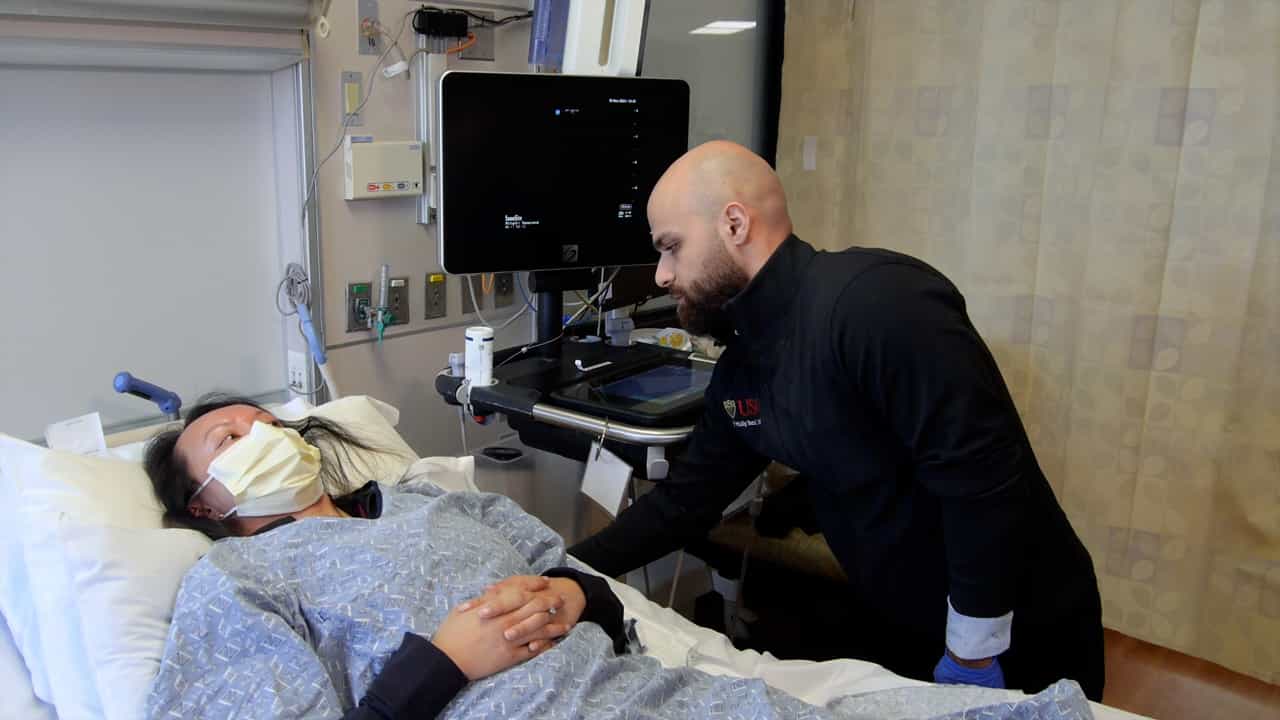
Point of Care Transcranial Color-Coded Duplex Ultrasound of the Middle Cerebral Artery
Published on: August 9, 2024
Optimal Cerebral Perfusion Pressure Management at Bedside: A Single-Center Pilot Study
Celeste Dias1, Maria João Silva, Eduarda Pereira
1Neurocritical Care Unit, Intensive Care Department, Hospital Sao Joao, Porto, Portugal, mceleste.dias@gmail.com.

Background:
Guidelines recommend cerebral perfusion pressure (CPP) values of 50-70 mmHg and intracranial pressure lower than 20 mmHg for the management of acute traumatic brain injury (TBI). However, adequate individual targets are still poorly addressed, since patients have different perfusion thresholds. Bedside assessment of cerebral autoregulation may help to optimize individual CPP-guided treatment.
Objective:
To assess staff compliance and outcome impact of a new method of autoregulation-guided treatment (CPPopt) based on continuous evaluation of cerebrovascular reactivity (PRx).
Methods:
Prospective pilot study of severe TBI adult patients managed with continuous multimodal brain monitoring in a single Neurocritical Care Unit (NCCU). Every minute CPPopt was automatically estimated, based on the previous 4-h window, as the CPP with the lowest PRx indicating the best cerebrovascular pressure reactivity. Patients were managed with CPPopt targets whenever possible and otherwise CPP was managed following general/international guidelines. In addition, other offline CPPopt estimates were calculated using cerebral oximetry (COx-CPPopt), brain tissue oxygenation (ORxs-CPPopt), and cerebral blood flow (CBFx-CPPopt).
Results:
Eighteen patients with a total multimodal brain monitoring time of 5,520 h were enrolled. During the total monitoring period, 11 patients (61 %) had a CPPopt U-shaped curve, 5 patients (28 %) had either ascending or descending curves, and only 2 patients (11 %) had no fitted curve. Real CPP correlated significantly with calculated CPPopt (r = 0.83, p < 0.0001). Preserved autoregulation was associated with greater Glasgow coma score on admission (p = 0.01) and better outcome (p = 0.01). We demonstrated that patients with the larger discrepancy (>10 mm Hg) between real CPP and CPPopt more likely have had adverse outcome (p = 0.04). Comparison between CPPopt and the other estimates revealed similar limits of precision. The lowest bias (-0.1 mmHg) was obtained with COx-CPPopt (NIRS).
Conclusion:
Targeted individual CPP management at the bedside using cerebrovascular pressure reactivity seems feasible. Large deviation from CPPopt seems to be associated with adverse outcome. The COx-CPPopt methodology using non-invasive CO (NIRS) warrants further evaluation.


Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:24
Blood Pressure
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management