Related Experiment Video
Updated: Apr 18, 2026


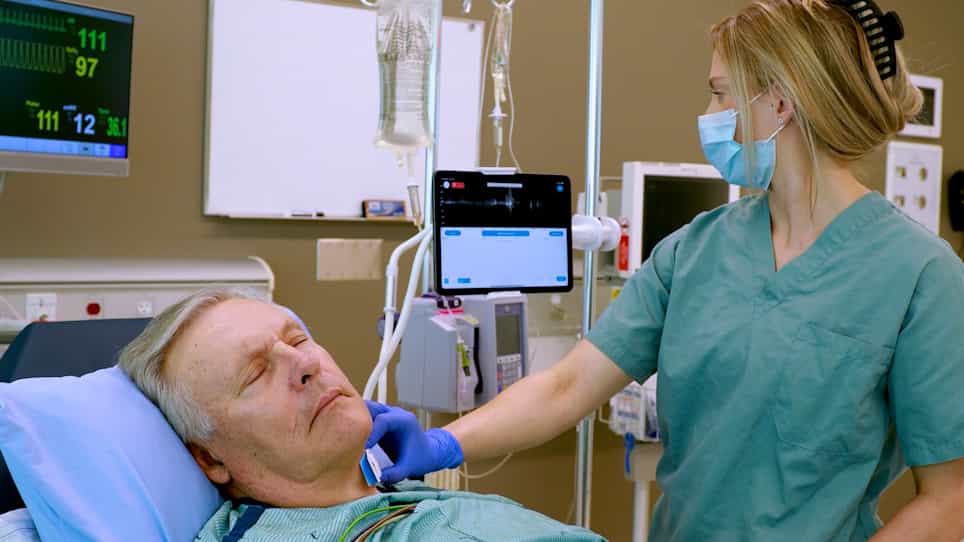
Echocardiographic Assessment Using Subxiphoid-Only Examination for Hypotensive Patients
Published on: April 18, 2025
[Influence of fluid loading in patients at different stages of septic shock: a prospective study]
Linlin Zhi1, Wei Feng, Yinan Guo
1Department of Critical Care Medicine, the Fourth People's Hospital of Shenyang, Shenyang 110031, Liaoning, China. Corresponding author: Zhi Linlin,

Objective:
To explore the influence of fluid loading at different stages in patients with septic shock.
Methods:
A prospective study was conducted. Forty-two mechanically ventilated patients in septic shock were enrolled in the Department of Critical Care Medicine of the Fourth People's Hospital of Shenyang from March 2010 to March 2014. Fluid loading was performed at 0, 24, 48 and 72 hours after the diagnosis of septic shock. The hemodynamic parameters including cardiac output ( CO ), stroke volume ( SV ), and extravascular lung water index ( EVLWI ) were measured by pulse indicator continuous cardiac output ( PiCCO ), and arterial partial pressure ( PaO2 ) was determined. Positive responders were defined as SV increased by more than 15% after fluid loading. Increase of lung water was defined as EVLWI increased after fluid loading and its value was more than 7 mL/kg. Oxygenation descend was defined when oxygenation index ( PaO2/FiO2 ) lowered. Fluid responsiveness, extravascular lung water, and oxygenation were analyzed and recorded at different stages in patients with septic shock.
Results:
Fluid loading test was conducted for a total of 168 times in 42 patients. Compared with those before fluid loading test, the heart rate ( HR ) was lowered, and mean arterial pressure ( MAP ), CO, and SV were increased after fluid loading at 0, 24, 48 hours ( all P<0.01),unchanged at 72 hours. EVLWI levels at all time points were increased including an increase of EVLWI less than 7 mL/kg at 0 hour and 24 hours, and higher than 7 mL/kg at 48 hours and 72 hours [ EVLWI ( mL/kg ) at 0 hour: 6.0±1.5 vs. 4.7±1.5, t = -4.183, P = 0.000; 24 hours: 6.5±1.5 vs. 5.6±1.3, t = -6.000, P = 0.000; 48 hours: 8.1±2.2 vs. 6.1±1.7, t = -7.246, P = 0.000; 72 hours: 9.0±2.4 vs. 6.2±1.5, t = -7.524, P = 0.000 ]. After fluid loading, PaO2/FiO2 was increased remarkably at 0 hour and 24 hours, unchanged at 48 hours, and decreased significantly at 72 hours [ PaO2/FiO2 ( mmHg, 1 mmHg = 0.133 kPa ) at 0 hour: 189.6±34.5 vs. 183.2±36.6, t = -3.644, P = 0.002; 24 hours: 194.6±35.7 vs. 190.7±37.5, t = -4.594, P = 0.000; 48 hours: 201.8±30.2 vs. 200.8±33.0, t = -0.793, P=0.437; 72 hours: 201.7±24.8 vs. 206.2±26.9, t = 2.243, P = 0.036 ]. The rate of positive response gradually decreased: 85.7%, 80.9%, 42.8%, 28.6% at 0, 24, 48, and 72 hours, the rate of lung water increased was gradually elevated: 9.8%, 14.3%, 42.8%, 61.9% at 0, 24, 48, and 72 hours, and there was an increase of rate of lowering oxygenation with elapse of time ( 9.5%, 11.9%, 19.0%, 33.3% at 0, 24, 48 and 72 hours ). Compared with 0 hour, the rate of positive response decreased and rate of lung water increased were increased from 48 hours on ( P<0.05 or P<0.01 ), and rate of lowering oxygenation was increased at 72 hours ( P<0.01 ).
Conclusions:
48 to 72 hours might be the crucial period of occurrence of volume overload in patients with septic shock. Curtailing fluid infusion during this period might reduce the occurrence of pulmonary edema.

Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Acute Kidney Injury VI: Nursing Management
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...