Risk of local failure after ultrasound guided irreversible electroporation of malignant liver tumors

Introduction:
Irreversible electroporation (IRE) is considered superior to thermoablations for tumors in the vicinity of larger vessels and the liver hilum. We report on an initial clinical experience of IRE.
Materials And Methods:
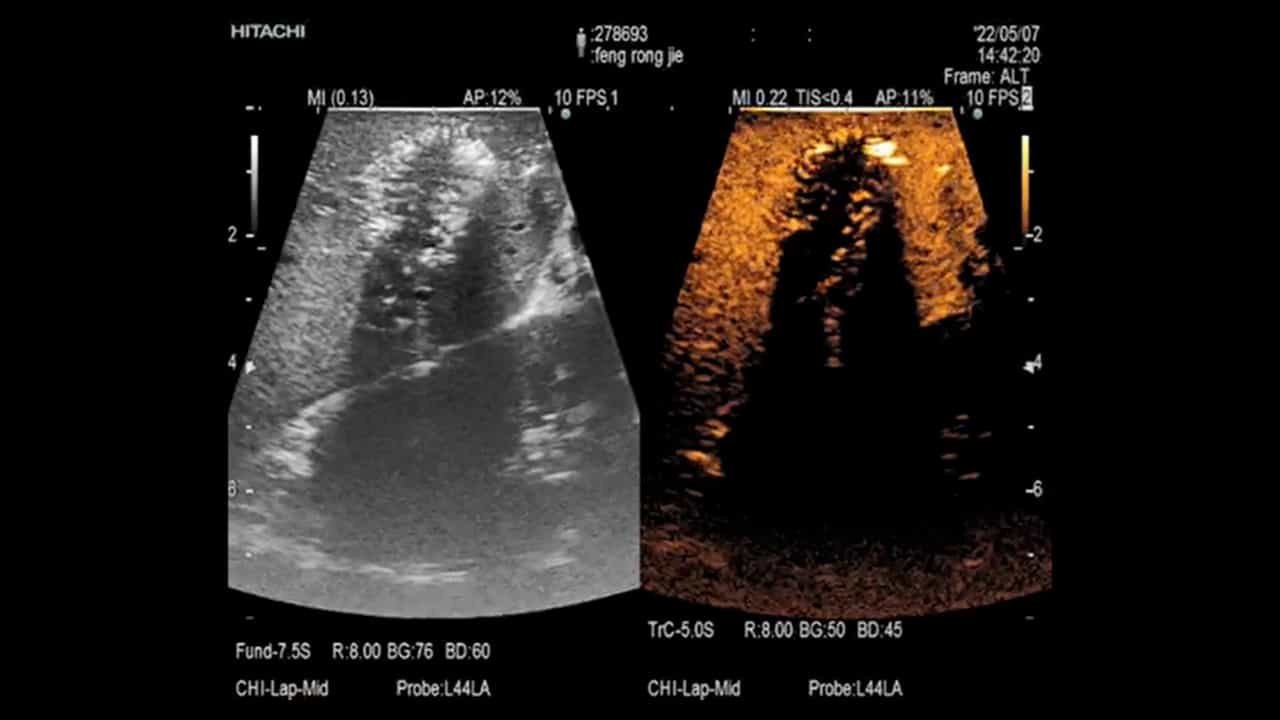
Indications included focal liver lesions <3 cm, irresectability due to contraindications and expected complications and/or irradicality following radiofrequency ablation (RFA). Ultrasound was chosen for guidance and needle placement.
Results:
IRE was intended to perform in 14 patients with 1 procedure aborted due to technical failure. Among the 13 successfully treated were 7 percutaneous, 4 laparoscopic, and 2 open surgical procedures. The average age was 63 ± 10 years. Twelve solitary nodules and one bifocal disease were treated with an average size of 1.5 cm ± 0.5 cm. Median follow-up was 6 months. Three incomplete ablations account for 21% (3/14), 2 of them occurring in 2 metastases larger than 2 cm percutaneously treated with 5 needles instead of 4 used for smaller tumor sizes.
Conclusion:
IRE was introduced without difficulties into clinical practice. As a main obstacle emerged in visualization of the needles, computed tomography may offer advantages in the guidance of percutaneous IRE of liver metastases larger than 2 cm. Local failure occurred in 21%.