Related Experiment Video
Updated: Apr 18, 2026


Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
An analysis of the anatomic variations of the paranasal sinuses and ethmoid roof using computed tomography
Hatice Kaplanoglu1, Veysel Kaplanoglu2, Alper Dilli1
1Department of Radiology, Diskapi Yildirim Beyazit Training and Research Hospital, Ankara, Turkey.

Objective:
To determine the Keros classification and asymmetrical distribution rates of the ethmoid roof and the frequency of anatomic variations of the paranasal sinuses.
Materials And Methods:
Paranasal sinus scans of 500 patients obtained using computed tomography were evaluated retrospectively. Measurements were performed using a coronal plan with right-left comparison and with distance measurement techniques. The depth of the lateral lamella was calculated by subtracting the depth of the cribriform plate from the depth of the medial ethmoid roof. The results were classified according to their Keros classification. Any asymmetries in the ethmoid roof depth and fovea ethmoidalis configuration were examined. The anatomic variations frequently encountered in paranasal sinuses (pneumatized middle concha, paradoxical middle concha, agger nasi cells, Haller cells, Onodi cells, etc.) were defined.
Results:
The mean height of the lateral lamella cribriform plate (LLCP) was 4.92±1.70 mm. The cases were classified as 13.4% Keros Type I, 76.1% Keros Type II, and 10.5% Keros Type III. There was asymmetry in the LLCP depths of 80% of the cases, and a configuration asymmetry in the fovea in 35% of the cases. In 32% of the cases with fovea configuration asymmetry, there was also asymmetry in the height of the right and left LLCP. The most frequent variations were nasal septum deviation (81.8%), agger nasi cells (63.8%), intralamellar air cells (45%), and concha bullosa (30%).
Conclusion:
Using the Keros classification for LLCP height, higher rates of Keros Type I were found in other studies than in our study. The most frequent classification was Keros Type II. The paranasal sinus variations in each patient should be carefully evaluated. The data obtained from these evaluations can prevent probable complications by informing rhinologists performing endoscopic sinus surgery about preoperative and intraoperative processes.


Related Concept Videos
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:29
Anatomy of Respiratory System I: Upper Respiratory Tract
Nose and nasal cavity
The nose and nasal cavity represent the main external openings of the respiratory tract....
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
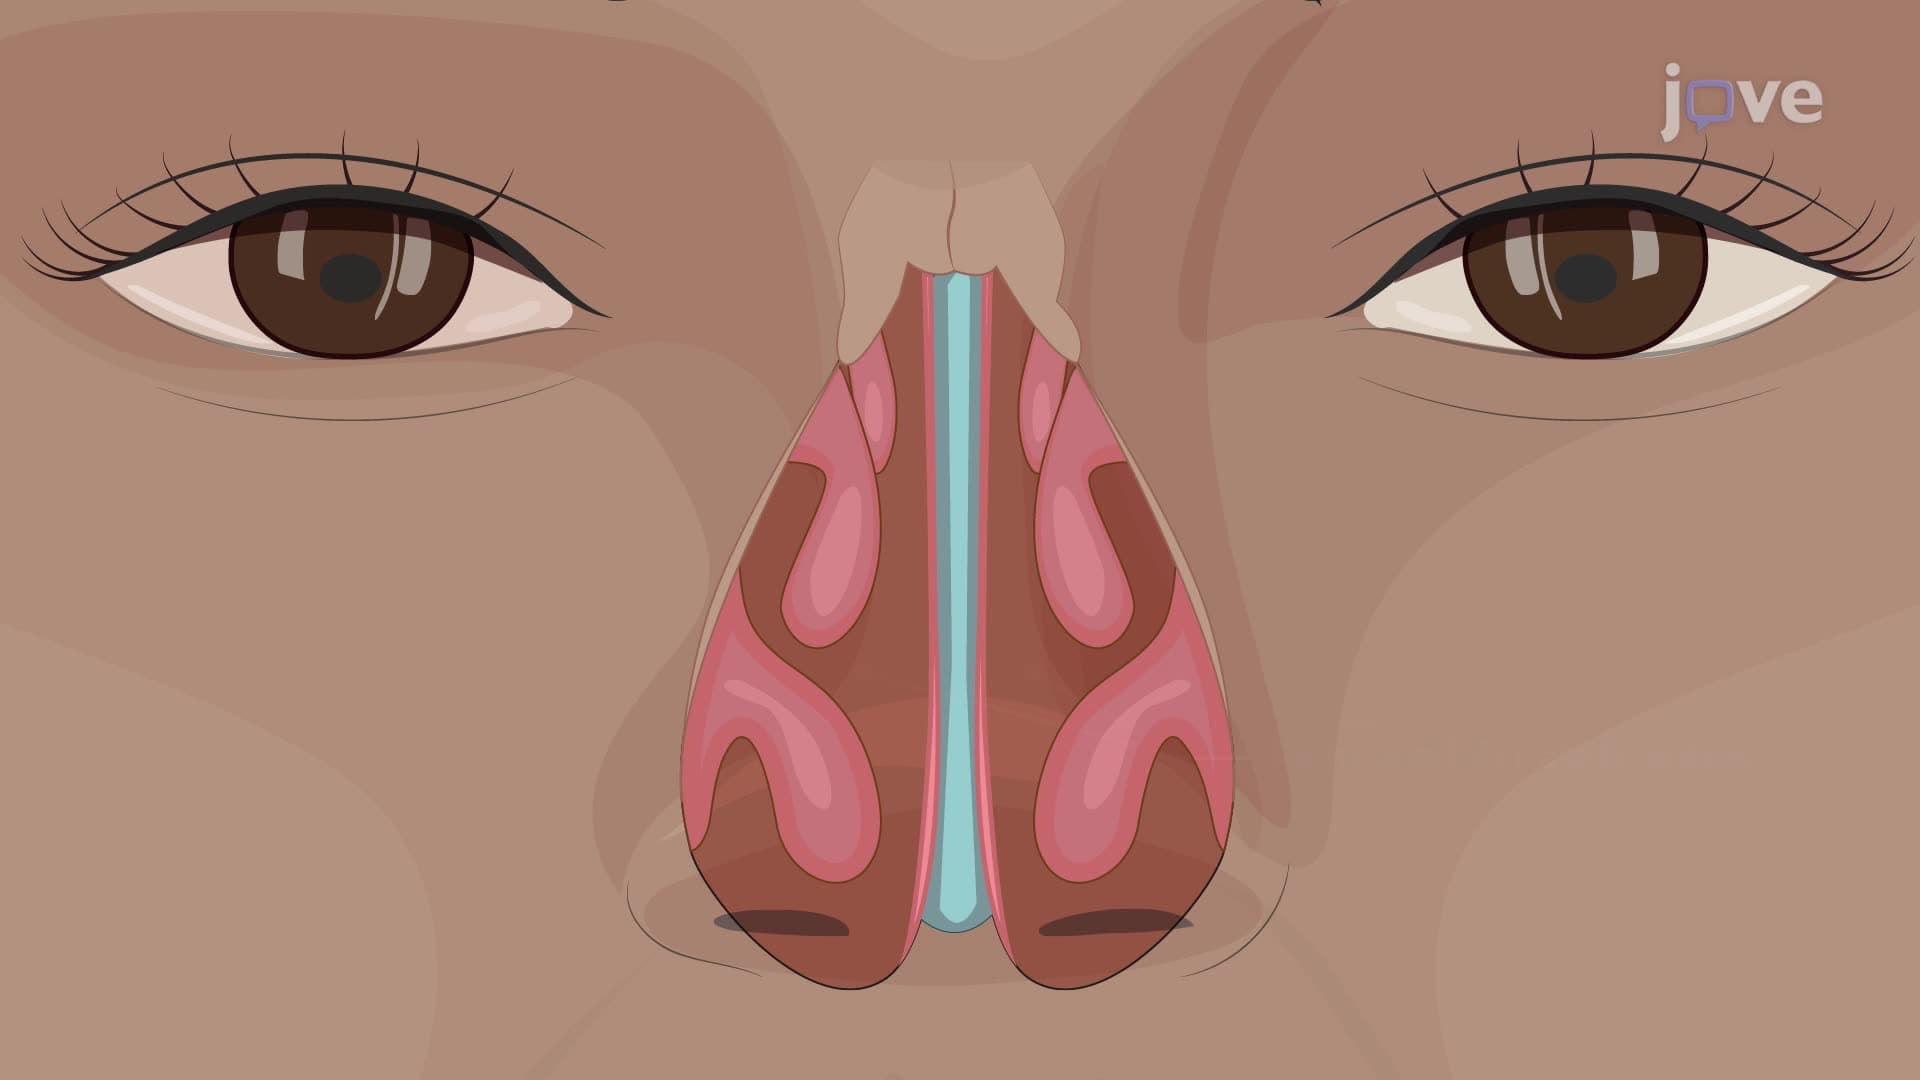 01:24
Nose and Nasal Cavity
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Imaging Studies III: Computed Tomography