Related Experiment Video
Updated: Apr 18, 2026

High-Throughput Cardiotoxicity Screening Using Mature Human Induced Pluripotent Stem Cell-Derived Cardiomyocyte Monolayers
Published on: March 24, 2023
hERG Blockade by Iboga Alkaloids
Kenneth Alper1, Rong Bai2, Nian Liu2
1Departments of Psychiatry and Neurology, New York University School of Medicine, New York, NY, 10016, USA.

The iboga alkaloids are a class of naturally occurring and synthetic compounds, some of which modify drug self-administration and withdrawal in humans and preclinical models. Ibogaine, the prototypic iboga alkaloid that is utilized clinically to treat addictions, has been associated with QT prolongation, torsades de pointes and fatalities. hERG blockade as IKr was measured using the whole-cell patch clamp technique in HEK 293 cells. This yielded the following IC50 values: ibogaine manufactured by semisynthesis via voacangine (4.09 ± 0.69 µM) or by extraction from T. iboga (3.53 ± 0.16 µM); ibogaine's principal metabolite noribogaine (2.86 ± 0.68 µM); and voacangine (2.25 ± 0.34 µM). In contrast, the IC50 of 18-methoxycoronaridine, a product of rational synthesis and current focus of drug development was >50 µM. hERG blockade was voltage dependent for all of the compounds, consistent with low-affinity blockade. hERG channel binding affinities (K i) for the entire set of compounds, including 18-MC, ranged from 0.71 to 3.89 µM, suggesting that 18-MC binds to the hERG channel with affinity similar to the other compounds, but the interaction produces substantially less hERG blockade. In view of the extended half-life of noribogaine, these results may relate to observations of persistent QT prolongation and cardiac arrhythmia at delayed intervals of days following ibogaine ingestion. The apparent structure-activity relationships regarding positions of substitutions on the ibogamine skeleton suggest that the iboga alkaloids might provide an informative paradigm for investigation of the structural biology of the hERG channel.
The iboga alkaloids are a class of naturally occurring and synthetic compounds, some of which modify drug self-administration and withdrawal in humans and preclinical models. Ibogaine, the prototypic iboga alkaloid that is utilized clinically to treat addictions, has been associated with QT prolongation, torsades de pointes and fatalities. hERG blockade as IKr was measured using the whole-cell patch clamp technique in HEK 293 cells. This yielded the following IC50 values: ibogaine manufactured by semisynthesis via voacangine (4.09 ± 0.69 µM) or by extraction from T. iboga (3.53 ± 0.16 µM); ibogaine's principal metabolite noribogaine (2.86 ± 0.68 µM); and voacangine (2.25 ± 0.34 µM). In contrast, the IC50 of 18-methoxycoronaridine, a product of rational synthesis and current focus of drug development was >50 µM. hERG blockade was voltage dependent for all of the compounds, consistent with low-affinity blockade. hERG channel binding affinities (K i) for the entire set of compounds, including 18-MC, ranged from 0.71 to 3.89 µM, suggesting that 18-MC binds to the hERG channel with affinity similar to the other compounds, but the interaction produces substantially less hERG blockade. In view of the extended half-life of noribogaine, these results may relate to observations of persistent QT prolongation and cardiac arrhythmia at delayed intervals of days following ibogaine ingestion. The apparent structure-activity relationships regarding positions of substitutions on the ibogamine skeleton suggest that the iboga alkaloids might provide an informative paradigm for investigation of the structural biology of the hERG channel.
More Related Videos
 07:16
Methods for the Discovery of Novel Compounds Modulating a Gamma-Aminobutyric Acid Receptor Type A Neurotransmission
Published on: August 16, 2018
 08:49
Assessing Changes in Volatile General Anesthetic Sensitivity of Mice after Local or Systemic Pharmacological Intervention
Published on: October 16, 2013
Related Concept Videos
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:17
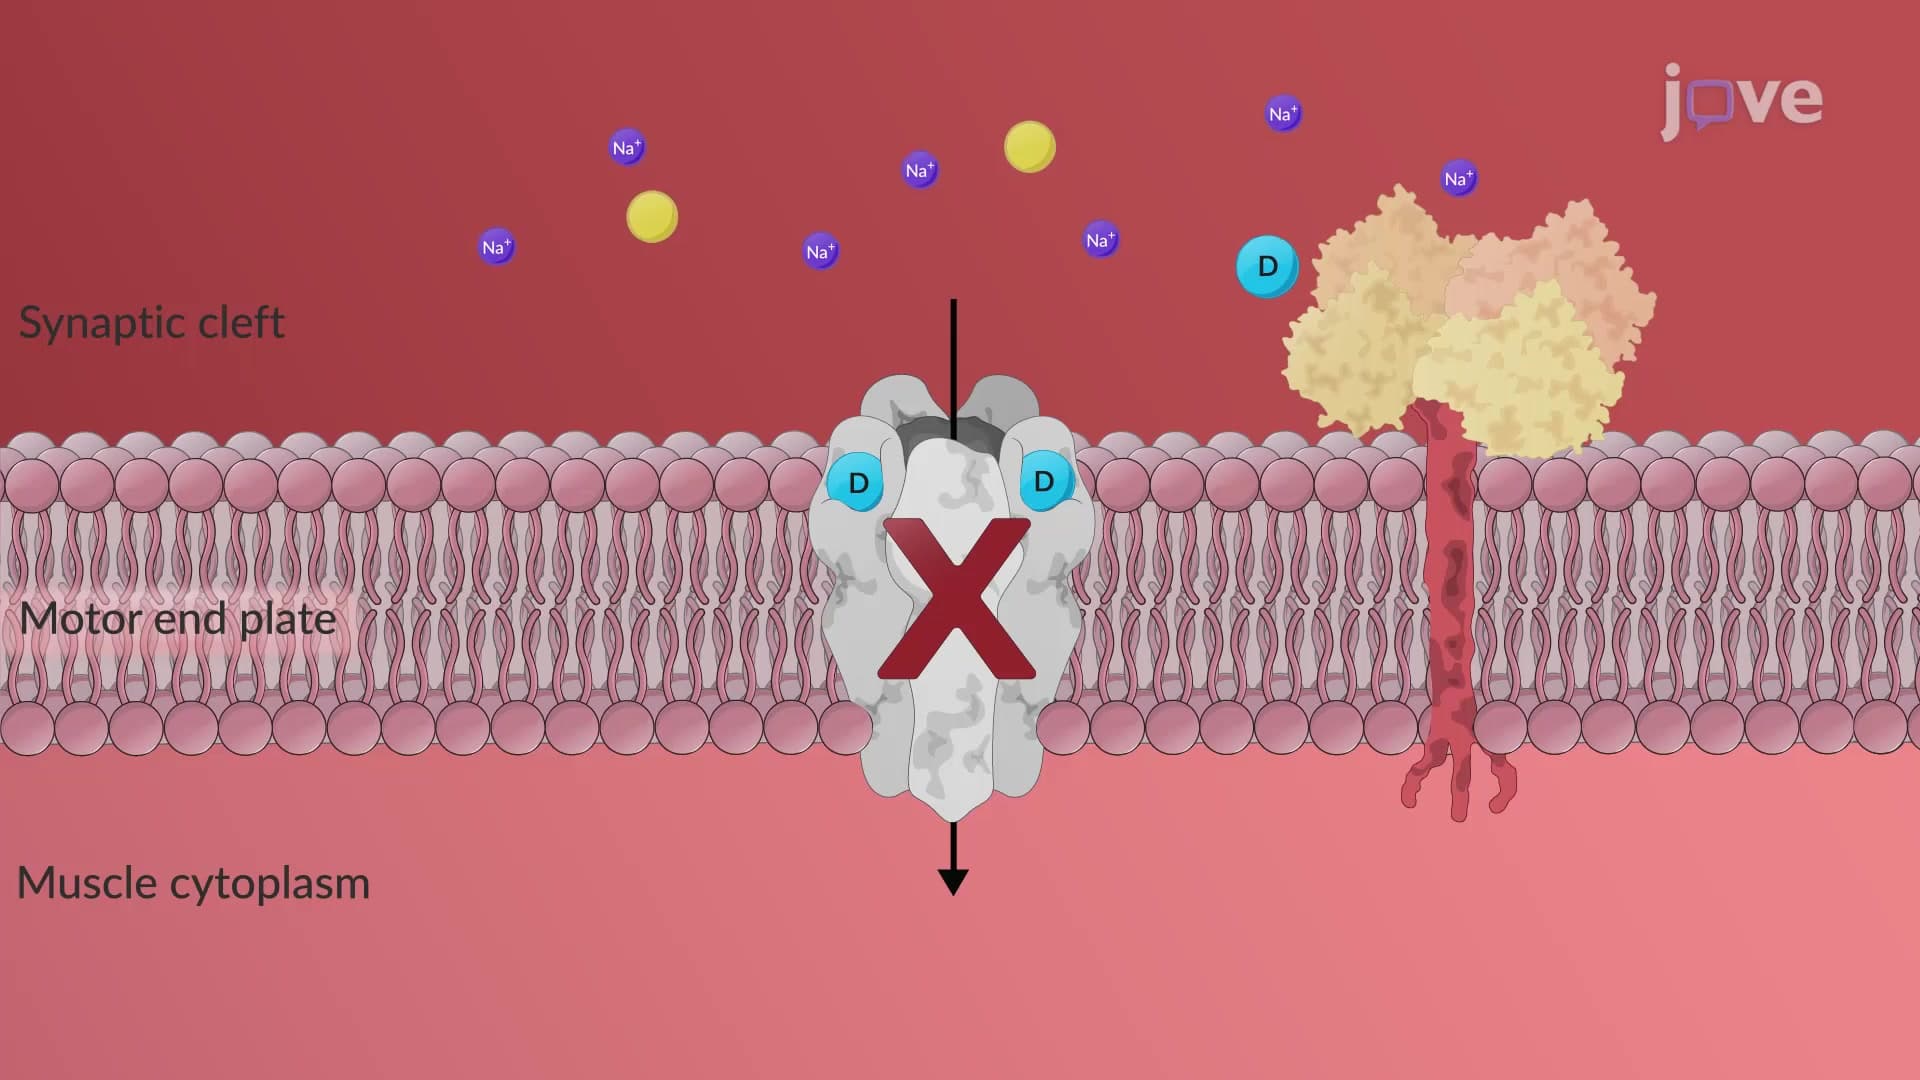
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...