Related Experiment Video
Updated: Apr 17, 2026


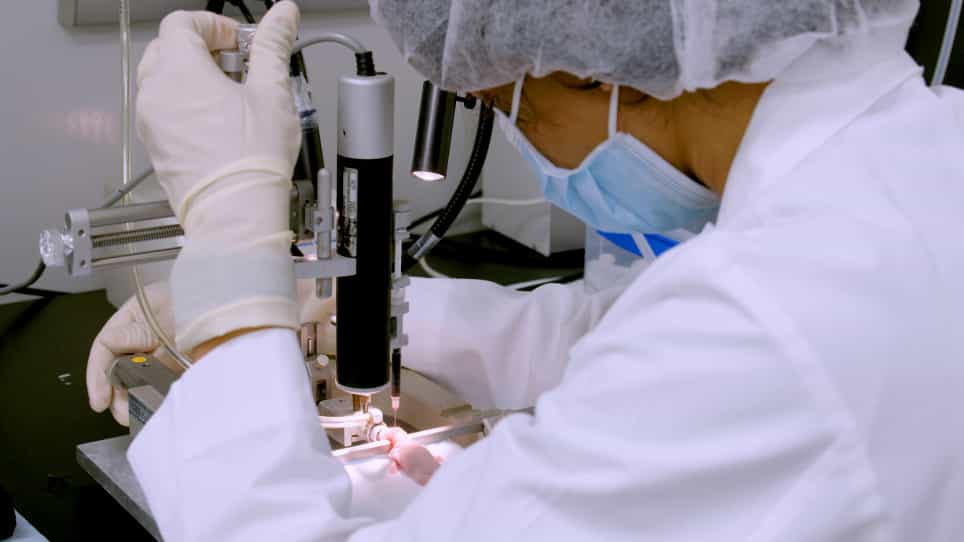
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
[Ventriculo subgaleal shunt in hydrocephalus secondary to intraventricular hemorrhage in prematures]
Antonio García-Méndez1, Leonardo Álvarez-Vázquez1, Fernando Agustín-Aguilar1
1Servicio de Neurocirugía Pediátrica, Hospital General La Raza Dr. Gaudencio González, México, D.F.

Insights
Ventriculo subgaleal shunts effectively manage intraventricular hemorrhage (IVH) in premature infants, reducing infection rates and neurological sequelae. This method offers improved hydrocephalus control and better long-term outcomes for high-risk neonates.
Area of Science:
- Neonatal Neurology
- Pediatric Neurosurgery
- Critical Care Medicine
Context:
- Intraventricular hemorrhage (IVH) remains a significant complication in premature infants, with current incidence rates around 20%.
- Managing IVH presents challenges due to diverse therapeutic options and potential for long-term neurological deficits.
- Historical incidence of IVH in the 1970s-1980s was high (40-50%), highlighting the need for improved interventions.
Purpose:
- To evaluate the efficacy of ventriculo subgaleal shunts in managing intraventricular hemorrhage in premature infants.
- To assess the impact of gestational age, weight, and IVH grade on therapeutic decisions for shunt placement.
- To analyze infection rates, mortality, and long-term neurological sequelae associated with ventriculo subgaleal shunts.
Summary:
- A retrospective review of 48 premature infants treated with ventriculo subgaleal shunts was conducted.
- The average gestational age for shunt placement was 30 months, with an average infant weight of 1,511g.
- The study reported a 4% infection rate and 8% mortality, with no surgical mortality observed. 92% of survivors received a peritoneal shunt.
Impact:
- Derivation using subgaleal shunts significantly reduces infection rates compared to historical data.
- This approach allows for effective control of hydrocephalus, mitigating long-term neurological sequelae in premature infants.
- The findings suggest ventriculo subgaleal shunts are a valuable therapeutic option for reducing morbidity and mortality in neonatal IVH.
Background:
Intraventricular hemorrhage (IVH) is one of the most serious complications in premature lightweight. While in the decade of 1970-1980 the incidence was 40-50%, now it is at least 20%. But it presents a challenge because of the multiple existing therapies and the results in terms of neurological sequelae.
Material And Methods:
We performed a retrospective review of 48 patients managed with ventriculo subgaleal shunt and a therapeutic decision based on gestational age, weight, and grade of intraventricular hemorrhage.
Results:
Of the patients, 29 (60%) of the cases were female and 19 (40%) were male. The average gestation age for placing the subgaleal system was 30 months, with an average weight of 1,511 g, and with an infection rate of 4%. In 44 cases peritoneal system was placed (92%) because four died (8%). No mortality was observed at surgery.
Conclusions:
Mortality in the past appeared in 75% of patients, with the realization that derivation of subgaleal irrigation reduces infections besides allowing proper control of hydrocephalus and thus decreases the long-term neurological sequelae.
More Related Videos

Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology