Related Experiment Video
Updated: Apr 17, 2026

Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Evaluation of sulfobutylether-β-cyclodextrin (SBECD) accumulation and voriconazole pharmacokinetics in critically ill
Tyree H Kiser1, Douglas N Fish2, Christina L Aquilante3
1Department of Clinical Pharmacy, University of Colorado Skaggs School of Pharmacy and Pharmaceutical Sciences, 12850 E Montview Blvd, Mail Stop C238, Aurora, CO, 80045, USA. ty.kiser@ucdenver.edu.

Introduction:
Intravenous (IV) voriconazole is not recommended in patients with creatinine clearance <50 ml/min to avoid potentially toxic accumulation of sulfobutylether-β-cyclodextrin (SBECD). The purpose of this study was to evaluate the pharmacokinetics of SBECD, voriconazole, and voriconazole N-oxide in critically ill patients undergoing continuous renal replacement therapy (CRRT) and to determine if CRRT removes SBECD sufficiently to allow for the use of IV voriconazole without significant risk of SBECD accumulation.
Methods:
This prospective, open-label pharmacokinetic study enrolled patients >18 years old receiving IV voriconazole for a known or suspected invasive fungal infection while undergoing CRRT. Serial blood and effluent samples were collected on days 1, 3, 5, 7, and every 3 to 5 days thereafter. SBECD, voriconazole, and voriconazole N-oxide plasma and effluent concentrations were measured by liquid chromatography-tandem mass spectrometry. Pharmacokinetic, pharmacodynamic, and pharmacogenetic analyses were conducted.
Results:
Ten patients (mean ± standard deviation (SD)) 53 ± 11 years old, 50% male, 81 ± 14 kg, with Acute Physiologic and Chronic Health Evaluation II (APACHE II) scores of 31.5 ± 3.8 were evaluated. All patients underwent continuous venovenous hemofiltration (CVVH) with a median predilution replacement fluid rate of 36 (interquartile range (IQR) 32 to 37) ml/kg/hr and total ultrafiltration rate of 38 (IQR 34 to 39) ml/kg/hr. Mean ± SD voriconazole and SBECD dosages administered were 8.1 ± 2.1 mg/kg/day and 129 ± 33 mg/kg/day, respectively. Voriconazole plasma trough concentrations were >1 mg/L in all patients with CVVH accounting for only 15% of the total body clearance. CVVH accounted for 86% of the total body clearance of SBECD with the majority of the dose being recovered in the effluent. Minimal increases in dose normalized SBECD area under the concentration-time curve from 0 to 12 hours (AUC0-12) (4,484 ± 4,368 to 4,553 ± 2,880 mg*hr/L; P = 0.97) were observed after study day 1.
Conclusions:
CVVH effectively removed SBECD at a rate similar to the ultrafiltration rate. Voriconazole clearance by CVVH was not clinically significant. Standard dosages of IV voriconazole can be utilized in patients undergoing CVVH without significant risk of SBECD accumulation.
Trial Registration:
ClinicalTrials.gov NCT01101386 . Registered 6 April 2010.
More Related Videos
 06:08
Evaluation of Drug Sorption to PVC- and Non-PVC-based Tubes in Administration Sets Using a Pump
Published on: March 11, 2017
 08:44
Continuous IV Infusion is the Choice Treatment Route for Arginine-vasopressin Receptor Blocker Conivaptan in Mice to Study Stroke-evoked Brain Edema
Published on: September 1, 2016
Related Concept Videos
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:15
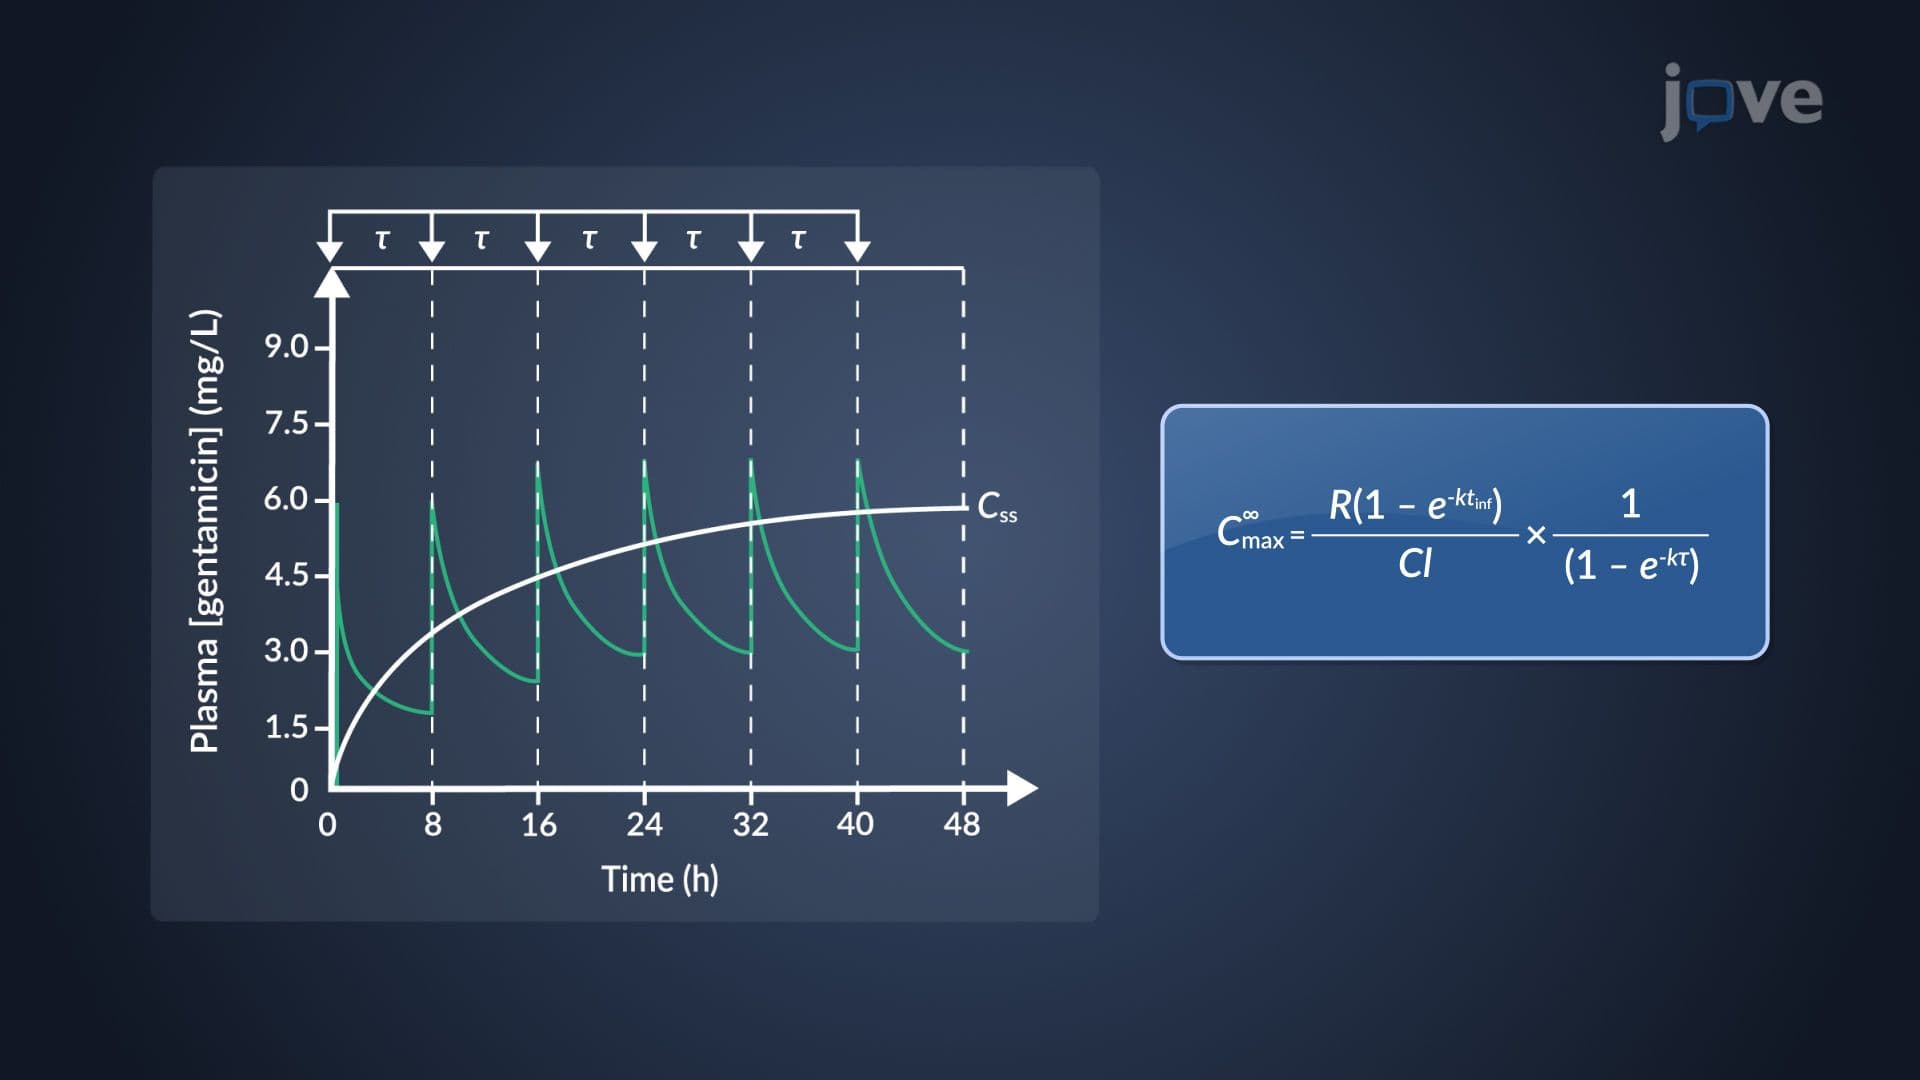
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...