Related Experiment Video
Updated: Apr 17, 2026
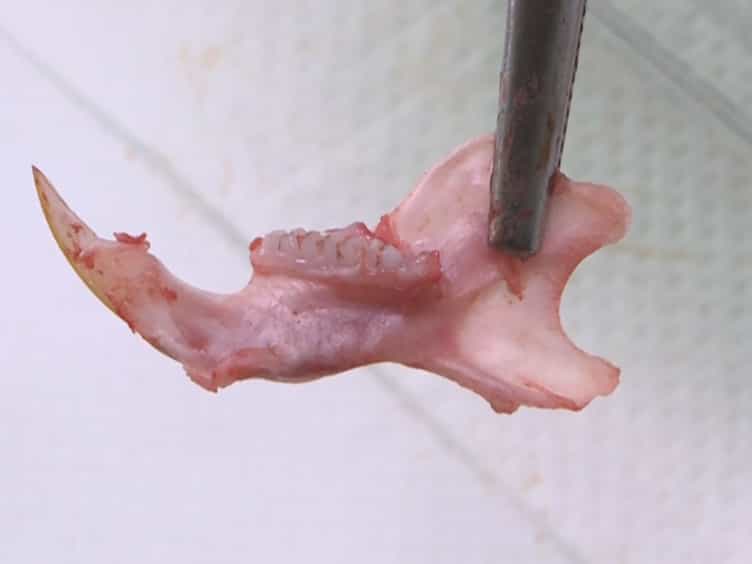

Micro-dissection of Enamel Organ from Mandibular Incisor of Rats Exposed to Environmental Toxicants
Published on: March 29, 2018
Income-based life-course models of caries in 30-year-old Australian adults
David Simon Brennan1, A John Spencer
1Australian Research Centre for Population Oral Health, School of Dentistry, University of Adelaide, Adelaide, SA, Australia.

Objectives:
To assess income-based life-course models between the age of 13 and 30 years and caries in young adults.
Methods:
In 1988-89, n = 7673 South Australian school children aged 13 years were sampled with n = 4604 children (60.0%) and n = 4476 parents (58.3%) returning questionnaires. In 2005-06, n = 632 baseline study participants aged 30 years responded (43.0% of those traced and living in Adelaide). Life-course models representing critical period, cumulative risk and social mobility were constructed using income tertiles at ages 13 and 30 years. Critical period was evaluated by comparing the low tertile with the middle and higher tertiles at age 13. Cumulative risk was evaluated by coding the low tertile as 2, the middle tertile as 1 and highest tertile as 0, and summing to produce a cumulative risk score categorized into lower (score 0-1), moderate (score of 2) and higher risk (scores 3-4). Social mobility was classified using tertiles into stable disadvantaged, downwardly mobile, stable middle income, upwardly mobile and stable advantaged.
Results:
Models adjusting for sex, visiting and toothbrushing at age 30 showed no association between caries at age 30 and low income at age 13 years (critical period model). Compared to the low cumulative risk group based on income, decayed teeth (RR = 1.6) and missing teeth (RR = 7.2) were higher (P < 0.05) in the higher risk group, and missing teeth (RR = 6.0) were higher in the moderate risk group (cumulative risk model). There were more (P < 0.05) decayed teeth in the disadvantaged (RR = 3.1) and stable middle income groups (RR = 2.2), more missing teeth for those classified as disadvantaged (RR = 6.4), stable middle (RR = 6.3) and downwardly mobile (RR = 2.8), and higher DMFT for the disadvantaged group (RR = 1.5) compared to the upwardly mobile group (social mobility model).
Conclusions:
Socioeconomic advantage and upward mobility were associated with fewer decayed and missing teeth at age 30 years. Life-course models of cumulative risk and social mobility influenced oral health outcomes across childhood to adulthood.
Related Concept Videos
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 01:28
Development of the Oral Microbiota
 02:20
Longitudinal Research
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...
 01:20
Lifestyle Factors and Health
Benefits of Physical Activity
Physical activity, whether through structured exercise or casual activities like walking, biking, or dancing, is a cornerstone of a...