Continuous and noninvasive hemoglobin monitoring reduces red blood cell transfusion during neurosurgery: a prospective cohort study
Related Experiment Video
Updated: Apr 17, 2026
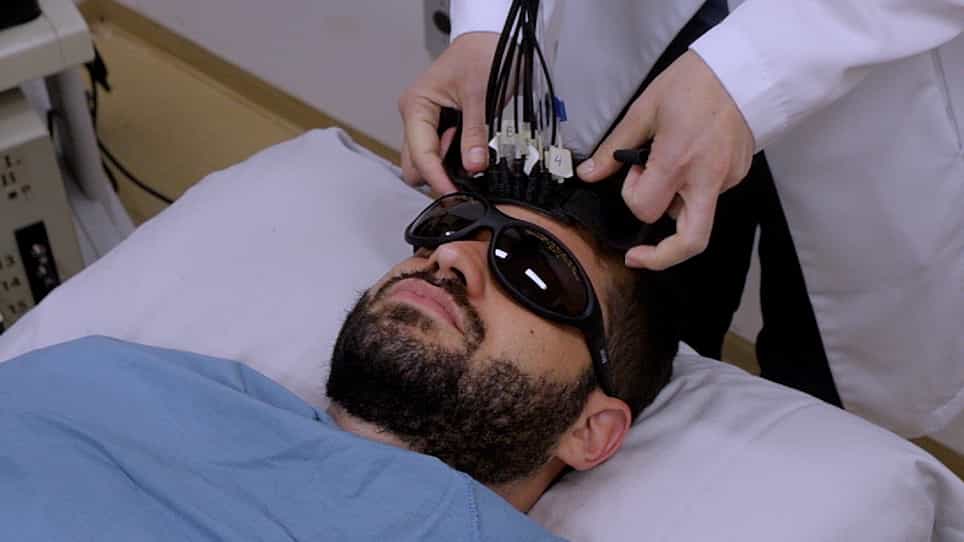
Real-Time Monitoring of Neurocritical Patients with Diffuse Optical Spectroscopies
Published on: November 19, 2020
Wael N Awada1, Maher F Mohmoued2, Tarek M Radwan3
1Department of Anesthesia, ICU and Pain Management, Cairo University, Manyal, Cairo, Egypt. waoool@hotmail.com.

Continuous, noninvasive hemoglobin (SpHb) monitoring provides clinicians with the trending of changes in hemoglobin, which has the potential to alter red blood cell transfusion decision making. The objective of this study was to evaluate the impact of SpHb monitoring on blood transfusions in high blood loss surgery. In this prospective cohort study, eligible patients scheduled for neurosurgery were enrolled into either a Control Group or an intervention group (SpHb Group). The Control Group received intraoperative hemoglobin monitoring by intermittent blood sampling when there was an estimated 15% blood loss. If the laboratory value indicated a hemoglobin level of ≤10 g/dL, a red blood cell transfusion was started and continued until the estimated blood loss was replaced and a laboratory hemoglobin value was >l0 g/dL. In the SpHb Group patients were monitored with a Radical-7 Pulse CO-Oximeter for continuous noninvasive hemoglobin values. Transfusion was started when the SpHb value fell to ≤l0 g/dL and was continued until the SpHb was ≥l0 g/dL. Blood samples were taken pre and post transfusion. Percent of patients transfused, average amount of blood transfused in those who received transfusions and the delay time from the hemoglobin reading of <10 g/dL to the start of transfusion (transfusion delay) were compared between groups. The trending ability of SpHb, and the bias and precision of SpHb compared to the laboratory hemoglobin were calculated. Compared to the Control Group, the SpHb Group had fewer units of blood transfused (1.0 vs 1.9 units for all patients; p ≤ 0.001, and 2.3 vs 3.9 units in patients receiving transfusions; p ≤ 0.0 l), fewer patients receiving >3 units (32 vs 73%; p ≤ 0.01) and a shorter time to transfusion after the need was established (9.2 ± 1.7 vs 50.2 ± 7.9 min; p ≤ 0.00 l). The absolute accuracy of SpHb was 0.0 ± 0.8 g/dL and trend accuracy yielded a coefficient of determination of 0.93. Adding SpHb monitoring to standard of care blood management resulted in decreased blood utilization in high blood loss neurosurgery, while facilitating earlier transfusions.
Continuous, noninvasive hemoglobin (SpHb) monitoring provides clinicians with the trending of changes in hemoglobin, which has the potential to alter red blood cell transfusion decision making. The objective of this study was to evaluate the impact of SpHb monitoring on blood transfusions in high blood loss surgery. In this prospective cohort study, eligible patients scheduled for neurosurgery were enrolled into either a Control Group or an intervention group (SpHb Group). The Control Group received intraoperative hemoglobin monitoring by intermittent blood sampling when there was an estimated 15% blood loss. If the laboratory value indicated a hemoglobin level of ≤10 g/dL, a red blood cell transfusion was started and continued until the estimated blood loss was replaced and a laboratory hemoglobin value was >l0 g/dL. In the SpHb Group patients were monitored with a Radical-7 Pulse CO-Oximeter for continuous noninvasive hemoglobin values. Transfusion was started when the SpHb value fell to ≤l0 g/dL and was continued until the SpHb was ≥l0 g/dL. Blood samples were taken pre and post transfusion. Percent of patients transfused, average amount of blood transfused in those who received transfusions and the delay time from the hemoglobin reading of <10 g/dL to the start of transfusion (transfusion delay) were compared between groups. The trending ability of SpHb, and the bias and precision of SpHb compared to the laboratory hemoglobin were calculated. Compared to the Control Group, the SpHb Group had fewer units of blood transfused (1.0 vs 1.9 units for all patients; p ≤ 0.001, and 2.3 vs 3.9 units in patients receiving transfusions; p ≤ 0.0 l), fewer patients receiving >3 units (32 vs 73%; p ≤ 0.01) and a shorter time to transfusion after the need was established (9.2 ± 1.7 vs 50.2 ± 7.9 min; p ≤ 0.00 l). The absolute accuracy of SpHb was 0.0 ± 0.8 g/dL and trend accuracy yielded a coefficient of determination of 0.93. Adding SpHb monitoring to standard of care blood management resulted in decreased blood utilization in high blood loss neurosurgery, while facilitating earlier transfusions.
More Related Videos
 05:23
Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
 07:24
A Precision Medicine Tool for Measurement and Monitoring of Hemoglobin S in Sickle Cell Disease Patients Receiving Transfusion Therapy
