Related Experiment Video
Updated: Apr 17, 2026

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Prevention and treatment of hemorrhage during laparoscopic splenectomy and devascularization for portal hypertension
Wen-Jing Wang1, Yong Tang1, Yu Zhang1
1Department of Hepatobiliary Surgery, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan, 430022, China.

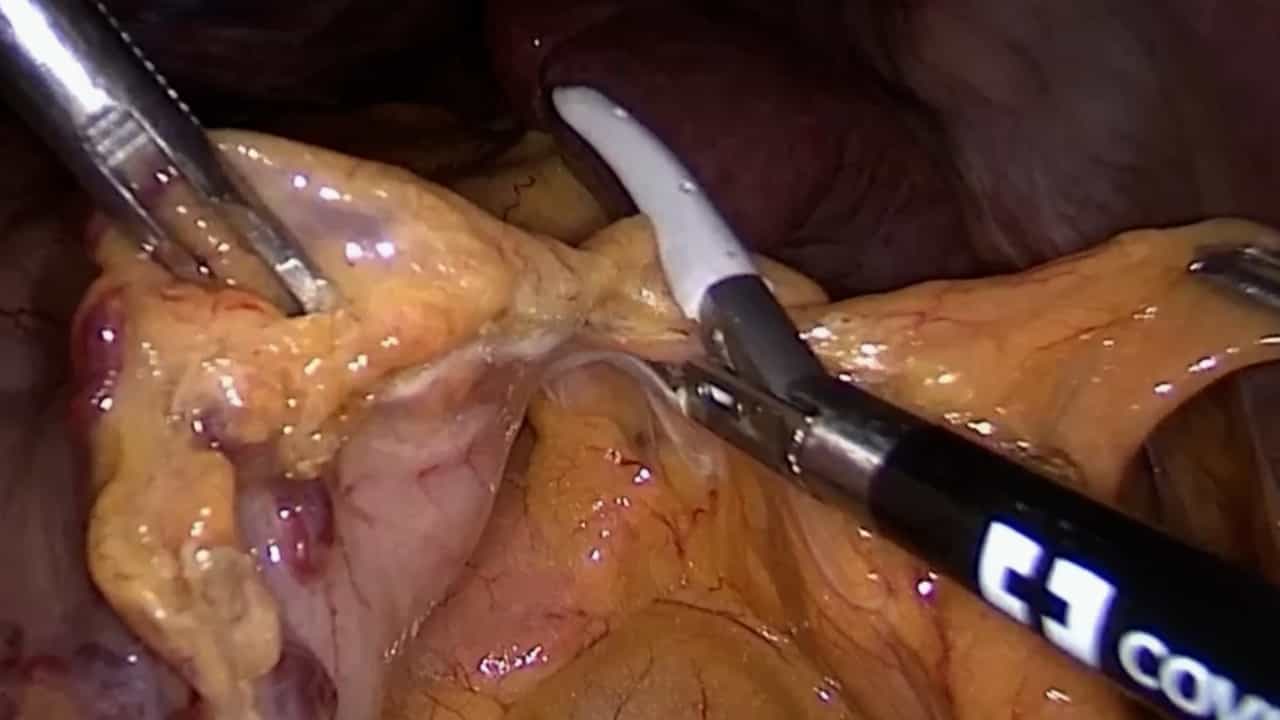
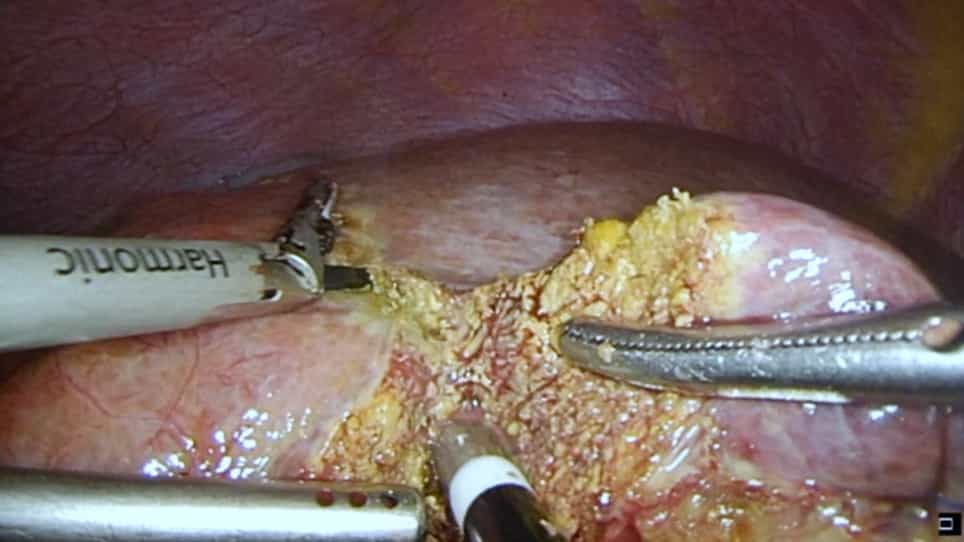
This study was aimed to explore prevention and treatment of hemorrhage during laparoscopic splenectomy plus devascularization (LSD) for portal hypertension by modified and simplified operation. From June 2012 to June 2014, LSD was performed on 138 patients with portal hypertension. The patients were allocated into two groups: earlier stage (ES) group, in which 45 patients received traditional LSD from June 2012 to Sep. 2012; later stage (LS) group, in which 93 patients underwent modified LSD from Jan. 2013 to June 2014. Perioperative variables were compared between the two groups. Laparoscopic operations were successfully performed in all but two patients in ES group who were converted to laparotomy (total conversion rate: 1.4%). There was no perioperative death or reoperation, and all patients recovered and were discharged from hospital with no serious complications in the six months of postoperative follow-up. The average time in the ES group was longer than that in the LS group (335.1 min vs. 201.3 min, P<0.05). LS group outperformed ES group in terms of blood loss (705.4 mL vs. 910.4 mL, P<0.05). The average operation time to oral diet intake after surgery (40.5 h vs. 50.3 h, P<0.05) and postoperative hospital stay (7.4 d vs. 9.0 days, P<0.05) were much less in the LS group than in the ES group. The overall complication rate (4.3 % vs. 11.1 %, P<0.05) and conversion rate (0% vs. 4.4%, P<0.05) were lower in the LS group than in the ES group. It was concluded that prevention and treatment of hemorrhage are the key points of LSD for portal hypertension. By creating a tunnel above the splenic pedicle and a tunnel behind the lower esophagus, the simplified and modified LSD can reduce hemorrhage and improve success of surgery dramatically, and splenomegaly and severe varices are not contraindications.
This study was aimed to explore prevention and treatment of hemorrhage during laparoscopic splenectomy plus devascularization (LSD) for portal hypertension by modified and simplified operation. From June 2012 to June 2014, LSD was performed on 138 patients with portal hypertension. The patients were allocated into two groups: earlier stage (ES) group, in which 45 patients received traditional LSD from June 2012 to Sep. 2012; later stage (LS) group, in which 93 patients underwent modified LSD from Jan. 2013 to June 2014. Perioperative variables were compared between the two groups. Laparoscopic operations were successfully performed in all but two patients in ES group who were converted to laparotomy (total conversion rate: 1.4%). There was no perioperative death or reoperation, and all patients recovered and were discharged from hospital with no serious complications in the six months of postoperative follow-up. The average time in the ES group was longer than that in the LS group (335.1 min vs. 201.3 min, P<0.05). LS group outperformed ES group in terms of blood loss (705.4 mL vs. 910.4 mL, P<0.05). The average operation time to oral diet intake after surgery (40.5 h vs. 50.3 h, P<0.05) and postoperative hospital stay (7.4 d vs. 9.0 days, P<0.05) were much less in the LS group than in the ES group. The overall complication rate (4.3 % vs. 11.1 %, P<0.05) and conversion rate (0% vs. 4.4%, P<0.05) were lower in the LS group than in the ES group. It was concluded that prevention and treatment of hemorrhage are the key points of LSD for portal hypertension. By creating a tunnel above the splenic pedicle and a tunnel behind the lower esophagus, the simplified and modified LSD can reduce hemorrhage and improve success of surgery dramatically, and splenomegaly and severe varices are not contraindications.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Venous Thrombosis IV: Nursing Management
 01:22
Portal Hypertension