Related Experiment Video
Updated: Apr 17, 2026

Recurrent Escherichia coli Urinary Tract Infection Triggered by Gardnerella vaginalis Bladder Exposure in Mice
Published on: December 4, 2020
Elevated postvoid residual urine volume predicting recurrence of urinary tract infections in toilet-trained children
Shang-Jen Chang1, Li-Ping Tsai, Chun-Kai Hsu
1Division of Urology, Taipei Tzu Chi Hospital, Buddhist Tzu Chi Medical Foundation, 16F, 289 Chienkuo Road, Xindian, New Taipei, 231, Taiwan.

Insights
Elevated postvoid residual (PVR) urine volume in toilet-trained children with a history of febrile urinary tract infection (fUTI) is a significant predictor of recurrent fUTI. Monitoring and managing elevated PVR is crucial for preventing further infections.
Area of Science:
- Pediatric Nephrology
- Urology
- Infectious Diseases
Background:
- Febrile urinary tract infections (fUTI) can lead to recurrent infections in children.
- Postvoid residual (PVR) urine volume is a potential indicator of lower urinary tract dysfunction.
- A new PVR nomogram has been proposed to better define elevated PVR in children.
Purpose of the Study:
- To investigate if elevated PVR, as defined by a new nomogram, increases the risk of recurrent fUTI in toilet-trained children.
- To identify independent risk factors for UTI recurrence in this pediatric population.
Main Methods:
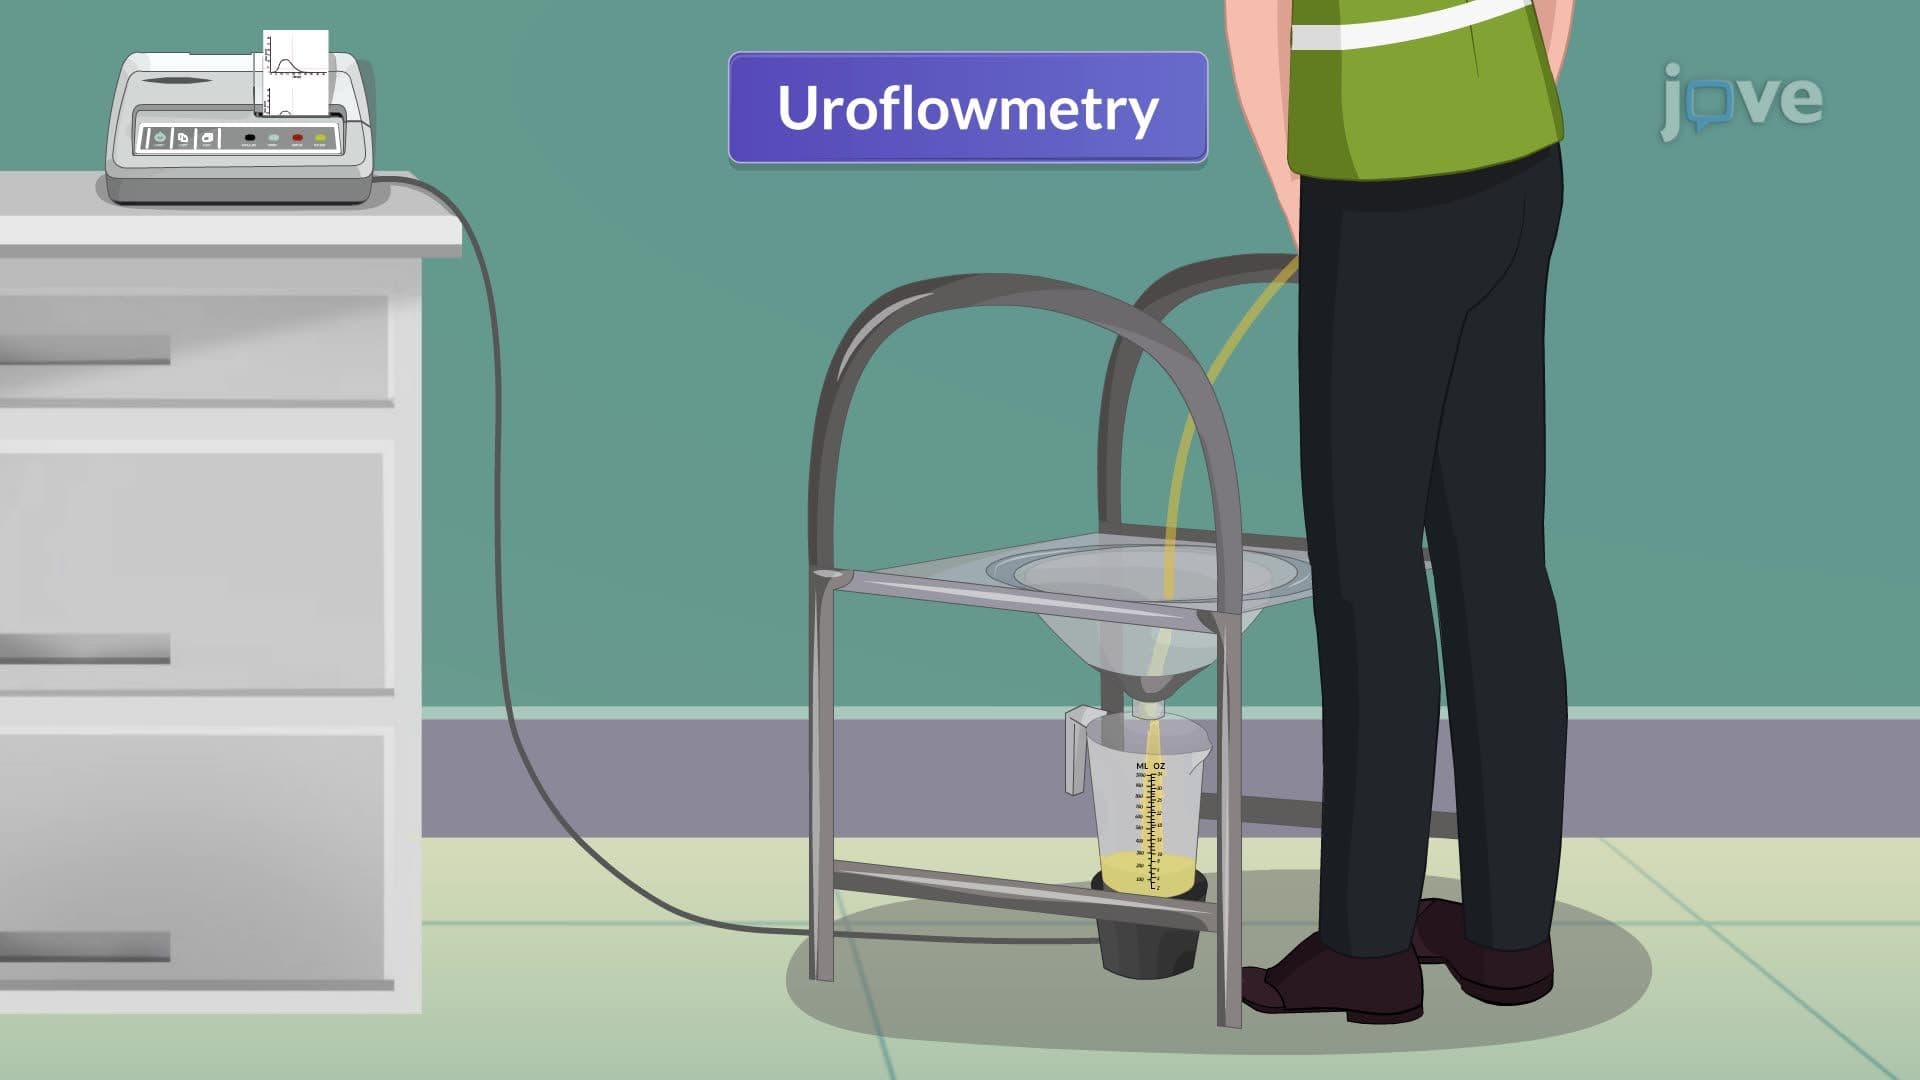
- Children with a history of fUTI underwent uroflowmetry and PVR assessment via ultrasonography.
- Elevated PVR was defined based on age-specific thresholds from the new nomogram.
- Cox proportional hazards regression analysis was employed to determine risk factors for UTI recurrence.
Main Results:
- Younger age and elevated PVR were identified as significant, independent risk factors for recurrent fUTI.
- Elevated PVR showed a hazard ratio of 2.88 (p=0.01) for recurrent fUTI.
- Constipation and high-grade vesicoureteral reflux (VUR) were not found to be independent predictors of recurrent fUTI in this cohort.
Conclusions:
- The new PVR nomogram effectively predicts recurrent UTI in children with a history of fUTI.
- Elevated PVR is a critical factor to consider in the management of children at risk for recurrent UTIs.
- Clinical attention should be directed towards managing elevated PVR in pediatric patients to prevent UTI recurrence.
Background:
The aim of this study was to examine whether toilet-trained children with a history of febrile urinary tract infection (fUTI) and elevated postvoid residual (PVR) urine volume according to a recently published PVR nomogram were at greater risk of UTI recurrence.
Materials And Methods:
One month after recovery from febrile UTI, constipation was diagnosed according to the Rome III criteria, and lower urinary tract (LUT) function was evaluated with two sets of uroflowmetry and PVR by ultrasonography. For children aged ≦ 6 and ≧ 7 years, elevated PVR is defined as >20 and >10 ml, respectively. Cox proportion hazards regression was used to evaluate the risk factors for recurrence of UTI.
Results:
Between 2005 and 2011, 60 children aged 6.5 ± 2.5 years (boy:girl ratio 27:33) were enrolled for analysis. Univariate analysis showed that recurrent febrile UTI was more commonly observed in children with elevated PVR [repetitive elevated PVR: hazard ratio (HR) 5.75, 95% confidence interval (CI) 1.41-23.4; one elevated PVR: HR 4.53, 95% CI 1.01-20.2] and high-grade vesicoureteral reflux (VUR; HR 4.53, 95% CI 1.46-14.07). Multivariate analysis showed that younger age (HR 1.37, 95% CI 1.03-1.82, p < 0.01) and elevated PVR (HR 2.88, 95% CI 1.44-5.73, p = 0.01) were significant, independent risk factors for recurrent febrile UTI--but not gender, presence of high-grade VUR and constipation.
Conclusion:
Elevated PVR defined by the new PVR nomogram predicted recurrent UTI in children with history of febrile UTI. Care should be taken to manage children with elevated PVR.

Related Concept Videos
 01:19
Urodynamic Studies: Uroflowmetry
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:17
Urinary Tract Infection IV: Nursing Management
 01:25
Urinary Tract Infection II: Pathophysiology
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:30
Urinary Tract Calculi III: Medical Management