Related Experiment Video
Updated: Apr 17, 2026


Voluntary Breath-hold Technique for Reducing Heart Dose in Left Breast Radiotherapy
Published on: July 3, 2014
Breath-holding spells in infants

Insights
Breath-holding spells are common in healthy children aged 6–48 months, presenting as benign, seizure-like episodes. Diagnosis requires an electrocardiogram and anemia screening, with no further investigation needed.
Area of Science:
- Pediatric Neurology
- Child Development
Background:
- Seizure-like episodes, including cyanosis and loss of consciousness, can occur in children.
- These episodes are often concerning for parents and may lead to unnecessary medical investigations.
Purpose of the Study:
- To determine the prevalence and characteristics of breath-holding spells in children.
- To clarify the necessary diagnostic investigations for breath-holding spells.
Main Methods:
- Clinical diagnosis based on patient history and observed episodes.
- Recommended investigations include electrocardiogram and anemia screening.
Main Results:
- Breath-holding spells are a common, benign, nonepileptic disorder in children aged 6 to 48 months.
- Episodes are triggered by emotional upset or minor injury and can involve cyanosis and syncope.
- These episodes, while frightening, have benign outcomes.
Conclusions:
- Breath-holding spells are a distinct clinical entity requiring a clinical diagnosis.
- Electrocardiogram and anemia screening are recommended to rule out other conditions.
- No further extensive investigations or specialist referrals are typically warranted after a clinical diagnosis.
Question:
I have children in my clinic who experience seizurelike episodes in which they cry and hold their breath to the point of cyanosis and loss of consciousness. Their examination or investigation findings are normal and referral to a pediatric specialist results in no further investigation. Are breath-holding spells common, and what type of investigation is needed?
Answer:
A breath-holding spell is a benign paroxysmal nonepileptic disorder occurring in healthy children 6 to 48 months of age. The episodes start with a provocation such as emotional upset or minor injury, and might progress to breath holding, cyanosis, and syncope. The episodes are extremely frightening to watch but have benign consequences. Once a clinical diagnosis is made, it is recommended to conduct an electrocardiogram and to rule out anemia, but no further investigation or referral is warranted.


Related Concept Videos
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:21
Mechanism of Breathing III: The Accessory Muscles
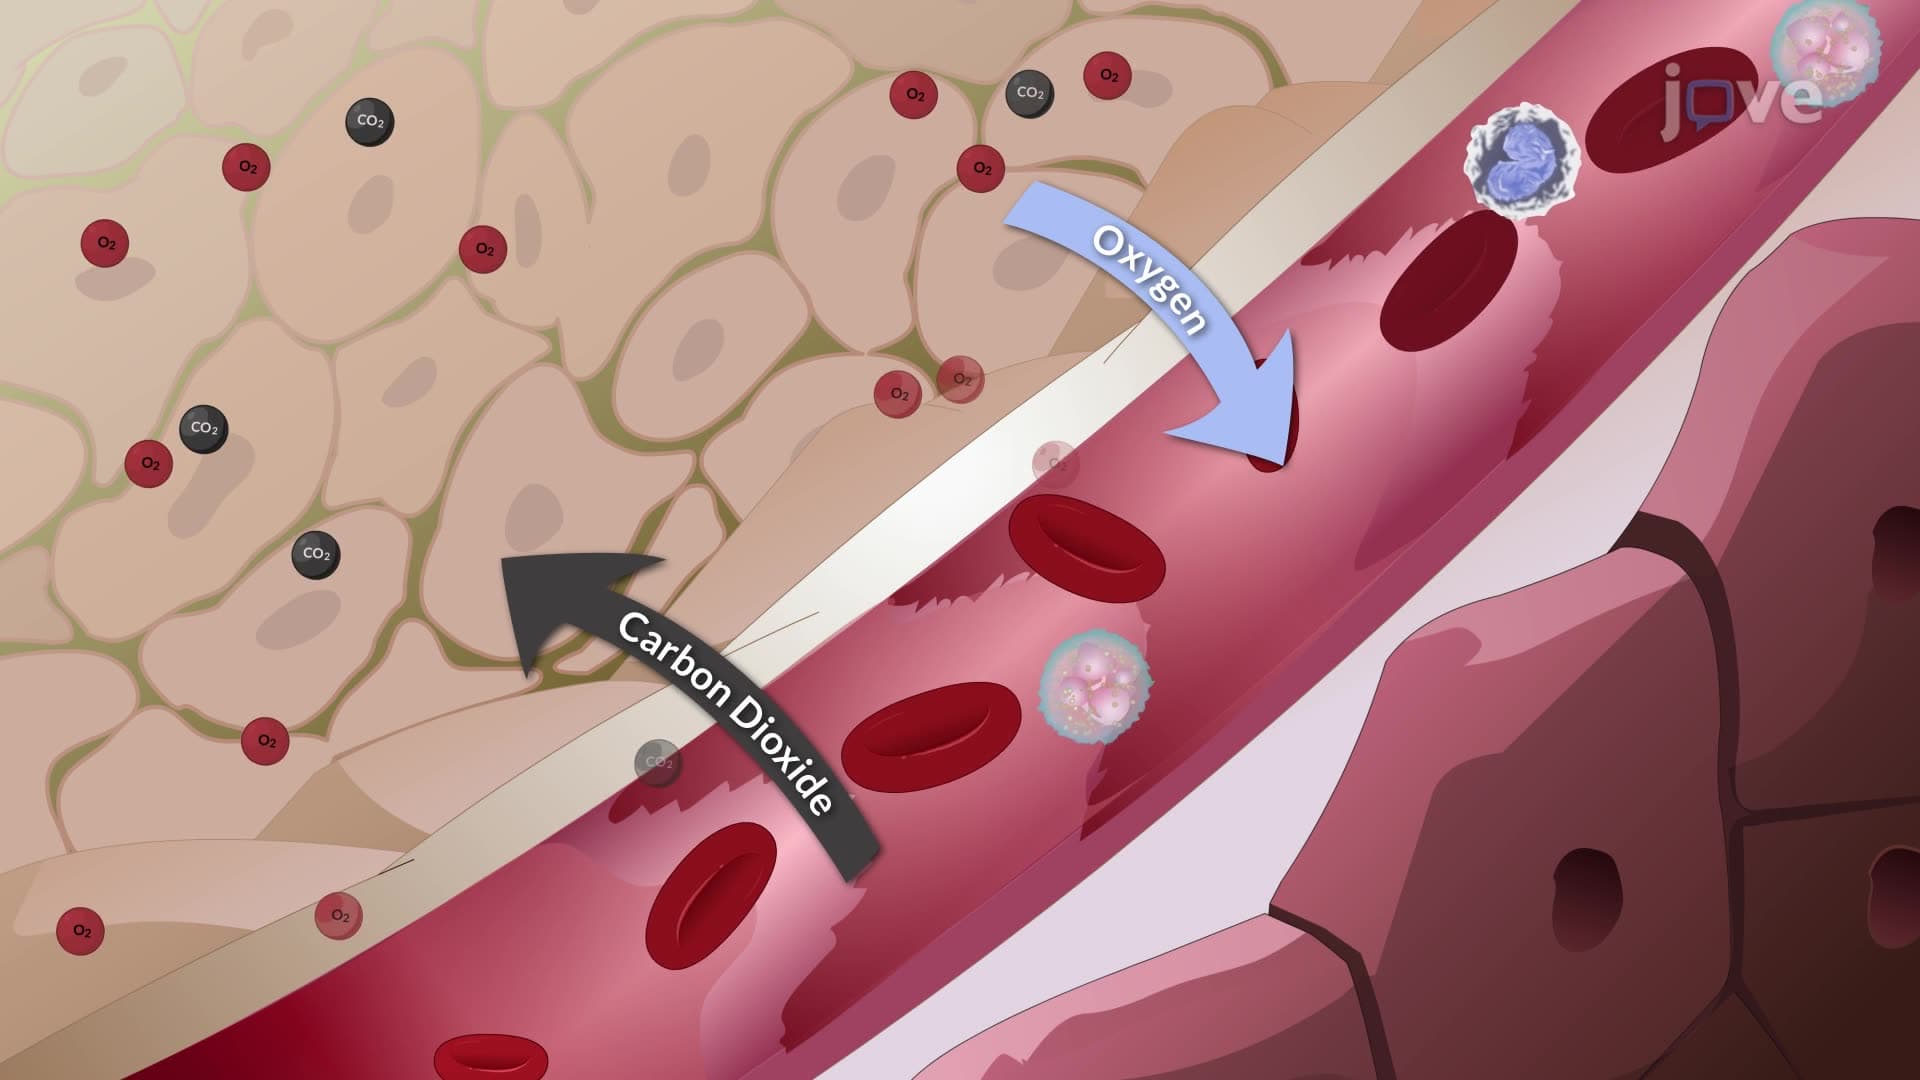
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:26
Respiratory Volumes and Capacities I