Exploration of Withdrawal of Life-Sustaining Therapy in Canadian Intensive Care Units
Related Experiment Video
Updated: Apr 17, 2026
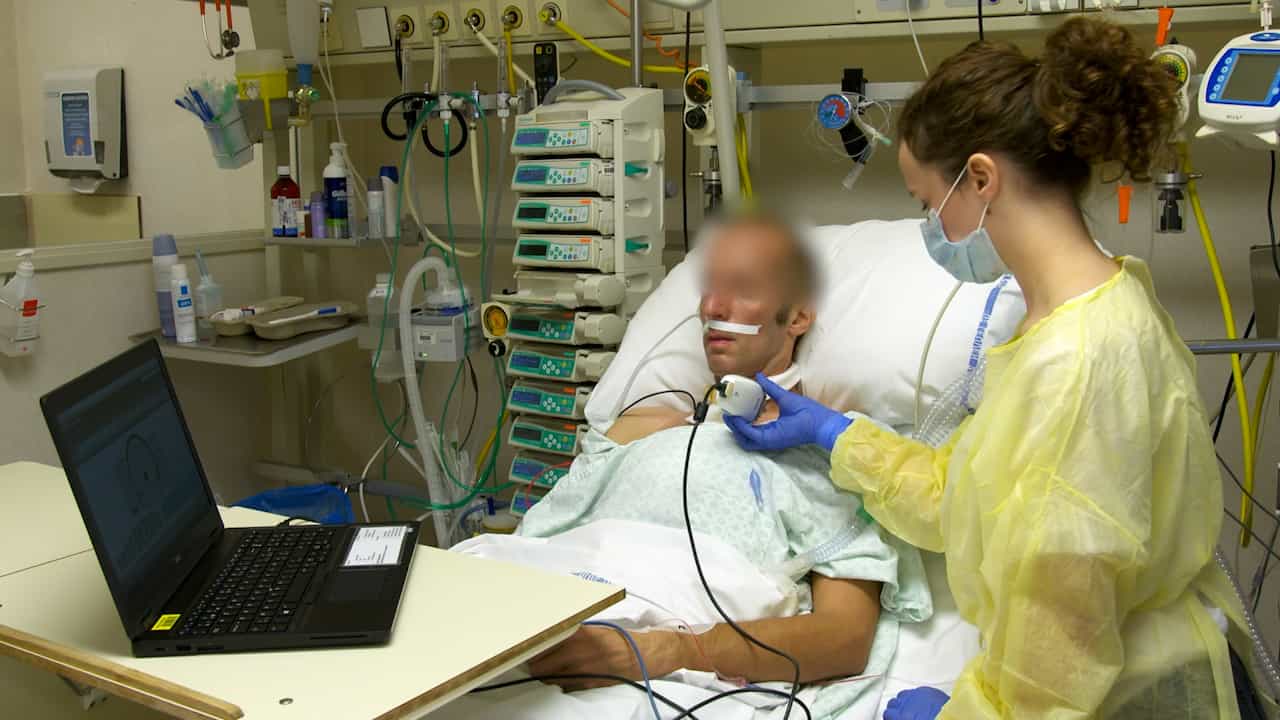
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Amanda van Beinum1, Laura Hornby2, Tim Ramsay3
1Department of Epidemiology and Community Medicine, University of Ottawa, Ottawa, Canada amandavb4@gmail.com.

Objective:
The process of controlled donation after circulatory death (cDCD) is strongly connected with the process of withdrawal of life-sustaining therapy. In addition to impacting cDCD success, actions comprising withdrawal of life-sustaining therapy have implications for quality of palliative care. We examined pilot study data from Canadian intensive care units to explore current practices of life-sustaining therapy withdrawal in nondonor patients and described variability in standard practice.
Design:
Secondary analysis of observational data collected for Determination of Death Practices in Intensive Care pilot study.
Setting:
Four Canadian adult intensive care units.
Patients:
Patients ≥18 years in whom a decision to withdraw life-sustaining therapy was made and substitute decision makers consented to study participation. Organ donors were excluded.
Interventions:
None.
Measurements And Main Results:
Prospective observational data on interventions withdrawn, drugs administered, and timing of life-sustaining therapy withdrawal was available for 36 patients who participated in the pilot study. Of the patients, 42% died in ≤1 hour; median length of time to death varied between intensive care units (39-390 minutes). Withdrawal of life-sustaining therapy processes appeared to follow a general pattern of vasoactive drug withdrawal followed by withdrawal of mechanical ventilation and extubation in most sites but specific steps varied. Approaches to extubation and weaning of vasoactive drugs were not consistent. Protocols detailing the process of life-sustaining therapy withdrawal were available for 3 of 4 sites and also exhibited differences across sites.
Conclusions:
Standard practice of life-sustaining therapy withdrawal appears to differ between selected Canadian sites. Variability in withdrawal of life-sustaining therapy may have a potential impact both on rates of cDCD success and quality of palliative care.
More Related Videos
 06:59
A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
 06:04
Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
Related Concept Videos
 01:27
Ethical Issues
Ethical Concerns in Healthcare:
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:19
Restorative Care
 01:22
Heart Failure VI: Adjunct Therapies
 01:30
Continuous Renal Replacement Therapy
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's...