Related Experiment Video
Updated: Apr 17, 2026
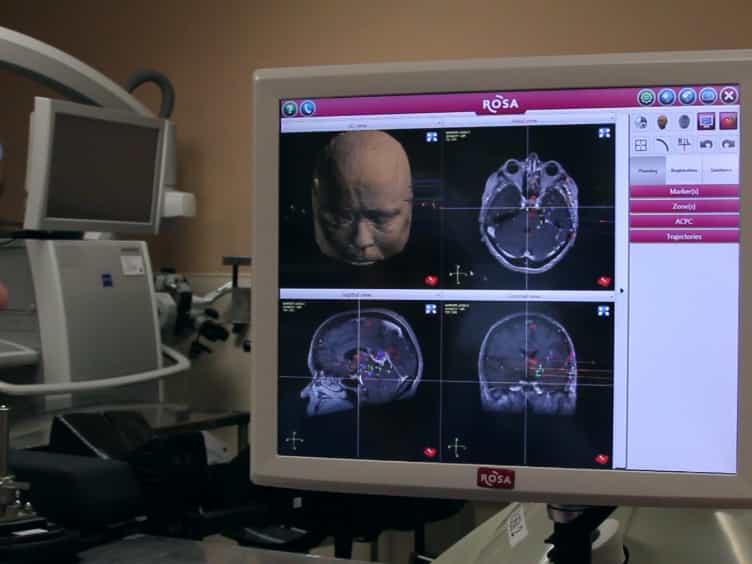
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
Optimizations and Nuances in Neurosurgical Technique for the Minimization of Complications in Subdural Electrode
Steven M Falowski1, Daniel J DiLorenzo2, Larry R Shannon3
1Department of Neurosurgery, Rush University Medical Center, Chicago, Illinois, USA; St. Luke's Neurosurgical Associates, Bethlehem, Pennsylvania, USA.

Background:
Surgical intervention is an important therapeutic option for patients with intractable epilepsy and a well-characterized epileptogenic focus. Invasive monitoring with subdural electrodes is an effective technique for localizing epileptogenic foci. Previous studies reported varying complication rates, and these may deter more widespread adoption. We present potentially valuable technical nuances that may be associated with low complication rates. We assess the potential contribution of specific aspects of surgical technique to the reduction of complication rates.
Methods:
We retrospectively reviewed patients from the Rush University Surgical Epilepsy database who underwent craniotomies for invasive electroencephalography monitoring for medically intractable epilepsy using our technique. We analyzed and compared complication rates and techniques with those reported elsewhere.
Results:
The sample group comprised 127 consecutive patients who underwent electrode implantation. The average monitoring period was 6 days. There were 5 complications (3.9%), including 1 subdural hematoma requiring surgery (0.8%), 1 infection (0.8%), 2 pulmonary emboli (1.6%), and 1 deep vein thrombosis (0.8%). There were no symptomatic cerebrospinal fluid leaks or permanent neurologic complications. These results compare favorably with published results. Analysis and comparison of our technique anecdotally suggest the importance of use of a subgaleal drain throughout the monitoring period, postoperative antibiotic coverage for 1 week, meticulous hemostasis, and secure suturing of the electrodes to the dura mater to minimize trauma to superficial vessels as potential contributors to improved complication rates.
Conclusions:
A very low incidence of major morbidity can be achieved in invasive electroencephalography monitoring with this protocol.
More Related Videos
 08:11
Surgical Training for the Implantation of Neocortical Microelectrode Arrays Using a Formaldehyde-fixed Human Cadaver Model
Published on: November 19, 2017
 09:00
Investigating the Function of Deep Cortical and Subcortical Structures Using Stereotactic Electroencephalography: Lessons from the Anterior Cingulate Cortex
Published on: April 15, 2015