Related Experiment Video
Updated: Aug 11, 2026
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Effect of CGP 17/582, a selective beta-adrenoceptor antagonist, on the haemodynamic and hypokalaemic response to
K F Whyte1, P J De Vane, R Whitesmith
1Department of Materia Medica, University of Glasgow.

Abstract:
1. CGP 17/582B is a new beta-adrenoceptor antagonist which on experimental studies appears to combine selective beta 1-adrenoceptor blockade with partial agonist activity (ISA). Assessing beta-adrenoceptor selectivity and the degree of partial agonist activity in vivo can be difficult. 2. In a double-blind placebo controlled crossover study we have compared the effect of oral pretreatment for 7 days with CGP (100 mg twice daily), with propranolol (non-selective beta-adrenoceptor blocker with no ISA) and metoprolol (selective beta-adrenoceptor blocker with no ISA) on resting heart rate and heart rate response to submaximal exercise on a bicycle ergometer to assess the degree of beta-adrenoceptor blockade and also the changes in blood pressure, heart rate and potassium during the intravenous infusion of (-)-adrenaline to determine the degree of beta 2-adrenoceptor blockade. 3. Subjects underwent submaximal exercise testing on the second and fifth day of each treatment period and on the seventh day received a 2 h infusion of (-)-adrenaline (0.06 microgram kg-1 min-1). Heart rate, blood pressure, plasma potassium and catecholamines were measured throughout the study period. 4. All three active treatments significantly reduced exercise induced tachycardia. The (-)-adrenaline infusion significantly reduced plasma noradrenaline levels following propranolol and metoprolol and to a lesser extent with placebo but were unaltered on CGP. Baseline heart rate was unaltered by CGP but was significantly reduced by metoprolol and propranolol. Adrenaline significantly reduced plasma potassium levels following placebo and CGP pretreatment but plasma potassium was unaltered by adrenaline with metoprolol and propranolol pretreatment.(ABSTRACT TRUNCATED AT 250 WORDS)

Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:26
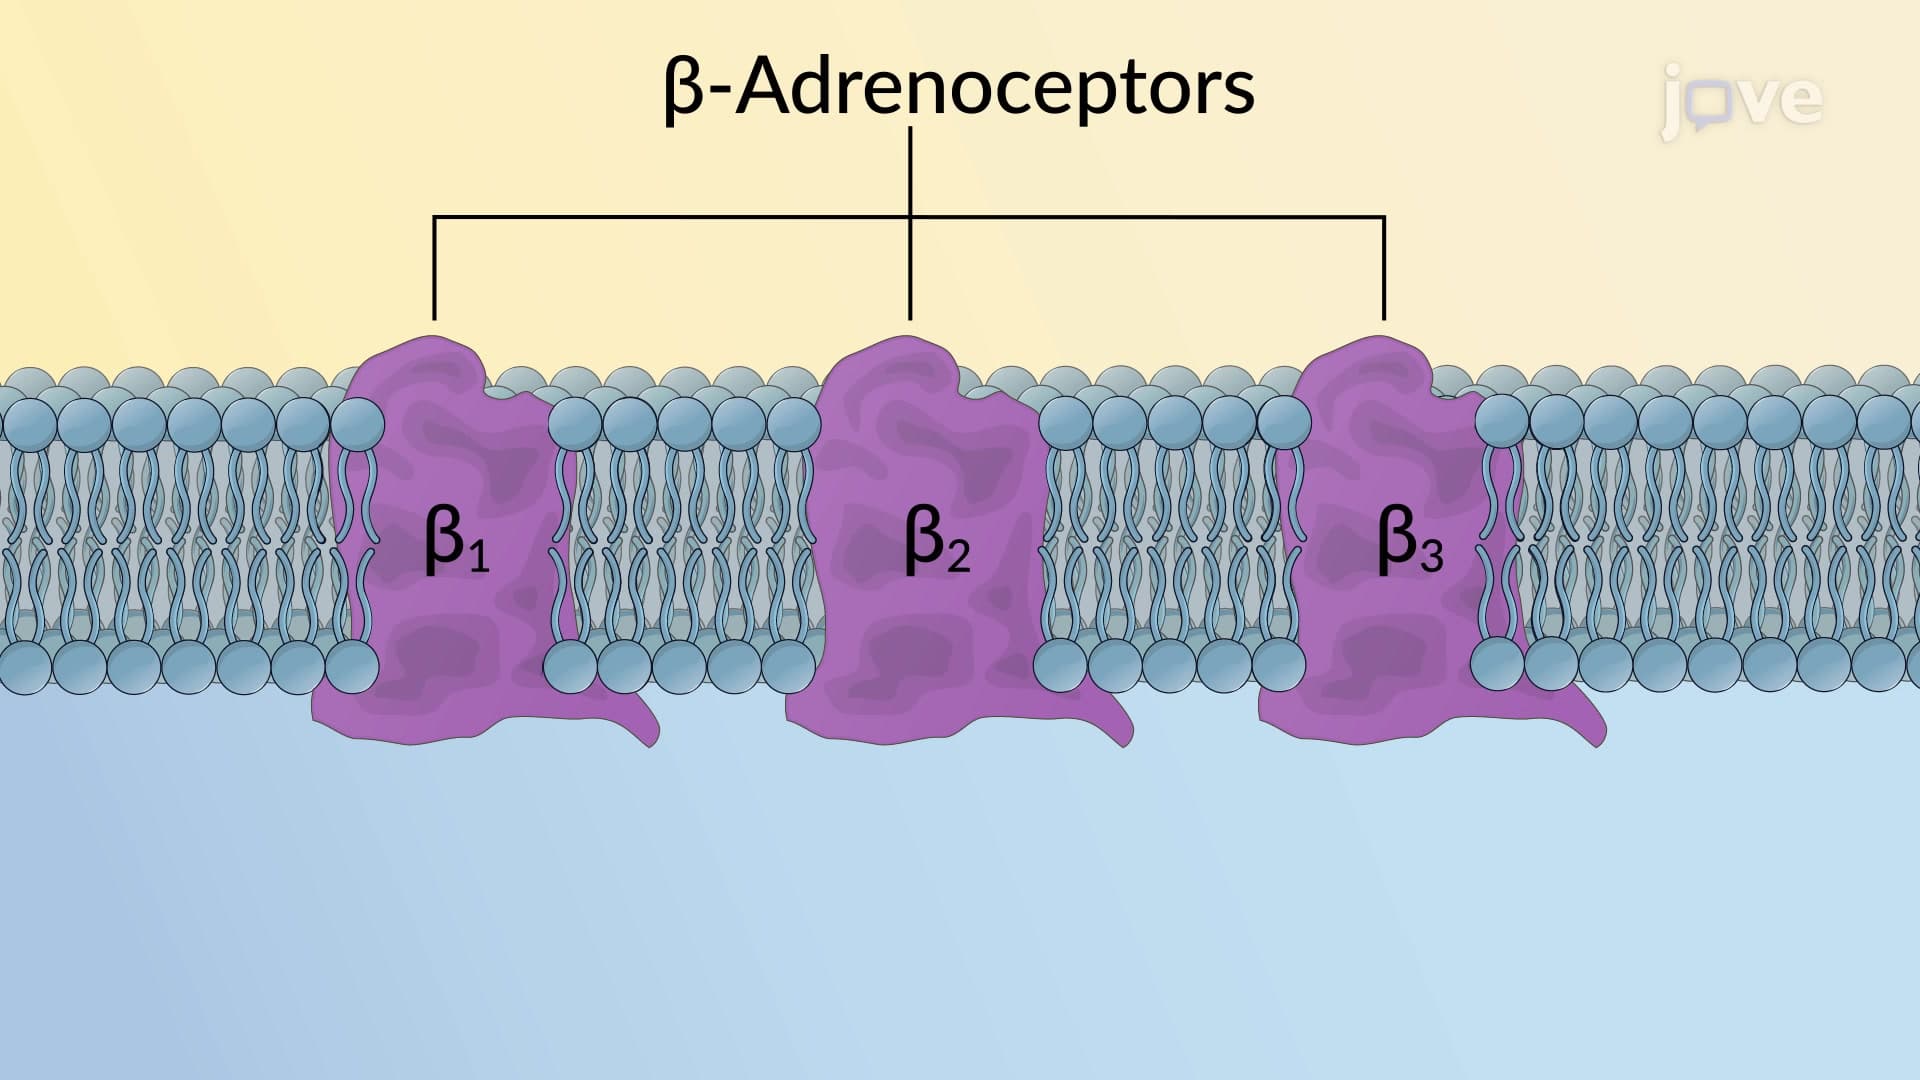
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers