Related Experiment Video
Updated: Apr 17, 2026

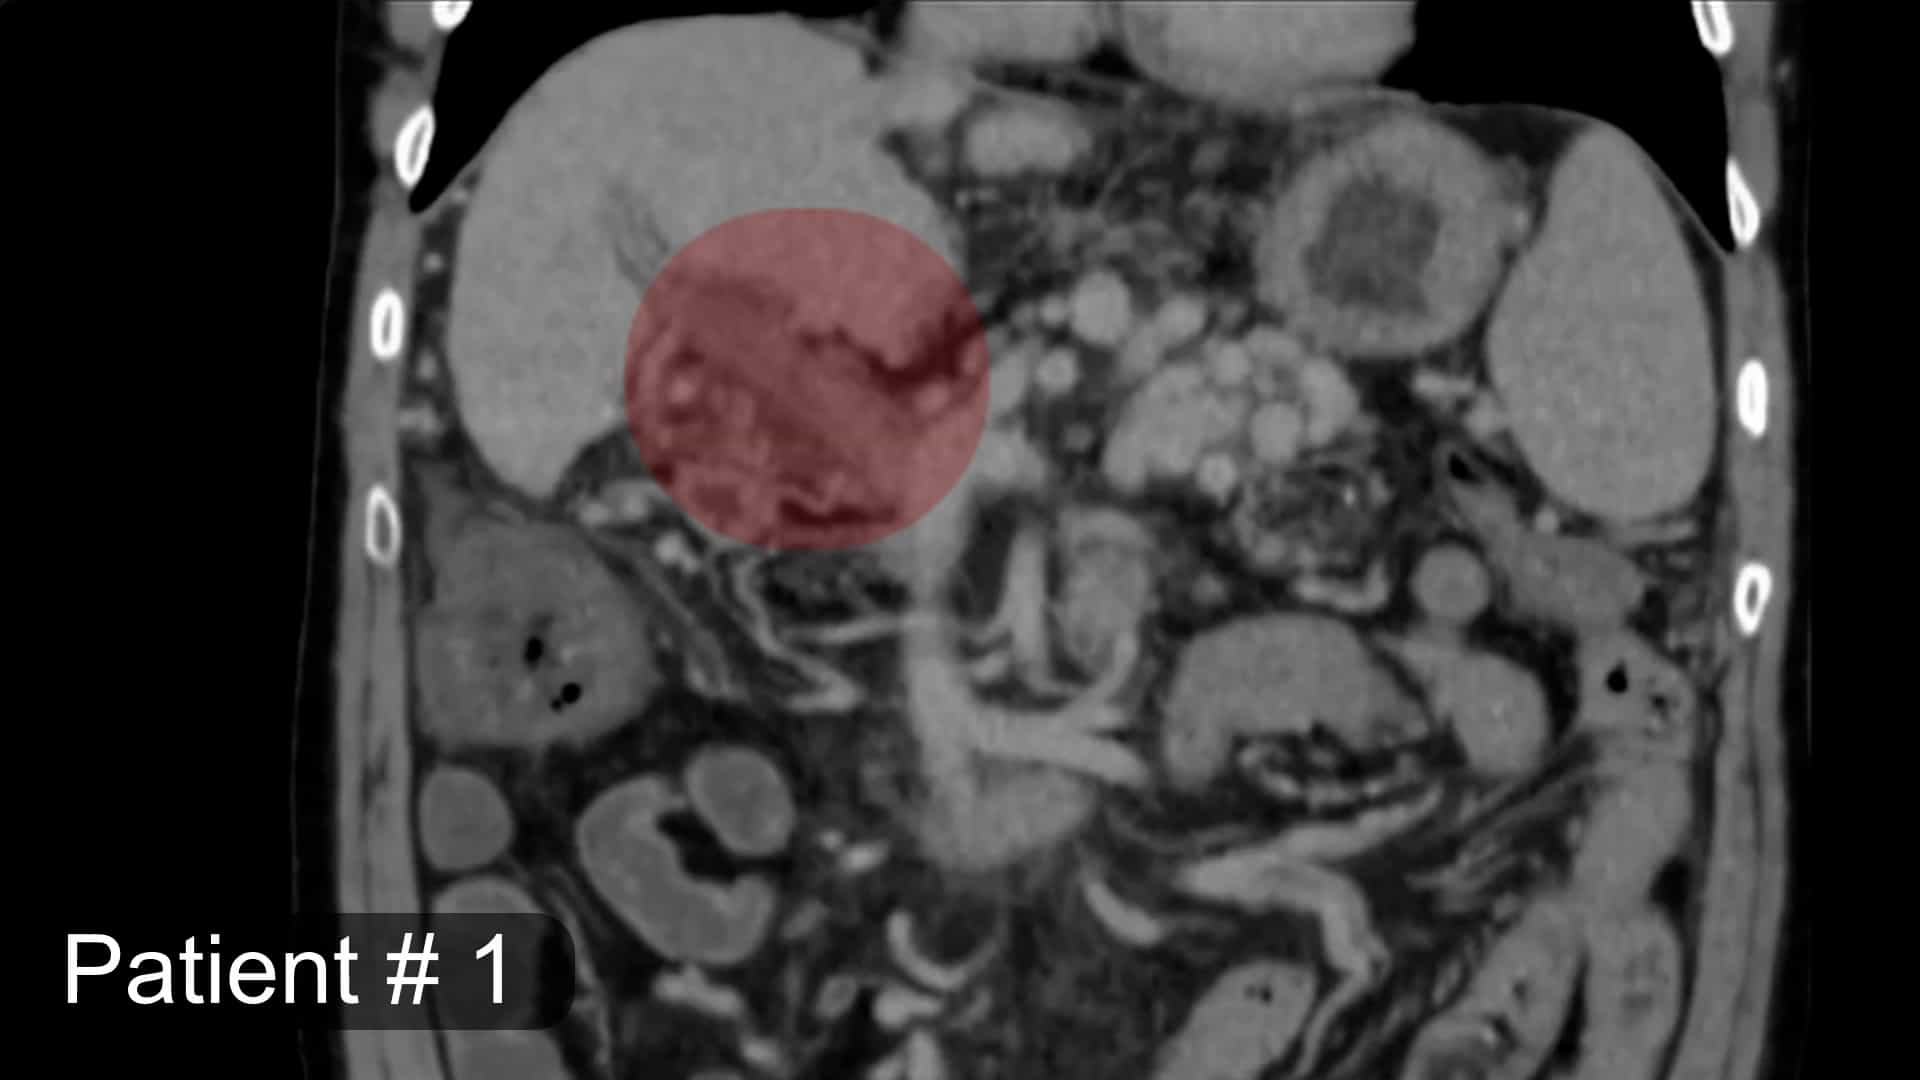
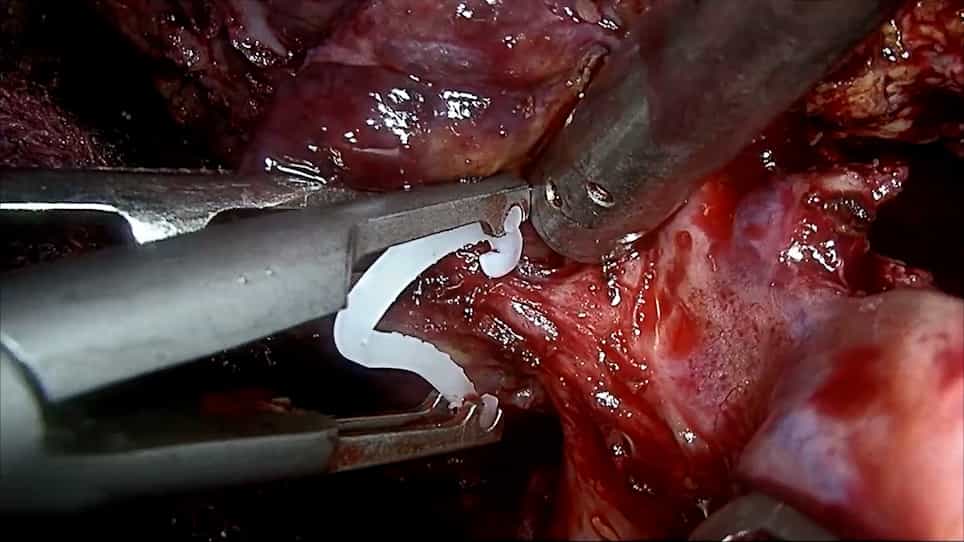
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
A comparative study of two anti-coagulation plans on the prevention of PVST after laparoscopic splenectomy and
1Institute of Hepatobiliary Surgery, Southwest Hospital, Third Military Medical University, Gaotanyan Road 29#, Shapingba District, Chongqing, 400038, China.

Insights
Early use of low molecular weight heparin (LMWH) significantly reduces portal vein system thrombosis (PVST) after laparoscopic surgery for cirrhosis and portal hypertension. This safe and effective approach improves patient outcomes by lowering complication rates.
Area of Science:
- Hepatology
- Gastroenterology
- Surgical Oncology
Background:
- Cirrhosis and portal hypertension (PH) are prevalent in China.
- Laparoscopic splenectomy and esophagogastric devascularization (LS + ED) is an effective treatment for PH.
- Portal vein system thrombosis (PVST) is a significant complication following LS + ED, with higher rates compared to open surgery.
Purpose of the Study:
- To evaluate the efficacy and safety of early low molecular weight heparin (LMWH) for preventing PVST after LS + ED.
- To compare early LMWH prophylaxis with conventional anticoagulant therapy in patients with cirrhosis and PH undergoing LS + ED.
Main Methods:
- Retrospective analysis of 219 patients with cirrhosis and PH undergoing LS + ED from January 2008 to June 2013.
- 139 patients received early LMWH therapy; 80 patients received conventional anticoagulant therapy.
- Comparison of PVST rates and types, coagulation function, intra-abdominal bleeding, and esophagogastric variceal bleeding (EGVB) between the two groups.
Main Results:
- The rate of postoperative PVST was significantly lower in the early LMWH group (30.2%) compared to the conventional group (50.0%) (P = 0.004).
- Main trunk thrombosis rates were significantly reduced with early LMWH (1.4% vs. 15.0%, P = 0.000).
- Esophagogastric variceal bleeding (EGVB) rates were also significantly lower in the early LMWH group (P = 0.048), with similar perioperative coagulation function and bleeding rates.
Conclusions:
- Early anticoagulation with LMWH is a safe and effective strategy for preventing PVST in patients undergoing LS + ED for cirrhosis and PH.
- This approach significantly reduces the incidence of PVST and related complications like EGVB.
- LMWH prophylaxis offers a promising standard of care for managing PVST risk in this patient population.
Abstract:
Cirrhosis and portal hypertension (PH) has a high incidence in China. Laparoscopic splenectomy and esophagogastric devascularization (LS + ED) was confirmed as an effective and safe surgical approach. But compared to open surgery (OS + ED), the rate of portal vein system thrombosis (PVST) was found to be higher after LS + ED. PVST is a common and potentially life-threatening complication after LS + ED in patients with cirrhosis and PH. Anti-coagulation therapy should be given early, but no standard plan for PSVT prophylaxis has been developed for all patients. In this study, the efficacy and safety of early use of low molecular weight heparin (LMWH) to prevent PVST were retrospectively evaluated compared with conventional anti-coagulant therapy. Of 219 patients with cirrhosis and PH undergoing LS + ED at our hospital from January 2008 to June 2013, 139 received early anti-coagulant therapy with LMWH, and 80 received conventional anti-coagulant therapy. The rates and types of PVST, perioperative coagulation function, intra-abdominal active bleeding, and esophagogastric variceal bleeding (EGVB) were compared in these two groups. Of the 139 patients in the early anti-coagulation group, 42 (30.2 %) experienced postoperative PVST, including two (1.4 %) with main trunk. Of the 80 patients in the conventional anti-coagulation group, 40 (50.0 %) experienced postoperative PVST, including 12 (15.0 %) with main trunk; three (3.8 %) experienced recurrent EGVB due to main trunk thrombosis, and one (1.3 %) underwent an immediate second laparotomy for uncontrollable active bleeding. The rates of postoperative PVST (P = 0.004), main trunk thrombosis (P = 0.000), and EGVB (P = 0.048) were significantly lower in the early than in the conventional anti-coagulant group, but all tested perioperative indices of coagulation function and rates of intraperitoneal active bleeding were similar. Early anti-coagulation with LMWH is safe and effective in patients with LS + ED for cirrhosis and PH.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care