Efficacy of antiplatelet therapy in secondary prevention following lacunar stroke: pooled analysis of randomized trials
Related Experiment Video
Updated: Oct 19, 2026
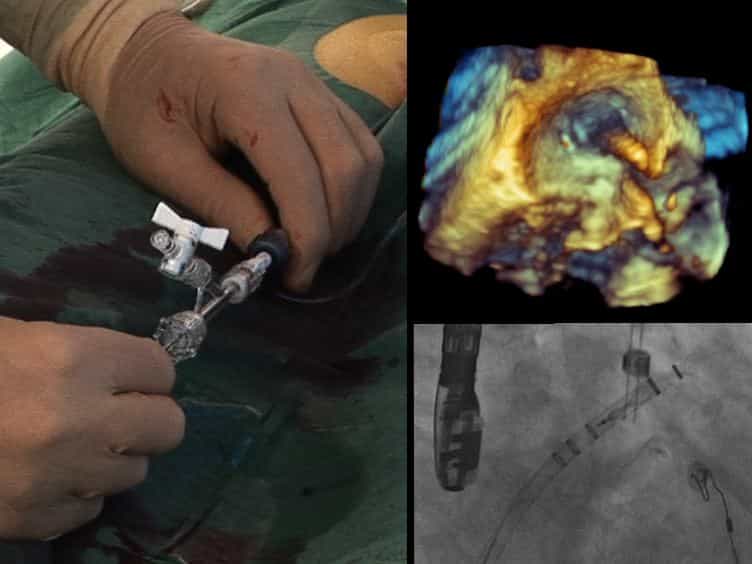
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Chun Shing Kwok1, Ashkan Shoamanesh2, Hannah Charlotte Copley2
1From the Institute of Cardiovascular Sciences, University of Manchester, Manchester, UK (C.S.K.); Institute of Applied Health Sciences, School of Medicine and Dentistry, University of Aberdeen, Aberdeen, Scotland, UK (C.S.K., P.K.M.); Department of Medicine, McMaster University/Population Health Research Institute, Hamilton, Ontario, Canada (A.S.); Department of Surgery, Addenbrooke's Hospital, Cambridge, UK (H.C.C.); Department of Medicine and Health Sciences, Norwich Medical School, University of East Anglia, Norwich Research Park, Norwich, UK (Y.K.L.); and Department of Medicine, Brain Research Centre, University of British Columbia, Vancouver Stroke Program, Vancouver, Canada (O.R.B.). shingkwok@doctors.org.uk.

Background And Purpose:
Lacunar stroke accounts for ≈25% of ischemic stroke, but optimal antiplatelet regimen to prevent stroke recurrence remains unclear. We aimed to evaluate the efficacy of antiplatelet agents in secondary stroke prevention after a lacunar stroke.
Methods:
We searched MEDLINE, Embase, and the Cochrane library for randomized controlled trials that reported risk of recurrent stroke or death with antiplatelet therapy in patients with lacunar stroke. We used random effects meta-analysis and evaluated heterogeneity with I(2).
Results:
We included 17 trials with 42,234 participants (mean age 64.4 years, 65% male) and follow up ranging from 4 weeks to 3.5 years. Compared with placebo, any single antiplatelet agent was associated with a significant reduction in recurrence of any stroke (risk ratio [RR] 0.77, 0.62-0.97, 2 studies) and ischemic stroke (RR 0.48, 0.30-0.78, 2 studies), but not for the composite outcome of any stroke, myocardial infarction, or death (RR 0.89, 0.75-1.05, 2 studies). When other antiplatelet agents (ticlodipine, cilostazol, and dipyridamole) were compared with aspirin, there was no consistent reduction in stroke recurrence (RR 0.91, 0.75-1.10, 3 studies). Dual antiplatelet therapy did not confer clear benefit over monotherapy (any stroke RR 0.83, 0.68-1.00, 3 studies; ischemic stroke RR 0.80, 0.62-1.02, 3 studies; composite outcome RR 0.90, 0.80-1.02, 3 studies).
Conclusions:
Our results suggest that any of the single antiplatelet agents compared with placebo in the included trials is adequate for secondary stroke prevention after lacunar stroke. Dual antiplatelet therapy should not be used for long-term stroke prevention in this stroke subtype.
Related Concept Videos
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:26
Atherosclerosis III: Management
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care