Related Experiment Video
Updated: Apr 16, 2026


In Vivo Real-Time Study of Drug Effects on Carotid Blood Flow in the Ovine Fetus
Published on: April 28, 2023
Theophylline Pharmacokinetics in Foetal Sheep: Maternal Metabolic Capacity is the Principal Driver
Barent DuBois1,2, Samantha Louey3, George D Giraud3,4
1Department of Pharmacy Practice, College of Pharmacy, Oregon State University, Corvallis, OR, USA.

Understanding theophylline pharmacokinetics (PK) in the foetus is essential to prevent in utero toxicity and optimize prophylactic therapies. Previous studies in pregnancy have been obfuscated by maternal dosing and inadequate sampling in the foetus; both render modelling of foetal PK difficult. Six ewes carrying singleton foetuses received theophylline (60 mg) into the foetal jugular vein. Blood samples were drawn from the foetus and ewe over 36 hr. Serum concentrations were measured. Maternal and foetal pharmacokinetic parameters were estimated. Foetal non-compartmental pharmacokinetic parameters were as follows: half-life 7.37 ± 1.22 hr; volume of distribution 44.62 ± 11.45 L; area under the curve 14.82 ± 2.71 hr/(μg/mL); and clearance 4.15 ± 0.70 L/hr. Rapid theophylline distribution across the placenta was observed. Maternal non-compartmental pharmacokinetic parameters were as follows: half-life 6.54 ± 2.44 hr; volume of distribution 32.48 ± 9.99 L; area under the curve 16.28 ± 4.53 hr/(μg/mL); and clearance 3.69 ± 1.47 L/hr. Foetal and ewe serum concentration-time profiles were fit together into a 3-compartment population pharmacokinetic model, and parameters were as follows: central volume 1.38 ± 0.11 L; 2nd peripheral compartment volume 3.11 ± 0.29 L; 3rd peripheral compartment volume 60.14 ± 6.02 L; elimination clearance 9.89 ± 0.90 L/hr; distribution clearance between central and 2nd compartment 30.87 ± 2.31 L/hr; and distribution clearance between 2nd and 3rd compartments 13.89 ± 1.11 L/hr. Cytochrome P4501A expression was robust in maternal liver; negligible activities were observed in placenta, foetal liver and foetal kidney. In vitro protein binding of theophylline was 30% lower in foetal serum compared to maternal serum (29.7 ± 4.4 versus 42.0 ± 3.6%-bound). Free concentrations were lower in the foetus than in the ewe, suggesting active transport across placenta. In summary, foetal clearance of theophylline is attributable to rapid distribution into the maternal circulation across the placenta followed by greater maternal protein binding and metabolic activity.
Understanding theophylline pharmacokinetics (PK) in the foetus is essential to prevent in utero toxicity and optimize prophylactic therapies. Previous studies in pregnancy have been obfuscated by maternal dosing and inadequate sampling in the foetus; both render modelling of foetal PK difficult. Six ewes carrying singleton foetuses received theophylline (60 mg) into the foetal jugular vein. Blood samples were drawn from the foetus and ewe over 36 hr. Serum concentrations were measured. Maternal and foetal pharmacokinetic parameters were estimated. Foetal non-compartmental pharmacokinetic parameters were as follows: half-life 7.37 ± 1.22 hr; volume of distribution 44.62 ± 11.45 L; area under the curve 14.82 ± 2.71 hr/(μg/mL); and clearance 4.15 ± 0.70 L/hr. Rapid theophylline distribution across the placenta was observed. Maternal non-compartmental pharmacokinetic parameters were as follows: half-life 6.54 ± 2.44 hr; volume of distribution 32.48 ± 9.99 L; area under the curve 16.28 ± 4.53 hr/(μg/mL); and clearance 3.69 ± 1.47 L/hr. Foetal and ewe serum concentration-time profiles were fit together into a 3-compartment population pharmacokinetic model, and parameters were as follows: central volume 1.38 ± 0.11 L; 2nd peripheral compartment volume 3.11 ± 0.29 L; 3rd peripheral compartment volume 60.14 ± 6.02 L; elimination clearance 9.89 ± 0.90 L/hr; distribution clearance between central and 2nd compartment 30.87 ± 2.31 L/hr; and distribution clearance between 2nd and 3rd compartments 13.89 ± 1.11 L/hr. Cytochrome P4501A expression was robust in maternal liver; negligible activities were observed in placenta, foetal liver and foetal kidney. In vitro protein binding of theophylline was 30% lower in foetal serum compared to maternal serum (29.7 ± 4.4 versus 42.0 ± 3.6%-bound). Free concentrations were lower in the foetus than in the ewe, suggesting active transport across placenta. In summary, foetal clearance of theophylline is attributable to rapid distribution into the maternal circulation across the placenta followed by greater maternal protein binding and metabolic activity.


Related Concept Videos
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:28
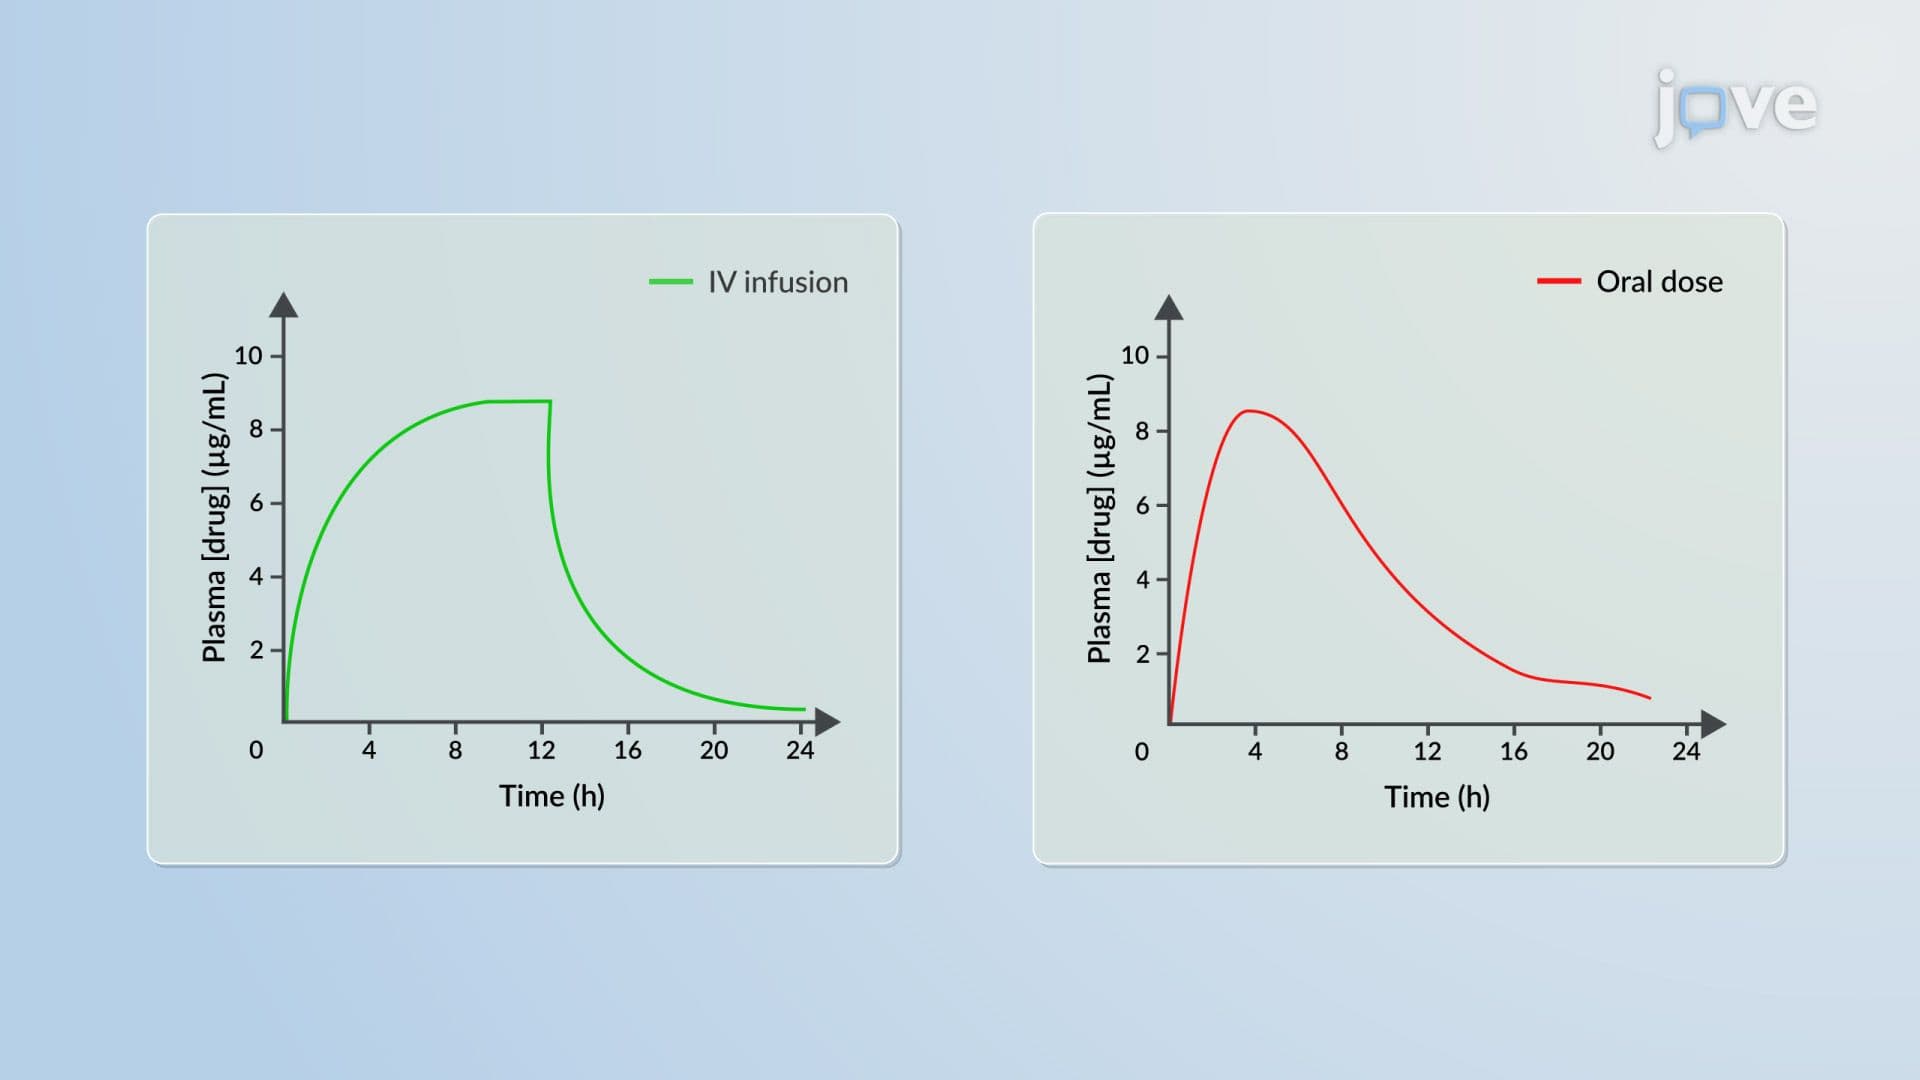
IV Infusion to Oral Dosing: Conversion Methods
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:29
Drug Dosing: Infants and Children