Related Experiment Video
Updated: Apr 16, 2026

Author Spotlight: Advancing Pathogen Detection and Disease Assessment in Real-Time Using M-ROSE
Published on: March 1, 2024
Antibiotic and Diagnostic Discordance Between ED Physicians and Hospitalists for Pediatric Respiratory Illness
Eric R Coon1, Christopher G Maloney2, Mark W Shen3
1Division of Inpatient Medicine, Department of Pediatrics, University of Utah School of Medicine, Primary Children's Hospital, Salt Lake City, Utah; and eric.coon@hsc.utah.edu.

Background And Objective:
Imperfect diagnostic tools make it difficult to know the extent to which a bacterial process is contributing to respiratory illness, complicating the decision to prescribe antibiotics. We sought to quantify diagnostic and antibiotic prescribing disagreements between emergency department (ED) and pediatric hospitalist physicians for children admitted with respiratory illness.
Methods:
Manual chart review was used to identify testing, diagnostic, and antibiotic prescribing decisions for consecutive children admitted for respiratory illness in a winter (starting February 20, 2012) and a summer (starting August 20, 2012) season to a tertiary, freestanding children's hospital. Respiratory illness diagnoses were grouped into 3 categories: bacterial, viral, and asthma.
Results:
A total of 181 children admitted for respiratory illness were studied. Diagnostic discordance was significant for all 3 types of respiratory illness but greatest for bacterial (P<.001). Antibiotic prescribing discordance was significant (P<.001), with pediatric hospitalists changing therapy for 93% of patients prescribed antibiotics in the ED, including stopping antibiotics altogether for 62% of patients.
Conclusions:
Significant diagnostic and antibiotic discordance between ED and pediatric hospitalist physicians exists for children admitted to the hospital for respiratory illness.
Insights
Disagreements in diagnosing bacterial respiratory illness and prescribing antibiotics exist between emergency department and pediatric hospitalist physicians. Pediatric hospitalists frequently altered or stopped antibiotics initiated in the emergency department.
Area of Science:
- Pediatric Medicine
- Infectious Diseases
- Healthcare Quality
Background:
- Accurate diagnosis of bacterial infections in pediatric respiratory illness is challenging due to imperfect diagnostic tools.
- This diagnostic uncertainty complicates decisions regarding antibiotic prescribing in hospitalized children.
- Variations in clinical judgment between emergency department (ED) and pediatric hospitalist physicians can lead to treatment discrepancies.
Purpose of the Study:
- To quantify diagnostic disagreements between ED and pediatric hospitalist physicians for children admitted with respiratory illness.
- To assess antibiotic prescribing discordance between ED and pediatric hospitalist physicians for pediatric respiratory admissions.
Main Methods:
- A manual chart review was conducted for children admitted with respiratory illness during winter and summer seasons.
- Diagnoses were categorized as bacterial, viral, or asthma.
- Testing, diagnostic, and antibiotic prescribing decisions were analyzed.
Main Results:
- Significant diagnostic discordance was observed across all respiratory illness categories, most notably for bacterial infections (P<.001).
- Antibiotic prescribing discordance was also significant (P<.001).
- Pediatric hospitalists modified antibiotic therapy for 93% of patients initially prescribed antibiotics in the ED, discontinuing them in 62%.
Conclusions:
- Substantial diagnostic and antibiotic prescribing discrepancies exist between emergency department and pediatric hospitalist physicians for hospitalized children with respiratory illness.
- These findings highlight a need for improved diagnostic accuracy and standardized treatment protocols to optimize antibiotic use in pediatric respiratory care.


Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
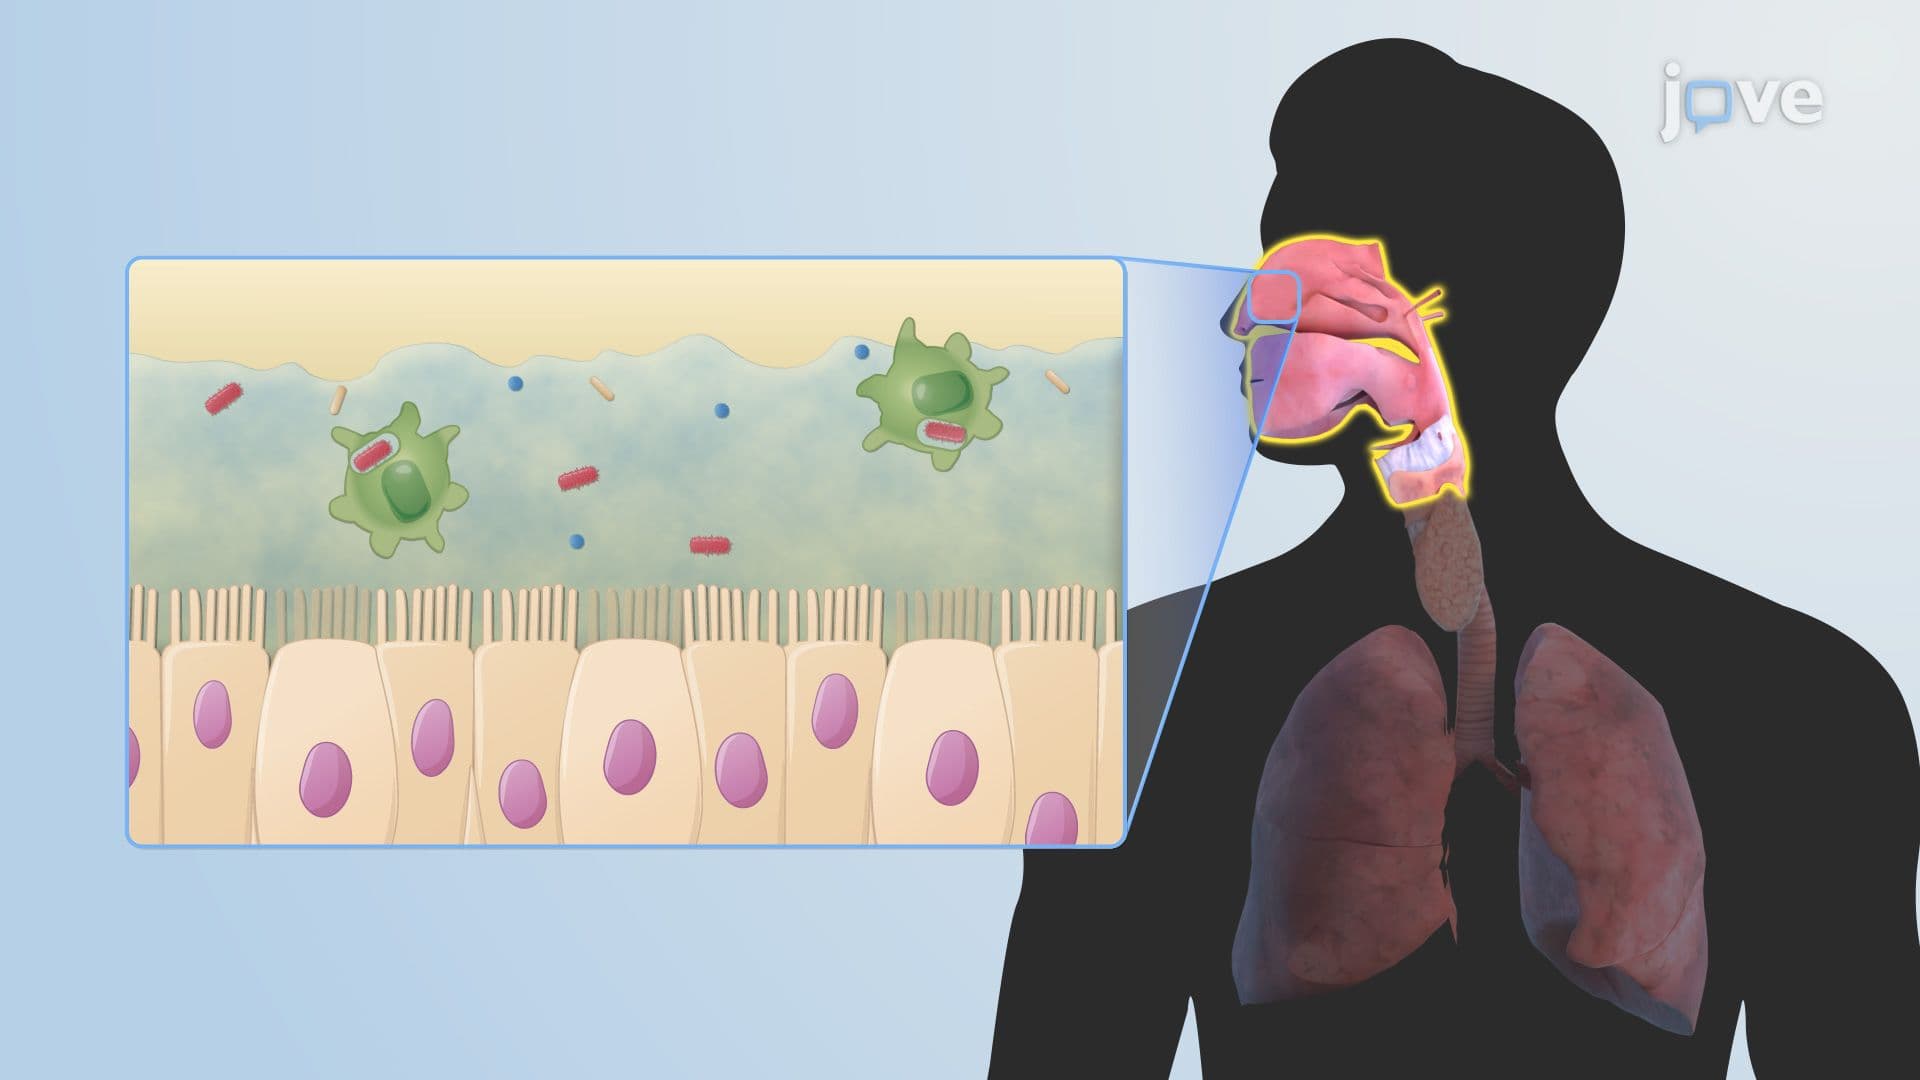 01:29
Microbiota of the Respiratory Tract
 01:14
Atypical Pneumonia
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management