Related Experiment Video
Updated: Apr 16, 2026

Evaluation of Drug Sorption to PVC- and Non-PVC-based Tubes in Administration Sets Using a Pump
Published on: March 11, 2017
Physical compatibility of cisatracurium with selected drugs during simulated Y-site administration
Jaime A Foushee1, Laura M Fox2, Lyndsay R Gormley2
1Jaime A. Foushee, Pharm.D., BCPS, is Assistant Professor of Pharmacy Practice; and Laura M. Fox, Ph.D., is Assistant Dean for Professional and Student Affairs and Professor of Pharmaceutics, School of Pharmacy, Presbyterian College, Clinton, SC. Lyndsay R. Gormley, Pharm.D., is Postgraduate Year 1 Pharmacy Practice Resident, Greenville Health System, Greenville, SC; at the time of writing she was Pharm.D. student, School of Pharmacy, Presbyterian College. Megan S. Lineberger, Pharm.D., is Pharmacist, Rite Aid, Woodruff, SC; at the time of writing she was Pharm.D. student, School of Pharmacy, Presbyterian College. jafoushee@presby.edu.

Purpose:
The physical compatibility of cisatracurium with selected drugs during simulated Y-site administration was studied.
Methods:
Study drugs were selected based on the lack of physical compatibility data with cisatracurium and their use in intensive care units. Test admixtures were prepared by mixing 2.5-mL samples of varying concentrations of calcium gluconate, diltiazem, esomeprazole, regular insulin, nicardipine, pantoprazole, and vasopressin with either 2.5 mL of normal saline 0.9% (control) or 2.5 mL of cisatracurium (experimental) to simulate a 1:1 Y-site ratio. Drug infusions were prepared at the maximum concentrations used clinically. Physical compatibility of the admixtures was determined by visual and turbidimetric assessments performed in triplicate immediately after mixing and at 15, 30, and 60 minutes. Visual incompatibility was defined as a change in color, the formation of haze or precipitate, the presence of particles, or the formation of gas in the experimental groups compared with the controls. Disturbances invisible to the naked eye were determined by assessing changes in turbidity of experimental admixtures compared with the controls.
Results:
None of the admixtures exhibited visual changes when mixed with cisatracurium. Six of the seven admixtures exhibited turbidimetric compatibility with cisatracurium. Pantoprazole admixtures demonstrated a significant difference in turbidimetric assessment between the control and experimental groups when mixed with cisatracurium (p < 0.001).
Conclusion:
Calcium gluconate, diltiazem hydrochloride, esomeprazole, regular insulin, nicardipine hydrochloride, and vasopressin demonstrated physical compatibility with cisatracurium over 60 minutes during simulated Y-site administration. Cisatracurium and pantoprazole should not be coadministered due to a significant difference in turbidity between control and experimental samples.

Related Concept Videos
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:17
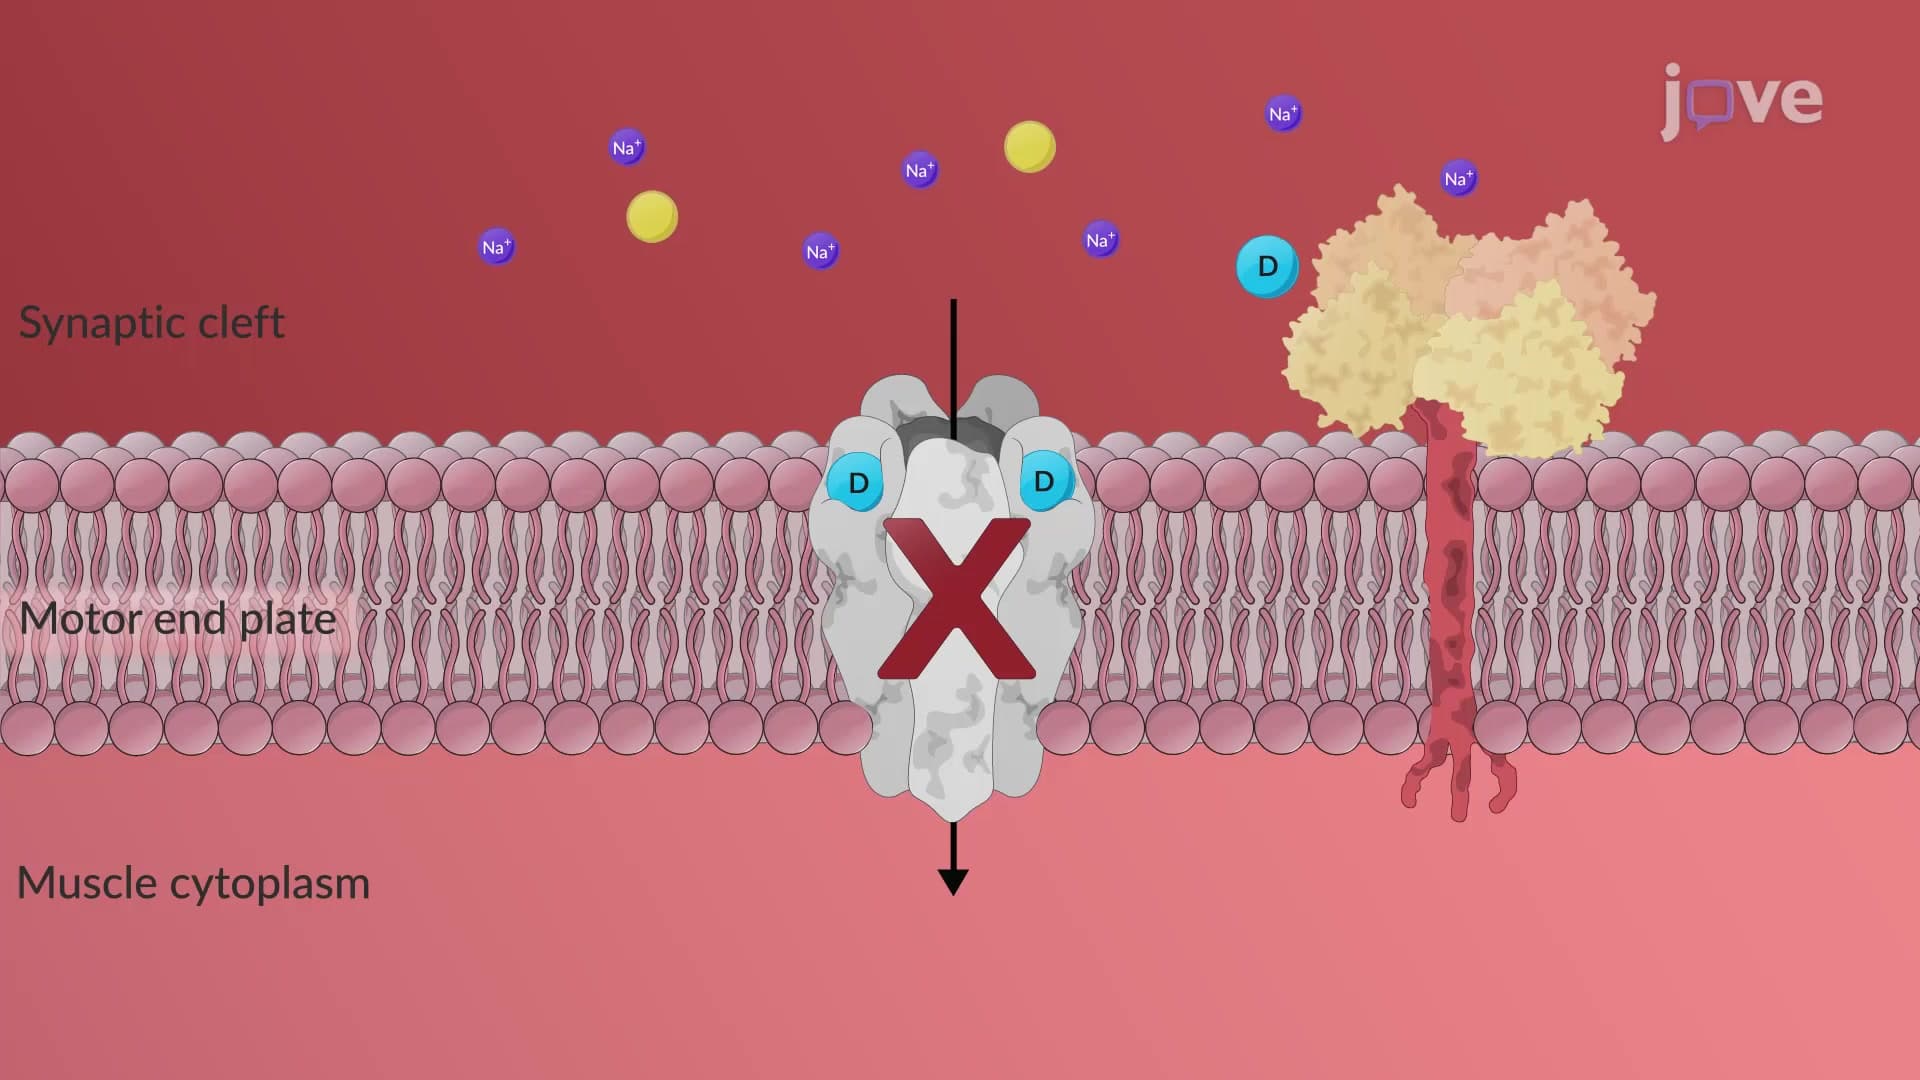
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...