Related Experiment Video
Updated: Apr 16, 2026
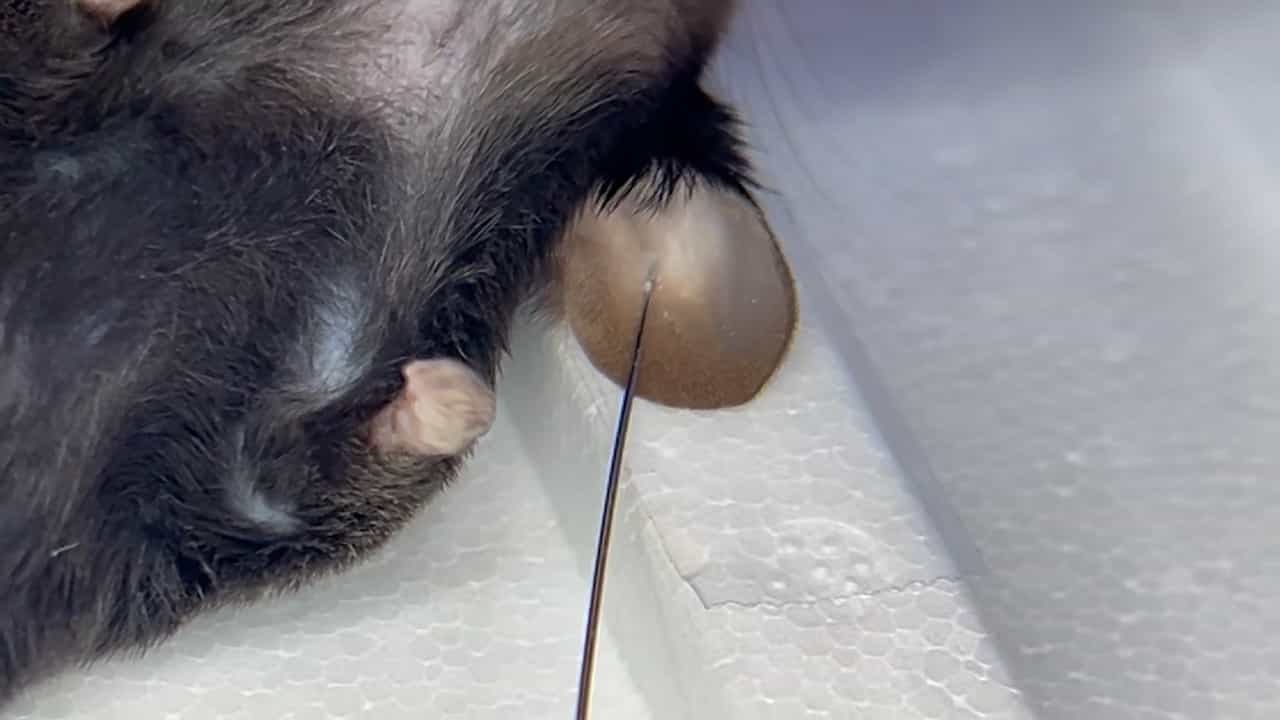

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
Risk factors for recurrence after successful treatment of Mycobacterium avium complex lung disease
Bo Young Lee1, Sunyoung Kim2, YoonKi Hong3
1Division of Pulmonary and Critical Care Medicine, University of Ulsan College of Medicine, Asan Medical Center, Seoul, South Korea.

Abstract:
This study analyzed the recurrence rate and risk factors for recurrence of Mycobacterium avium complex (MAC) lung disease in patients successfully treated for this disease. The medical records of 158 patients successfully treated for MAC lung disease at a tertiary referral center in South Korea between March 2000 and December 2009 were retrospectively analyzed. Recurrence was recorded, and factors associated with recurrence were analyzed. The mean age of the 158 patients was 60.7 ± 11.1 years. The etiologic agent was Mycobacterium avium in 77 patients (48.7%) and Mycobacterium intracellulare in 81 patients (51.3%). Radiographic features included nodular bronchiectatic disease in 95 (60.1%), fibrocavitary disease in 49 (31.0%), and an unclassifiable form in 14 (8.9%) patients. Almost all (98.7%, 156/158) patients had been previously treated with a macrolide-containing regimen, and 68 (43.0%) patients had received treatment with an aminoglycoside. During a median follow-up of 43.8 months after completion of therapy, 50 patients (31.6%) experienced recurrence, at a median of 11.9 months after treatment completion. Multivariate analysis showed that only the nodular bronchiectatic form of the disease (hazard ratio, 2.39; 95% confidence interval, 1.19 to 4.81) was independently associated with an increased risk of recurrence. Recurrence after successful treatment is frequent in patients with MAC lung disease. The recurrence rate was significantly higher in patients with the nodular bronchiectatic form than in those with the fibrocavitary form or an unclassifiable form of the disease.
More Related Videos
 07:21
Processing of Bronchoalveolar Lavage Fluid and Matched Blood for Alveolar Macrophage and CD4+ T-cell Immunophenotyping and HIV Reservoir Assessment
Published on: June 23, 2019
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...