Related Experiment Video
Updated: Apr 16, 2026


Establishment of the Dual Humanized TK-NOG Mouse Model for HIV-associated Liver Pathogenesis
Published on: September 11, 2019
Structural Bone Deficits in HIV/HCV-Coinfected, HCV-Monoinfected, and HIV-Monoinfected Women
Vincent Lo Re1, Kenneth Lynn2, Emily R Stumm2
1Division of Infectious Diseases Division of Center for AIDS Research Division of Center for Clinical Epidemiology and Biostatistics, Department of Biostatistics and Epidemiology.

Insights
Human immunodeficiency virus (HIV) and hepatitis C virus (HCV) coinfection in women is linked to lower bone mineral density (BMD) and thinner bone cortices, indicating increased fracture risk. This study characterized the structural bone changes in these women.
Area of Science:
- Bone biology and skeletal health
- Infectious diseases and immunology
- Radiology and imaging
Background:
- Coinfection with HIV and HCV is associated with reduced bone mineral density (BMD) and higher fracture rates in women.
- The specific structural changes contributing to skeletal fragility in coinfected women remain unclear.
Purpose of the Study:
- To characterize the structural underpinnings of skeletal fragility in women coinfected with HIV and HCV.
- To evaluate tibial bone parameters using peripheral quantitative computed tomography (pQCT) in relation to HIV/HCV status.
Main Methods:
- A cross-sectional study involving 50 HIV/HCV-coinfected, 51 HCV-monoinfected, and 50 HIV-monoinfected women.
- Tibial volumetric BMD and cortical dimensions were assessed using pQCT.
- Race-specific z-scores for age were calculated against a reference group of 263 women without HIV or liver disease.
Main Results:
- HIV/HCV-coinfected women exhibited significantly lower mean z-scores for trabecular volumetric BMD, cortical volumetric BMD, cortical area, and cortical thickness compared to reference participants.
- Reduced cortical dimensions were attributed to increased endosteal circumference with stable periosteal circumference.
- Trabecular volumetric BMD was lower in coinfected women compared to those with mono-infections. Advanced liver fibrosis (stage 3-4) in HCV-infected women correlated with lower BMD and cortical thickness.
Conclusions:
- HIV/HCV coinfection in women is associated with decreased tibial trabecular volumetric BMD and diminished cortical dimensions.
- Significant endocortical bone loss contributes to skeletal fragility in coinfected women.
- These structural bone changes provide a basis for the observed increased fracture risk.
Background:
Coinfection with human immunodeficiency virus (HIV) and hepatitis C virus (HCV) is associated with reduced bone mineral density (BMD) and increased fracture rates, particularly in women. The structural underpinnings for skeletal fragility in coinfected women have not been characterized. We used tibial peripheral quantitative computed tomography to evaluate skeletal parameters in women, by HIV/HCV status.
Methods:
We conducted a cross-sectional study among 50 HIV/HCV-coinfected, 51 HCV-monoinfected, and 50 HIV-monoinfected women. Tibial volumetric BMD and cortical dimensions were determined with peripheral quantitative computed tomography. Race-specific z scores for age were generated using 263 female reference participants without HIV infection or liver disease.
Results:
Coinfected participants had lower mean z scores for trabecular volumetric BMD (-0.85), cortical volumetric BMD (-0.67), cortical area (-0.61), and cortical thickness (-0.77) than reference participants (all P < .001). The smaller cortical dimensions were due to greater mean z scores for endosteal circumference (+0.67; P < .001) and comparable z scores for periosteal circumference (+0.04; P = .87). Trabecular volumetric BMD was lower in coinfected than in HCV- or HIV-monoinfected participants. HCV-infected women with stage 3-4 liver fibrosis had lower mean z scores for trabecular volumetric BMD, cortical thickness, and total hip BMD those with stage 0-2 fibrosis.
Conclusions:
Compared with healthy reference patients, HIV/HCV-coinfected women had decreased tibial trabecular volumetric BMD, diminished cortical dimensions, and significant endocortical bone loss.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:27
Cytomegalovirus Disease
 01:26
Sexually Transmitted Infections
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:27
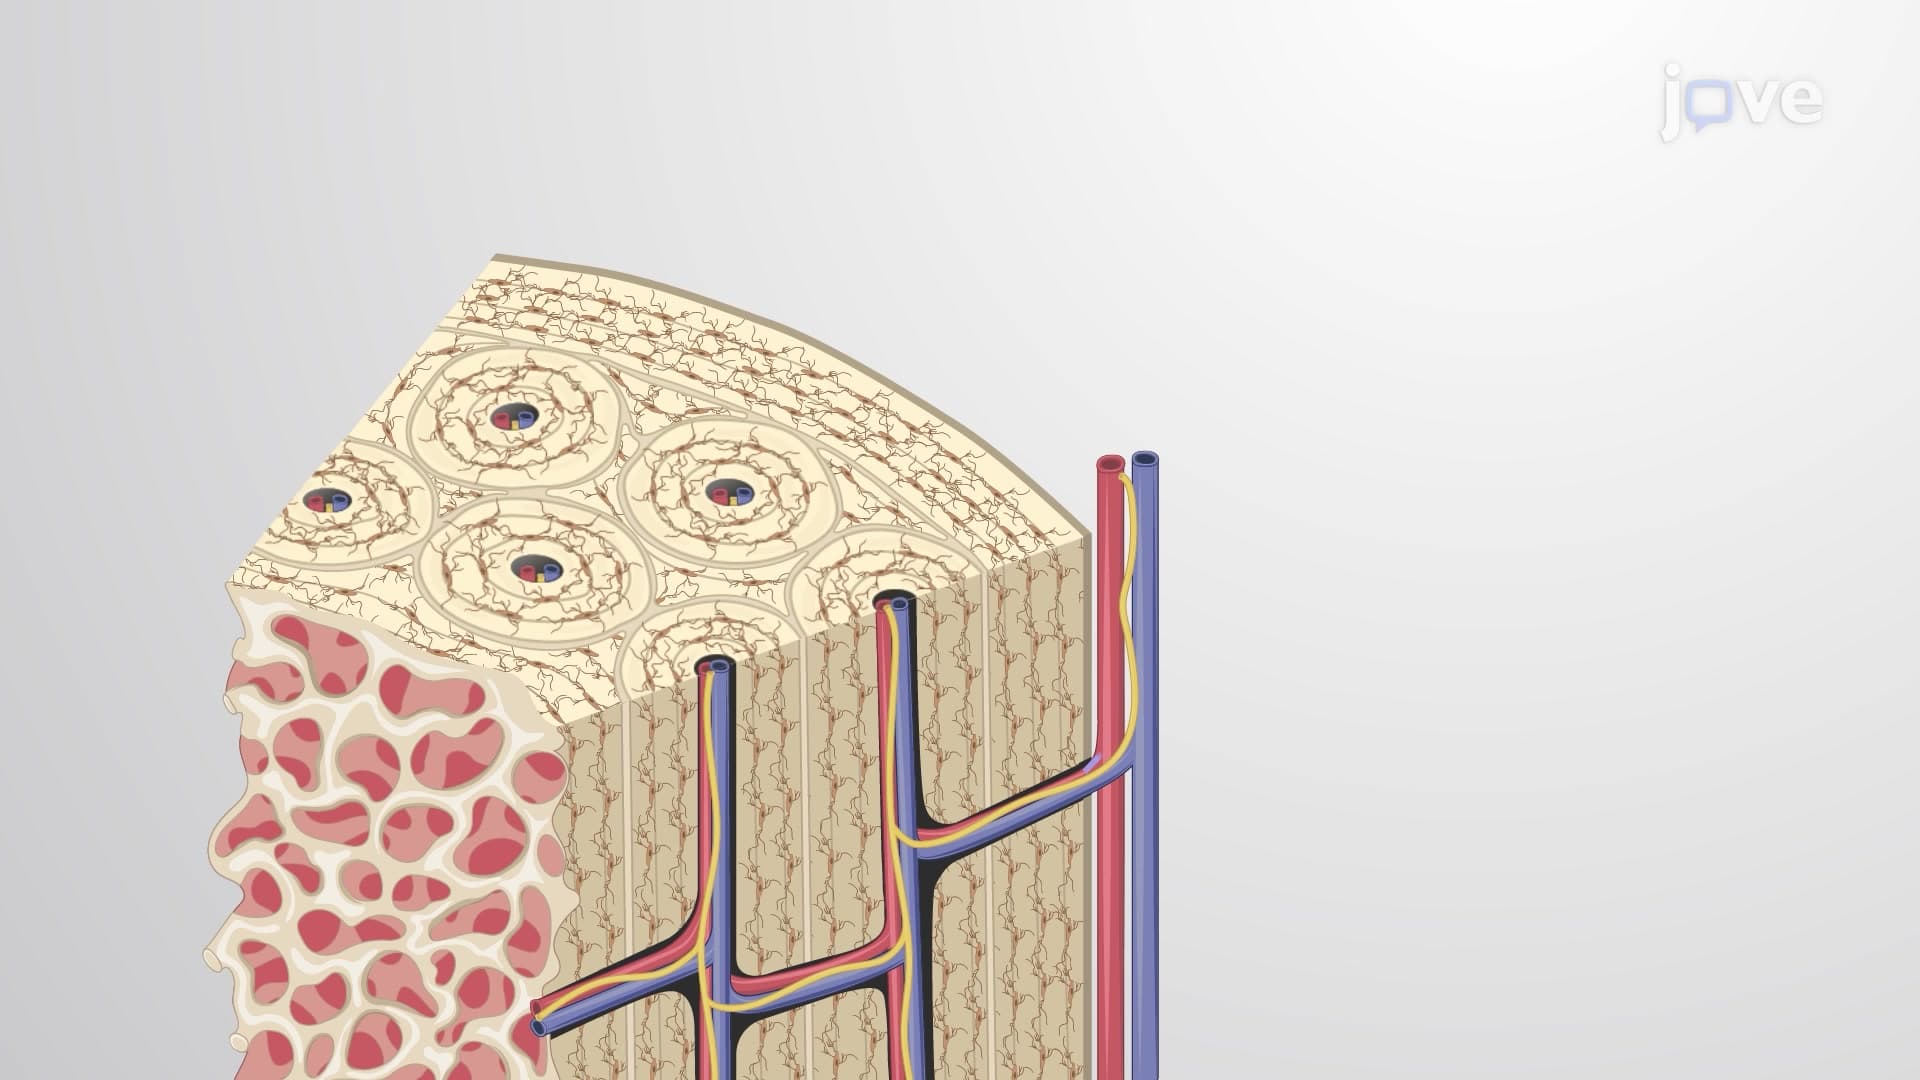
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...