Related Experiment Video
Updated: Apr 16, 2026

Use of a Hanging-weight System for Isolated Renal Artery Occlusion
Published on: July 19, 2011
Iohexol transmembrane clearance during modeled continuous renal replacement therapy

Background/Aims:
Urea clearance during continuous renal replacement therapy (CRRT) is not representative of middle molecular weight solute clearances. We aimed to characterize iohexol, molecular weight 821 Da, clearance during continuous hemofiltration (CH) and continuous hemodialysis (CHD).
Methods:
Using an in vitro model, iohexol sieving coefficients (SC) and saturation coefficients (SA) were determined with the M100 membrane at ultrafiltration/dialysate rates of 1, 2, 3, 4, and 6 l/h. Iohexol transmembrane clearance was calculated using the measured SC and SA.
Results:
During CH, the value of iohexol SC remained approximately 1 at all ultrafiltration rates studied. In contrast, during CHD iohexol the mean SA was 1.02 ± 0.05 at a dialysate rate 1 l/h and decreased significantly with higher dialysate rates to a mean SA of 0.57 ± 0.12 at a dialysate rate of 6 l/h.
Conclusions:
At higher effluent flow rates, CH was more effective in removing iohexol than CHD. CH transmembrane clearance of iohexol appears to approximate the ultrafiltration rate.

Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:08
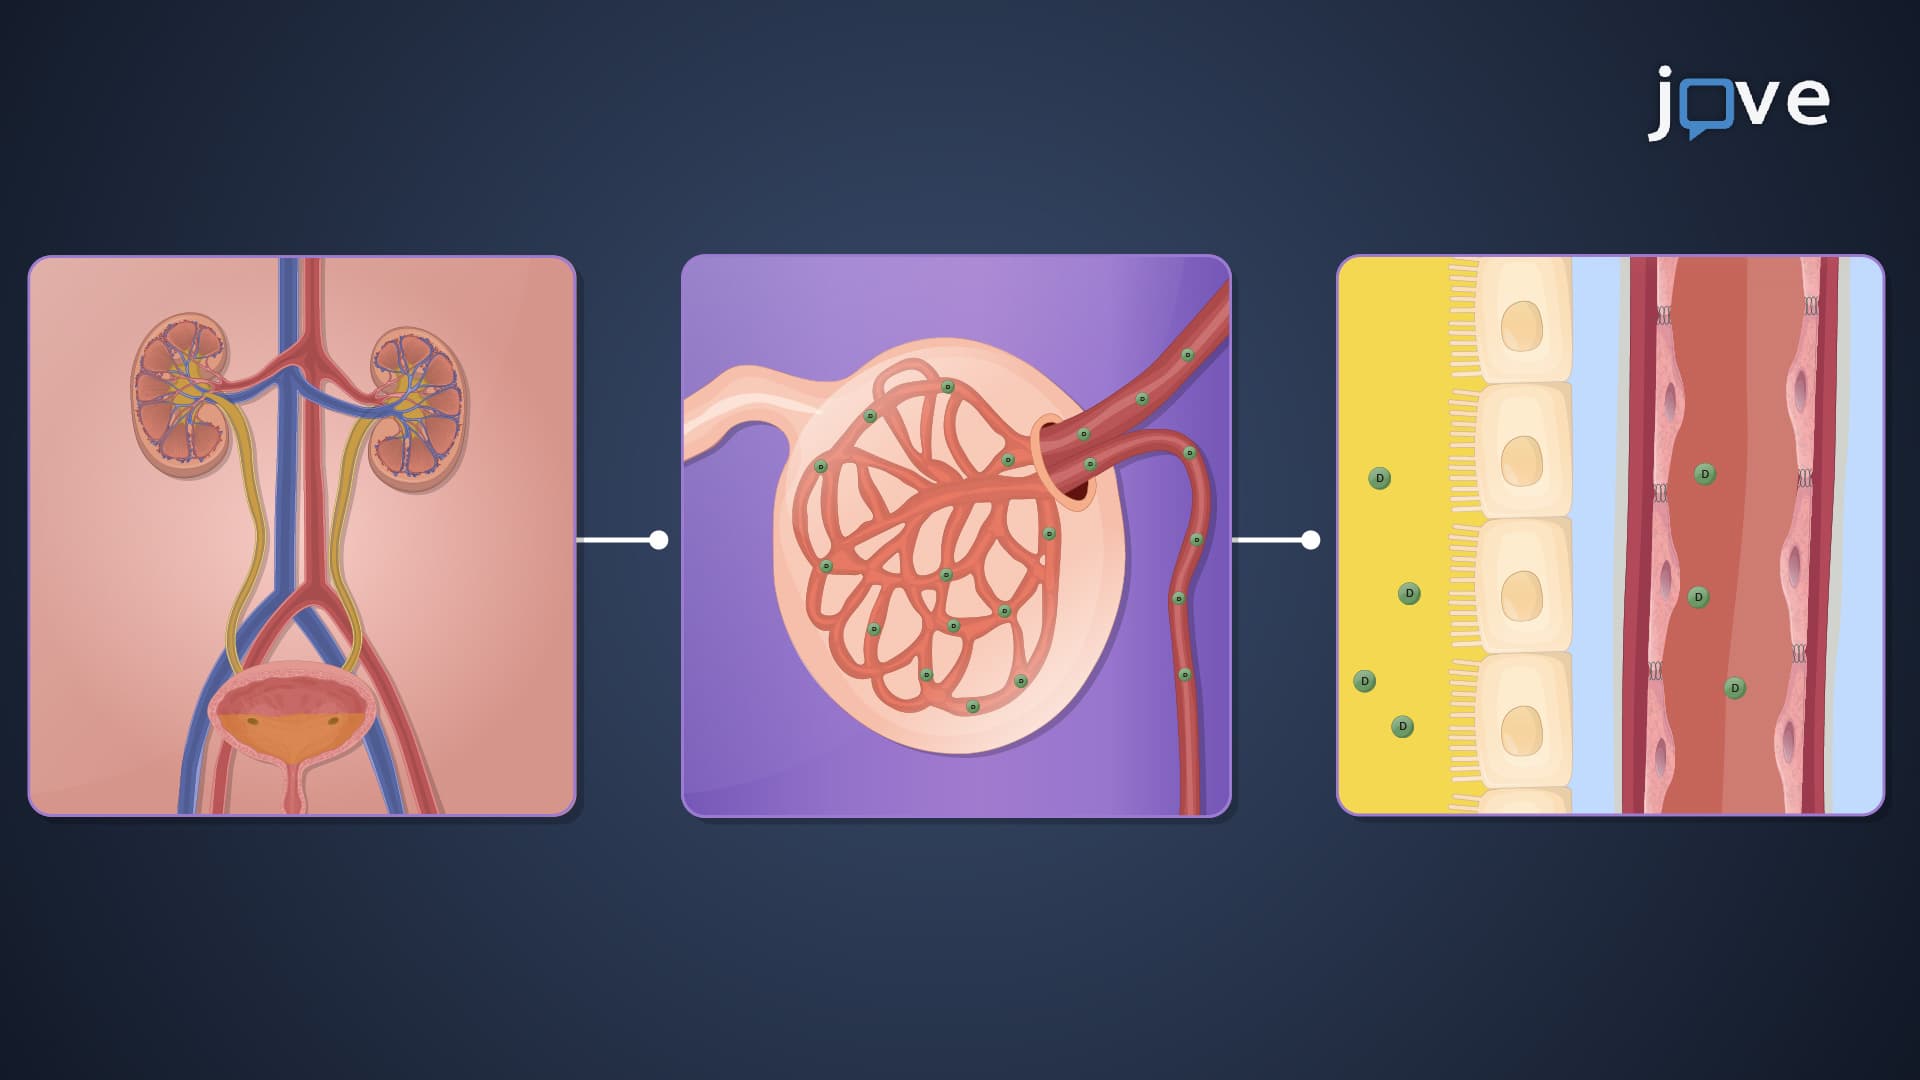
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:06
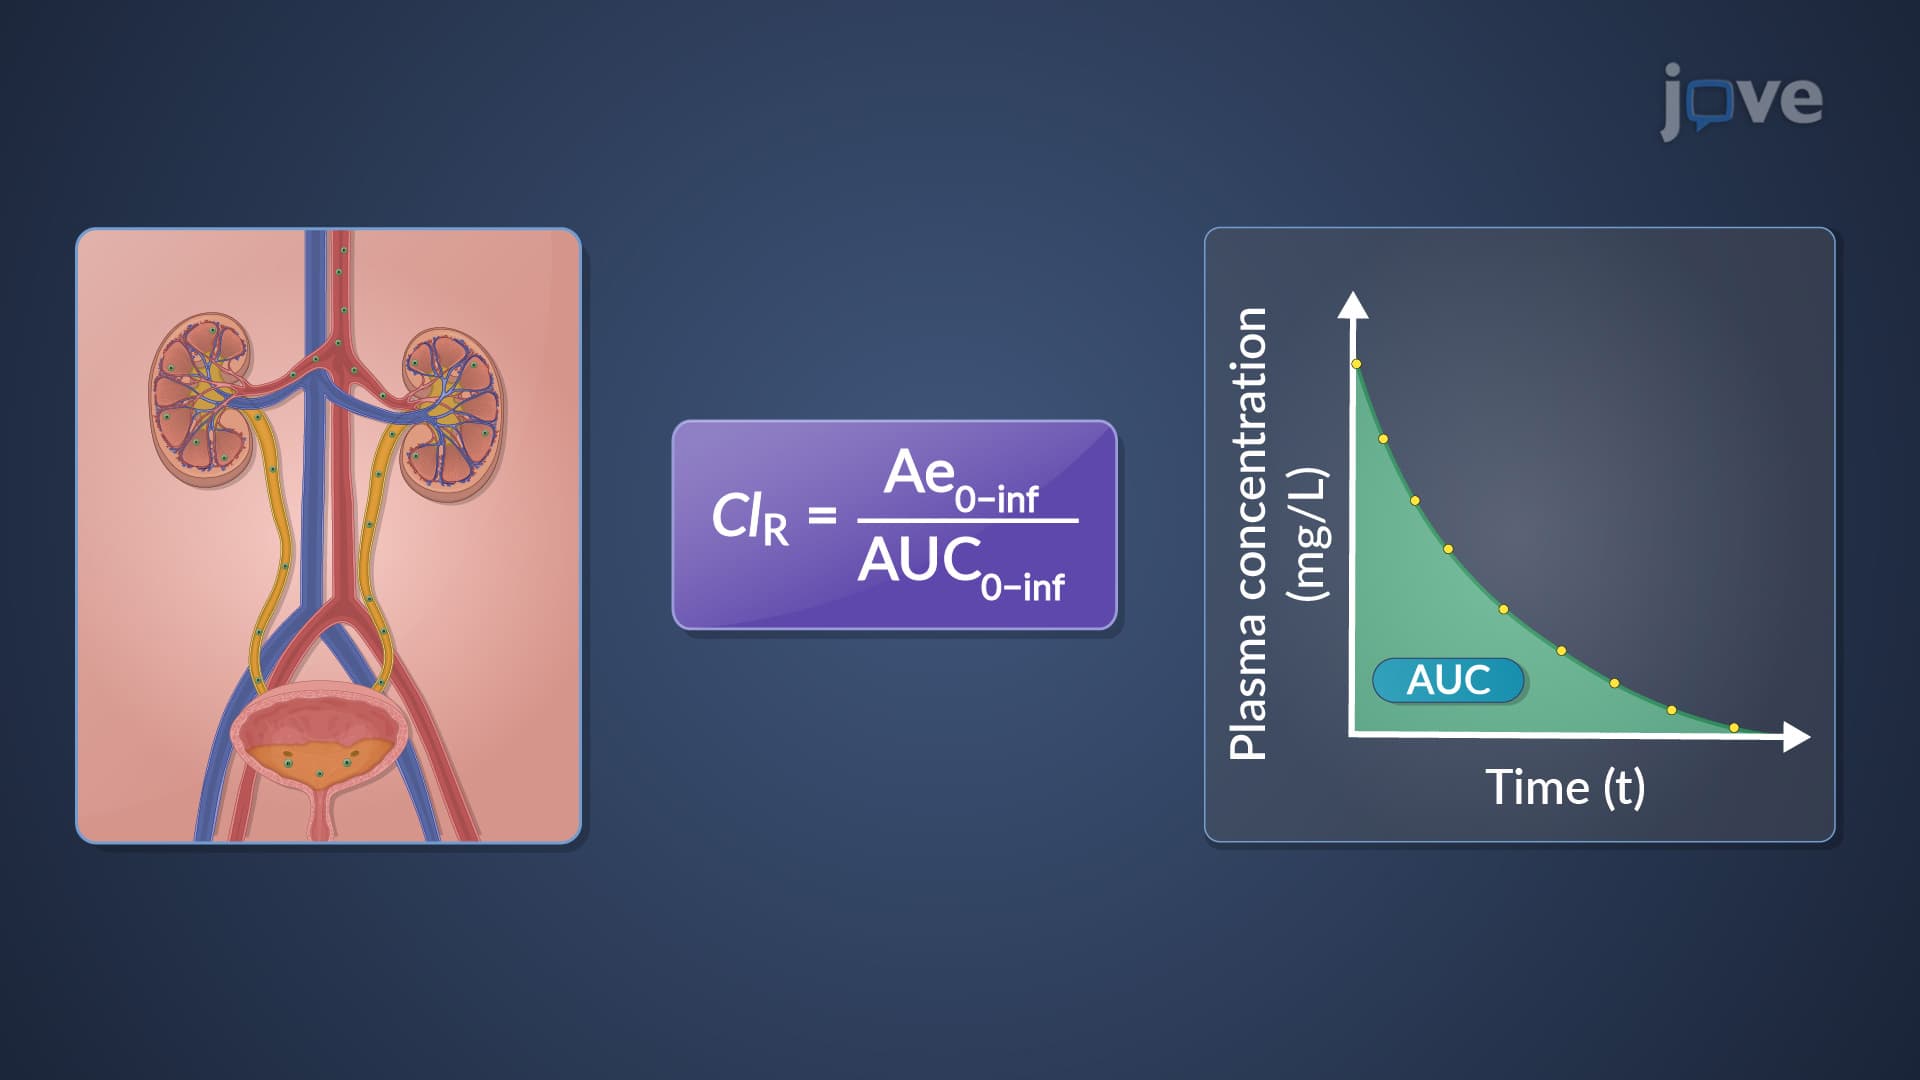
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions