Related Experiment Video
Updated: Apr 16, 2026


Induction of Nephrotic Syndrome in Mice by Retrobulbar Injection of Doxorubicin and Prevention of Volume Retention by Sustained Release Aprotinin
Published on: May 6, 2018
Nonalbumin proteinuria predominates in biopsy-proven tenofovir nephrotoxicity
Meghan E Sise1, Jamie S Hirsch, Pietro A Canetta
1aDivision of Nephrology, Department of Medicine, Massachusetts General Hospital, Boston, Massachusetts bDivision of Nephrology, Department of Medicine cDepartment of Biomedical Informatics, Columbia University Medical Center, New York, New York dDepartment of Anatomic Pathology, Cleveland Clinic, Cleveland, Ohio, USA.

Objective:
Tenofovir disoproxil fumarate (TDF) nephrotoxicity is characterized by proximal renal tubular injury and dysmorphic mitochondria resulting in proteinuria, orthoglycemic glycosuria, and other markers of proximal tubular dysfunction. The objective of this study was to determine the pattern of proteinuria in patients with biopsy-proven TDF nephrotoxicity.
Design:
Retrospective chart review.
Methods:
Patients with biopsy-proven TDF nephrotoxicity were identified and their medical charts and biopsy reports were reviewed. Comparison was made with HIV-infected patients not on TDF who underwent kidney biopsy.
Results:
We identified 43 biopsy-proven cases of TDF nephrotoxicity; mean age 54.7 ± 0.4 years, 53% men, 42% whites. Thirty-seven cases reported proteinuria by dipstick of which only 60% had at least 2+ proteinuria. Twenty-seven patients had urine protein quantified by either 24-h collection or spot urine protein-to-creatinine ratio; median proteinuria was 1742 mg/day [interquartile range (IQR) 1200-2000 mg] and 1667 mg/g creatinine (IQR 851-1967 mg/g), respectively. Ten patients had concurrent urinary albumin measured, with a median 236 mg/g creatinine (IQR 137-343 mg/g). The mean urine albumin-to-urine protein ratio (uAPR) was 0.17 (IQR 0.14-0.19), confirming that TDF nephrotoxicity is primarily associated with nonalbumin proteinuria. Control cases had a uAPR of 0.65 (IQR 0.55-0.79) P < 0.001. Histopathology showed the predominance of proximal tubular injury with characteristic mitochondrial abnormalities.
Conclusion:
In the largest published cohort of patients with biopsy-proven TDF nephrotoxicity, we show that low uAPR is a reliable feature of this disease. Because of the predominance of nonalbumin proteinuria, dipstick urinalysis may be unreliable in TDF nephrotoxicity.

Related Concept Videos
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:28
Renal Drug Excretion: Tubular Secretion
 01:02
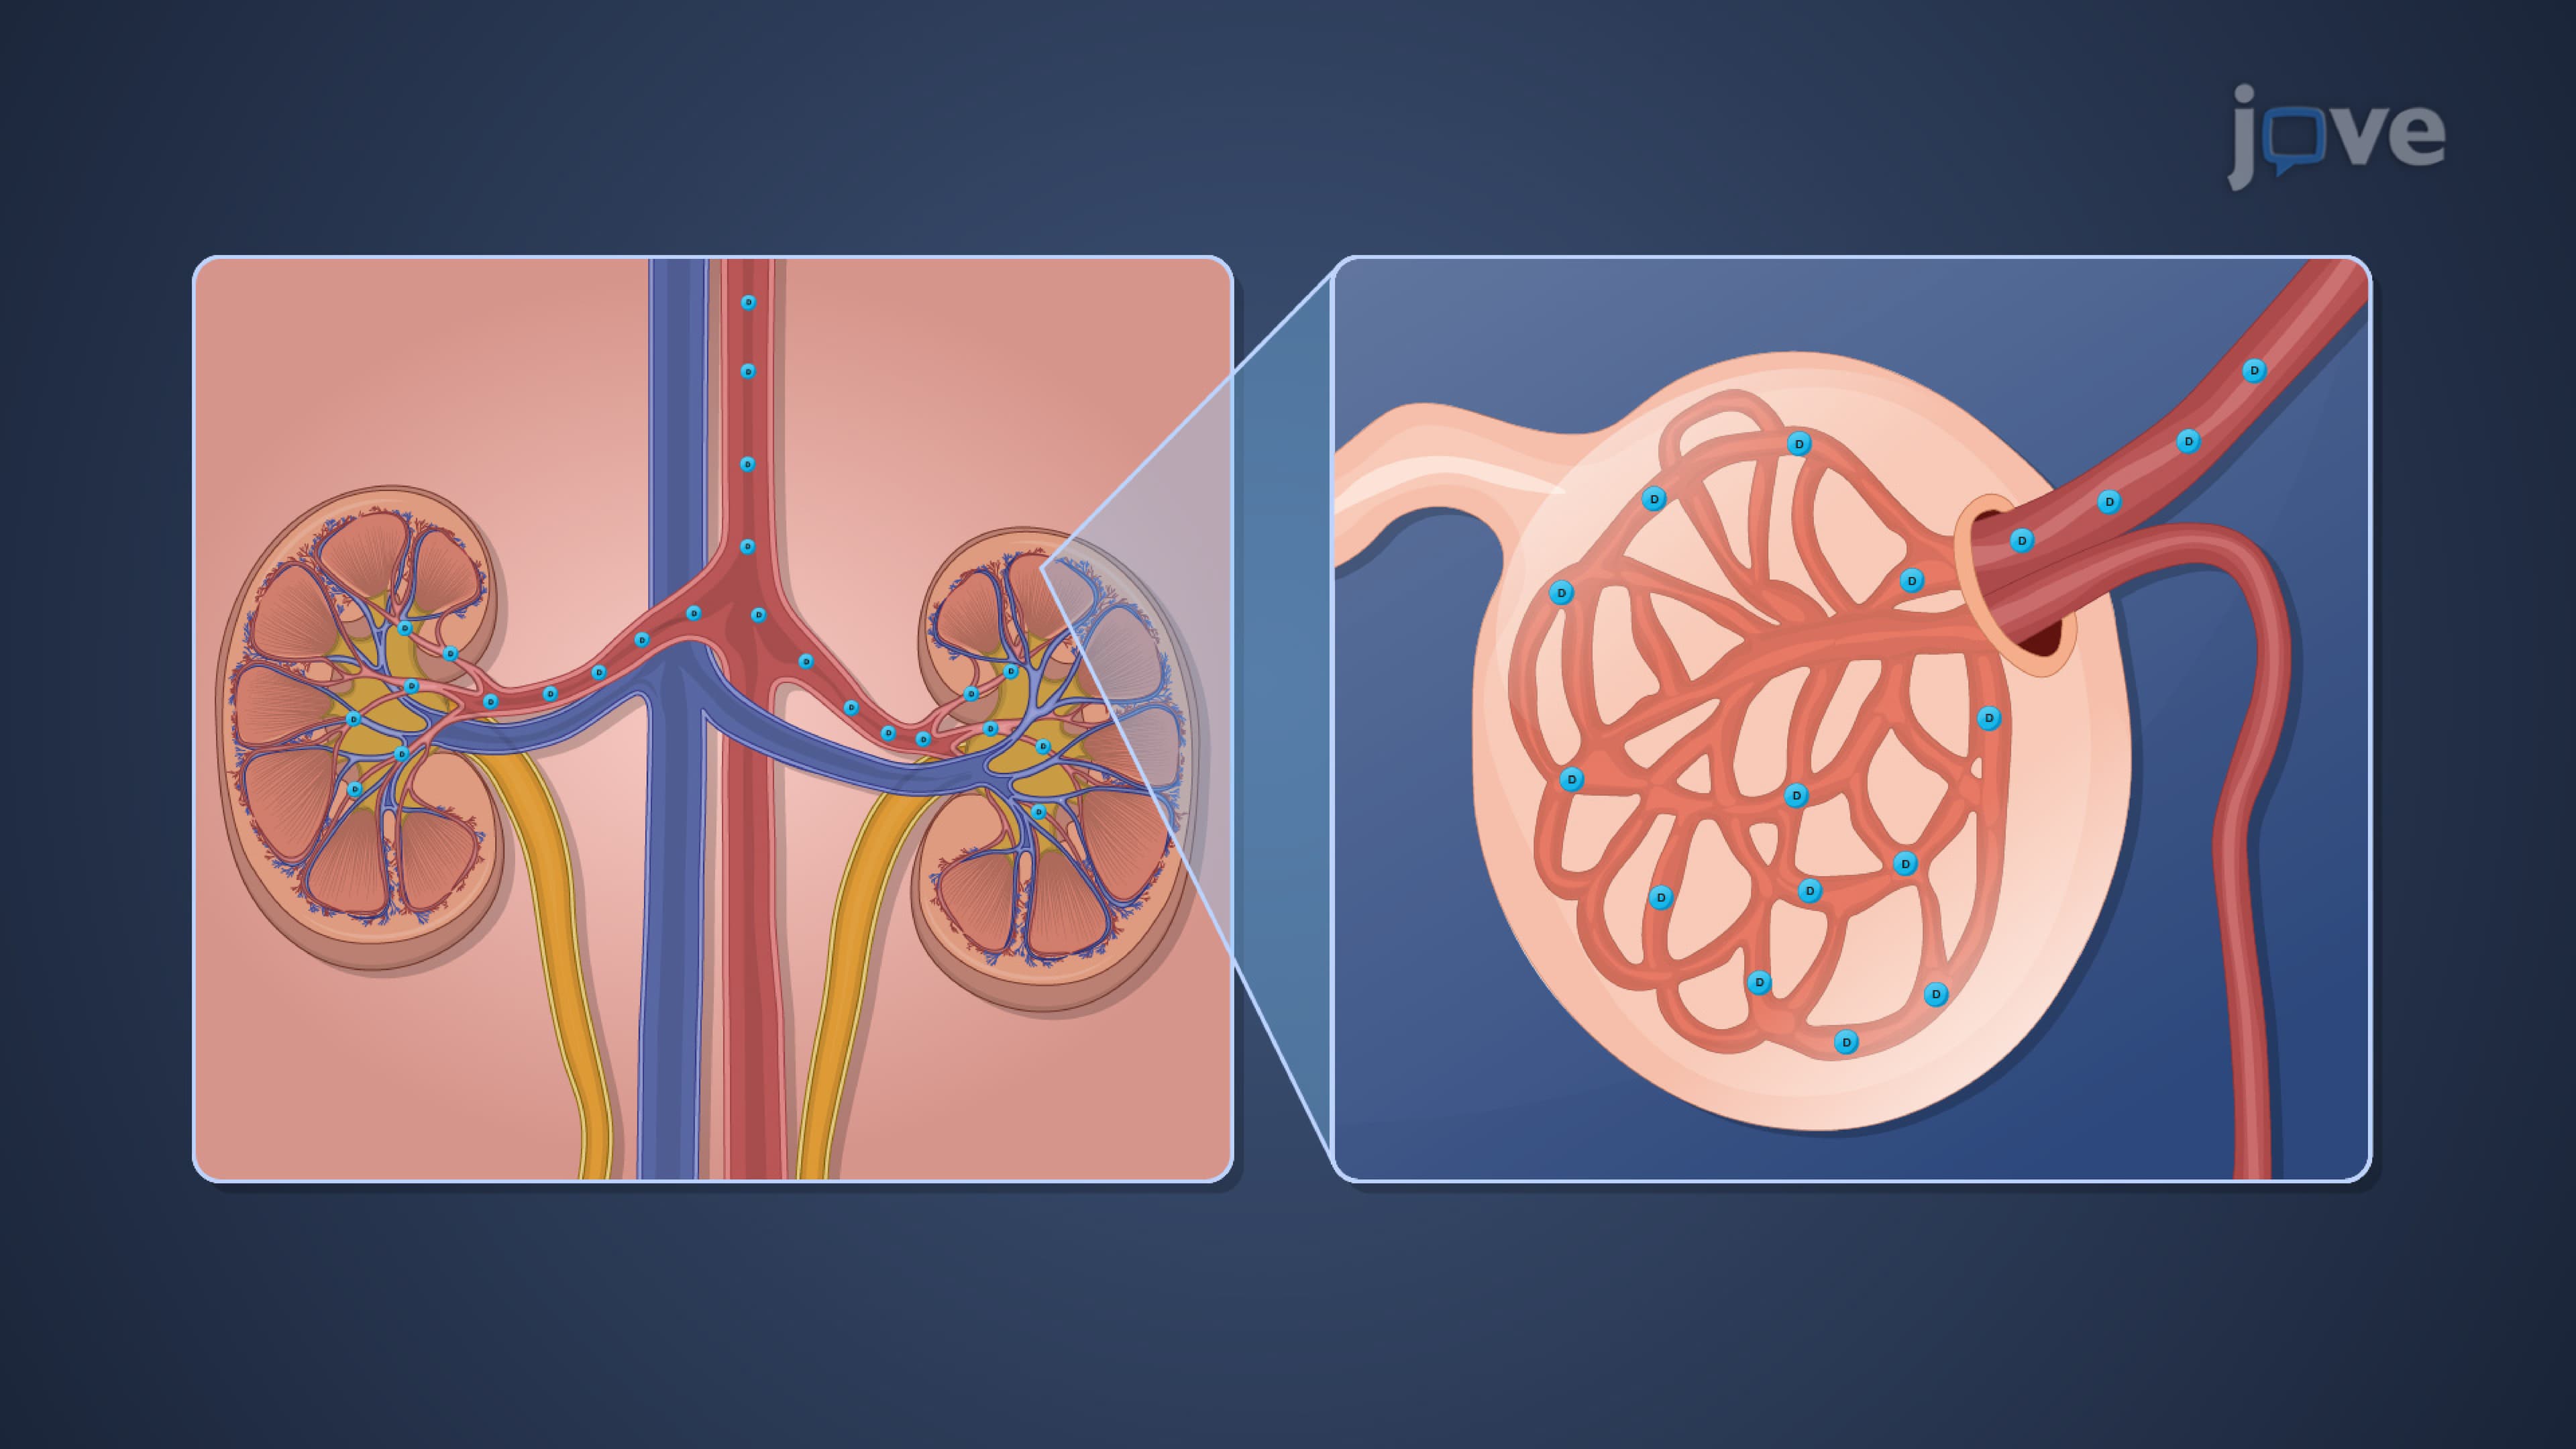
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:24
Nephrotic Syndrome I : Introduction
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...