Related Experiment Video
Updated: Apr 16, 2026

A Protocol for Analyzing Hepatitis C Virus Replication
Published on: June 26, 2014
Current status and emerging challenges in the treatment of hepatitis C virus genotypes 4 to 6
Vasilios Papastergiou1, Stylianos Karatapanis1
1Vasilios Papastergiou, Stylianos Karatapanis, Department of Internal Medicine, General Hospital of Rhodes, 85100 Rhodes, Greece.

Insights
Hepatitis C virus (HCV) genotypes 4, 5, and 6 are prevalent in Africa, the Middle East, and Asia. Current treatments show variable response rates, with newer direct-acting antivirals (DAAs) offering future promise.
Area of Science:
- Hepatology
- Virology
- Infectious Diseases
Background:
- Hepatitis C virus (HCV) genotypes 4, 5, and 6 are geographically concentrated in Africa, the Middle East, and Asia.
- These genotypes have been less extensively studied compared to others, particularly regarding epidemiology and disease progression.
- Limited data exists on optimal therapeutic strategies for these specific HCV genotypes.
Purpose of the Study:
- To review the current understanding of Hepatitis C virus (HCV) genotypes 4, 5, and 6.
- To evaluate the efficacy of existing and emerging treatments for these genotypes.
- To highlight the challenges and future directions in managing HCV 4-6 infections, especially in resource-limited settings.
Main Methods:
- Literature review of epidemiological data, natural history, and therapeutic outcomes for HCV genotypes 4, 5, and 6.
- Analysis of response rates for peginterferon/ribavirin combination therapy.
- Assessment of recent recommendations for direct-acting antiviral (DAA) regimens.
Main Results:
- Peginterferon/ribavirin treatment shows variable response rates: 40%-69% for HCV 4, 55%-60% for HCV 5, and 60%-90% for HCV 6.
- Response-guided therapy is recommended for HCV 4 and preliminarily for HCV 6, but not yet for HCV 5.
- Pan-genotypic DAAs (simeprevir, sofosbuvir, daclatasvir) are now recommended in triple regimens with peginterferon/ribavirin for HCV 4-6.
Conclusions:
- Direct-acting antiviral (DAA)-based interferon-free therapies are expected to significantly improve HCV treatment outcomes.
- Continued efforts to optimize peginterferon/ribavirin treatment are crucial due to the accessibility and cost of DAAs in resource-limited regions where HCV 4-6 are prevalent.
- Further research is needed to support individualized therapy for HCV 5 and to ensure equitable access to advanced treatments globally.
Abstract:
Hepatitis C virus (HCV) genotypes 4, 5 and 6 are mainly present in Africa, the Middle East and Asia and they have been less extensively studied with respect to epidemiology, natural disease history and therapeutic endpoints. Response rates to a 48-wk combined peginterferon/ribavirin treatment range to 40%-69% for HCV 4, 55%-60% for HCV 5 and 60%-90% for HCV 6. Response-guided schedules are recommended to optimize the outcomes of peginterferon/ribavirin treatment in HCV 4 and, in form of preliminary data, for HCV 6, but no data are yet available to support such an individualization of therapy for HCV 5. Recently, the direct-acting antivirals (DAAs) with pan-genotypic activities simeprevir, sofosbuvir and daclatasvir have been recommended in triple regimens with peginterferon/ribavirin for the treatment of HCV genotypes 4 to 6 infections. In the future, DAA-based interferon-free therapies are awaited to drastically improve treatment outcomes in HCV. However, efforts to improve treatment outcomes with peginterferon/ribavirin should continue, as the HCV 4-6 infected population is mainly based in resource-limited settings with restricted access to the costly DAAs.
More Related Videos


Related Concept Videos
 01:25
Hepatitis
 01:30
Inhibitors of Viral Protein Synthesis
 01:10
Retrovirus Life Cycles
 01:29
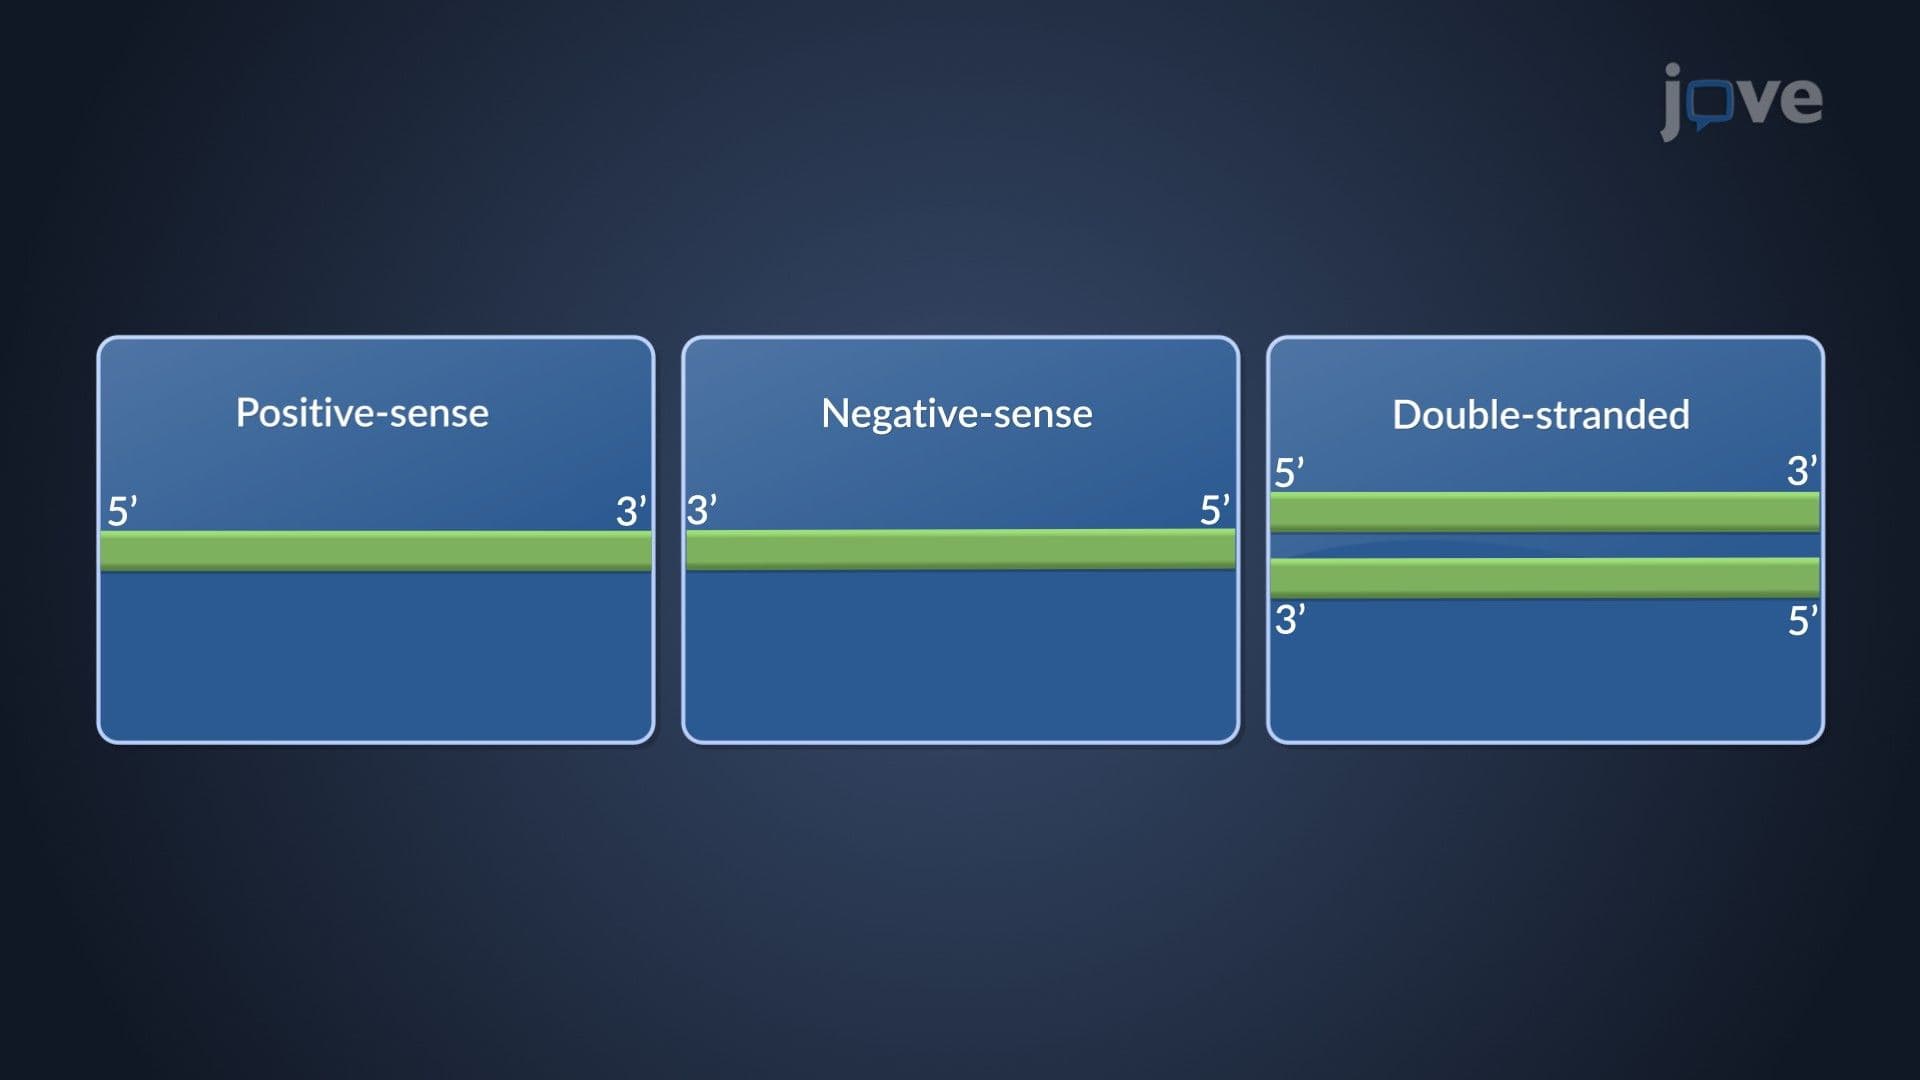
Viruses with RNA Genomes
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase