Related Experiment Video
Updated: Apr 16, 2026
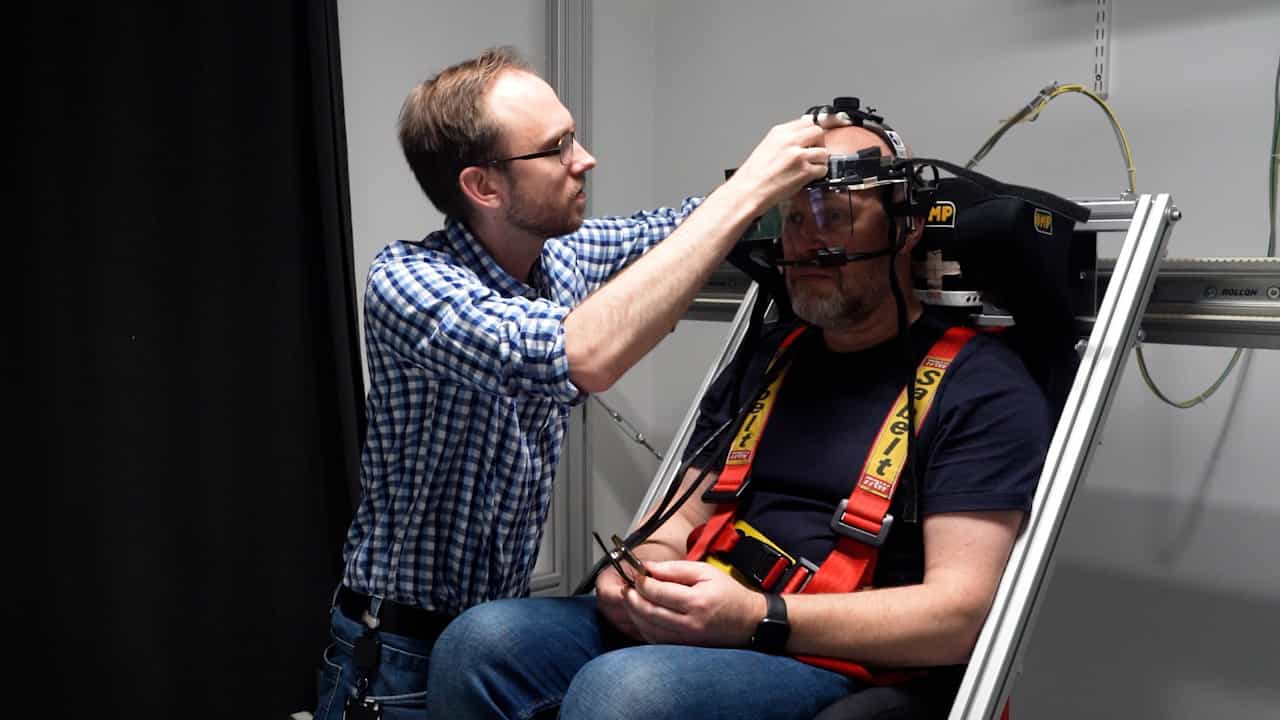

Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Clinical and electrographic findings in epileptic vertigo and dizziness: a systematic review
Alexander A Tarnutzer1, Seung-Han Lee2, Karen A Robinson2
1From the Department of Neurology (A.A.T.), University Hospital Zurich and the University of Zurich, Switzerland; the Department of Neurology (S.-H.L.), Chonnam National University Medical School, Gwangju, South Korea; the Departments of Medicine (K.A.R.), Neurology (D.E.N.-T.), and Otolaryngology Head & Neck Surgery (D.E.N.-T.), The Johns Hopkins University School of Medicine; and the Department of Neurology (P.W.K.), Johns Hopkins Bayview Medical Center, Baltimore, MD. alexander.tarnutzer@access.uzh.ch.

Objective:
Seizures can cause vestibular symptoms, even without obvious epileptic features. We sought to characterize epileptic vertigo or dizziness (EVD) to improve differentiation from nonepileptic causes, particularly when vestibular symptoms are the sole manifestation.
Methods:
We conducted a systematic review with electronic (Medline) and manual search for English-language studies (1955-2014). Two independent reviewers selected studies. Study/patient characteristics were abstracted. We defined 3 study population types: (1) seizures, some experiencing vertigo/dizziness (disease cohort); (2) vertigo/dizziness, some due to seizures (symptom cohort); (3) vertigo/dizziness due to seizures in all patients (EVD-only cohort).
Results:
We identified 84 studies describing 11,354 patients (disease cohort = 8,129; symptom cohort = 2,965; EVD-only cohort = 260). Among 1,055 EVD patients in whom a distinction could be made, non-isolated EVD was present in 8.5%, isolated EVD in 0.8%. Thorough diagnostic workups (ictal EEG, vestibular testing, and brain MRI to exclude other causes) were rare (<0.1%). Ictal EEG was reported in 487 (4.3%), formal neuro-otologic assessment in 1,107 (9.7%). Localized EEG abnormalities (n = 350) were most frequently temporal (79.8%) and uncommonly parietal (11.8%). Duration of episodic vestibular symptoms varied, but was very brief (<30 seconds) in 69.6% of isolated EVD and 6.9% of non-isolated EVD.
Conclusions:
Non-isolated EVD is much more prevalent than isolated EVD, which appears to be rare. Diagnostic evaluations for EVD are often incomplete. EVD is primarily associated with temporal lobe seizures; whether this reflects greater epidemiologic prevalence of temporal lobe seizures or a tighter association with dizziness/vertigo presentations than with other brain regions remains unknown. Consistent with clinical wisdom, isolated EVD spells often last just seconds, although many patients experience longer spells.
More Related Videos
 10:27
In Vivo Morphometric Analysis of Human Cranial Nerves Using Magnetic Resonance Imaging in Menière's Disease Ears and Normal Hearing Ears
Published on: February 21, 2018
 06:30
Assessment of Static Graviceptive Perception in the Roll-Plane using the Subjective Visual Vertical Paradigm
Published on: April 28, 2020