Related Experiment Video
Updated: Apr 15, 2026


MRI Mapping of Cerebrovascular Reactivity via Gas Inhalation Challenges
Published on: December 17, 2014
Cerebral hemodynamics at altitude: effects of hyperventilation and acclimatization on cerebral blood flow and
Matthew R Sanborn1, Mark E Edsell2, Meeri N Kim3
1UCL Centre for Altitude, Space and Extreme Environment Medicine, Portex Unit, Institute of Child Health (Drs Sanborn, Edsell, Imray, Yow, Wilson, Grocott, and Martin), and; Maine Medical Center, Portland, ME (Dr Sanborn).

Objective:
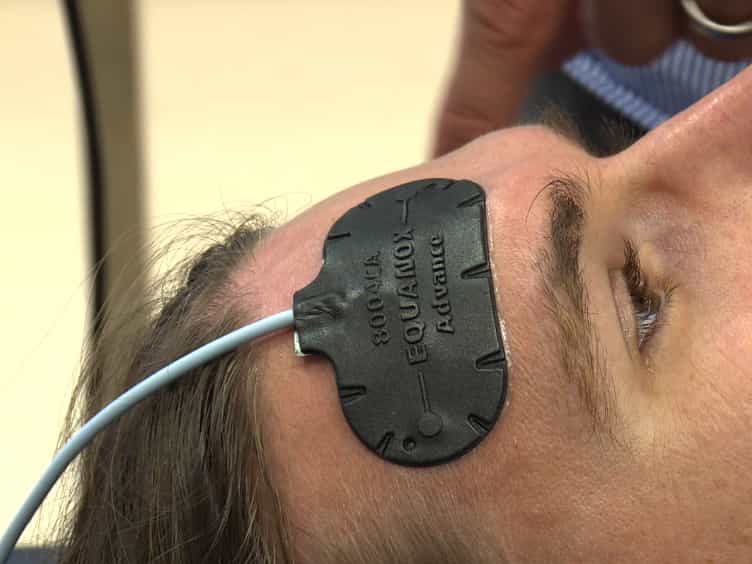
Alterations in cerebral blood flow (CBF) and cerebral oxygenation are implicated in altitude-associated diseases. We assessed the dynamic changes in CBF and peripheral and cerebral oxygenation engendered by ascent to altitude with partial acclimatization and hyperventilation using a combination of near-infrared spectroscopy, transcranial Doppler ultrasound, and diffuse correlation spectroscopy.
Methods:
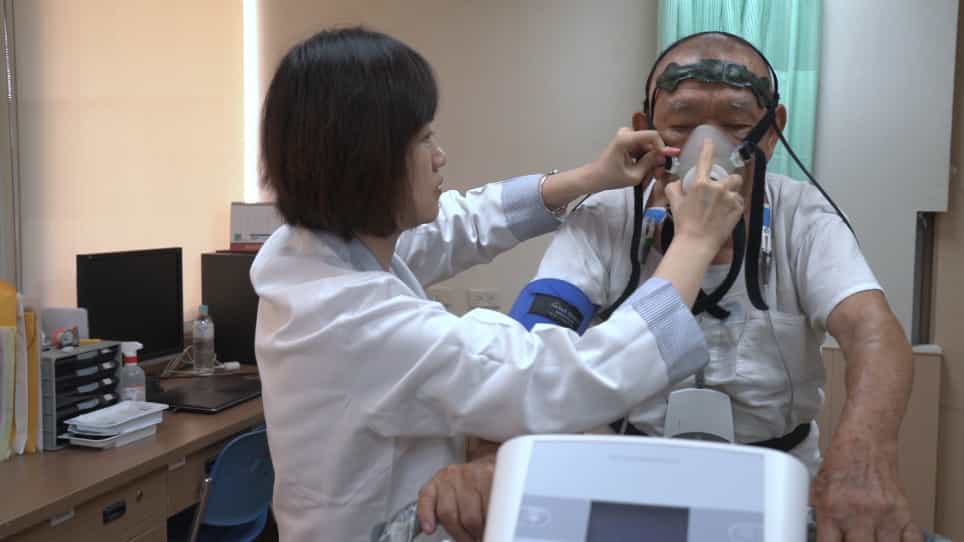
Peripheral (Spo2) and cerebral (Scto2) oxygenation, end-tidal carbon dioxide (ETCO2), and cerebral hemodynamics were studied in 12 subjects using transcranial Doppler and diffuse correlation spectroscopy (DCS) at 75 m and then 2 days and 7 days after ascending to 4559 m above sea level. After obtaining baseline measurements, subjects hyperventilated to reduce baseline ETCO2 by 50%, and a further set of measurements were obtained.
Results:
Cerebral oxygenation and peripheral oxygenation showed a divergent response, with cerebral oxygenation decreasing at day 2 and decreasing further at day 7 at altitude, whereas peripheral oxygenation decreased on day 2 before partially rebounding on day 7. Cerebral oxygenation decreased after hyperventilation at sea level (Scto2 from 68.8% to 63.5%; P<.001), increased after hyperventilation after 2 days at altitude (Scto2 from 65.6% to 69.9%; P=.001), and did not change after hyperventilation after 7 days at altitude (Scto2 from 62.2% to 63.3%; P=.35).
Conclusions:
An intensification of the normal cerebral hypocapnic vasoconstrictive response occurred after partial acclimatization in the setting of divergent peripheral and cerebral oxygenation. This may help explain why hyperventilation fails to improve cerebral oxygenation after partial acclimatization as it does after initial ascent. The use of DCS is feasible at altitude and provides a direct measure of CBF indices with high temporal resolution.
Related Concept Videos
 01:24
Factors Affecting Respiration
 01:25
Hyperpnea and Hyperventilation
 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...