Related Experiment Video
Updated: Apr 15, 2026
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Bronchus anastomosis after sleeve resection for lung cancer: does the suture technique have an impact on
Emanuel Palade1, Holger Holdt2, Bernward Passlick3
1Department of Thoracic Surgery, Medical University Freiburg, Freiburg, Germany Clinic for Surgery, University of Schleswig-Holstein, Lübeck, Germany emanuel.palade@uksh.de.

Objectives:
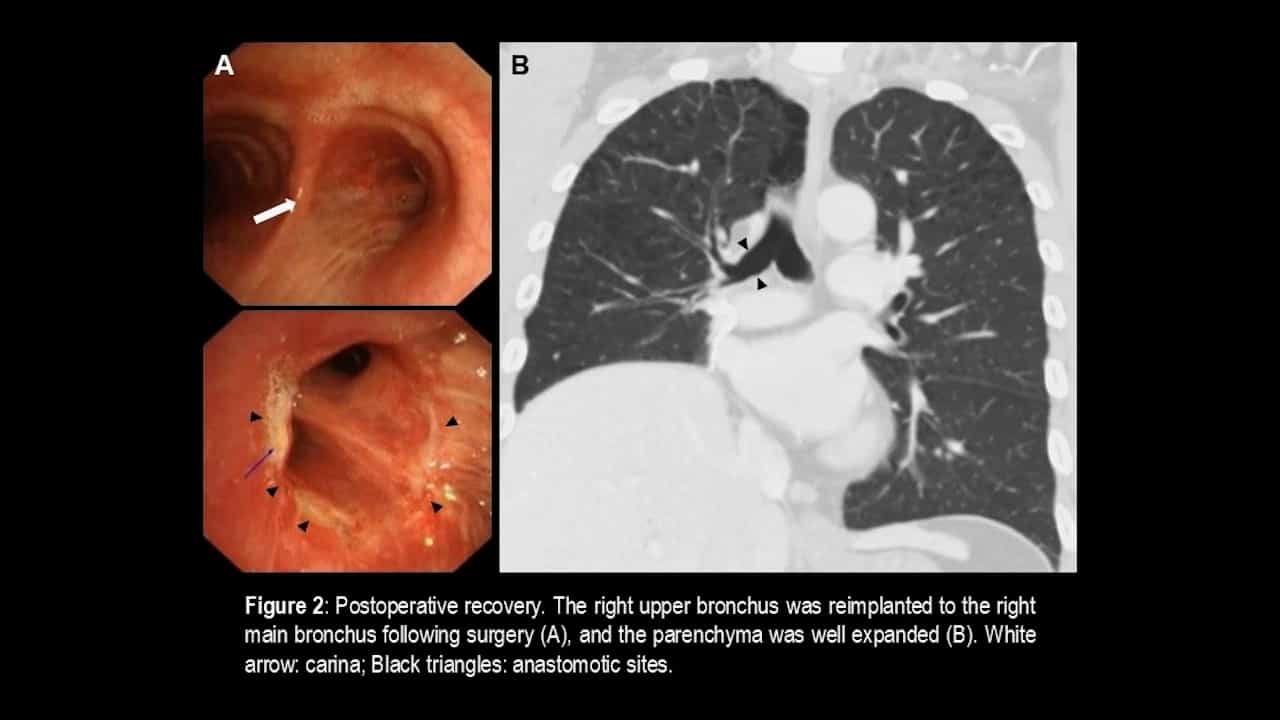
Bronchoplastic resections emerged as an alternative to pneumonectomy for patients with impaired pulmonary function and have gained popularity due to a marked decrease in morbidity and at least similar oncological outcome. Actual guidelines recommend sleeve resections whenever technically feasible, even in cases with adequate pulmonary reserve for pneumonectomy, in order to maximally preserve functional lung parenchyma. Various suture techniques were described; the existing evidence, however, is insufficient to recommend one of them as standard. The aim of this study was to compare two suture techniques for bronchus repair after sleeve resection.
Methods:
Two groups of patients from two separate institutions were retrospectively analysed. In Group A (n = 20), the anastomosis was performed with a running suture at the membranous part and an interrupted suture for the rest of the circumference. In Group B (n = 40), a telescoping continuous suture was used. Intra- and postoperative findings directly related to the anastomosis were compared. The parameters were assessed as absolute numbers and percentages; the statistical significance was determined using Pearson's χ(2) test for categorical variables and Student's t-test for continuous data (P < 0.05 considered as significant).
Results:
Other than tumour location and resection type (predominance of the right upper lobe for Group B), the groups were comparable regarding patient characteristics. The intraoperative anastomotic assessment revealed: patency 100% in both groups, initial air tightness (100 vs 82.5%; P = 0.047) and buttressing 85 vs 5%. No suture revision was necessary in both groups. The analysis of anastomosis-related morbidity revealed no significant difference: atelectasis (1 in Group A and 2 in Group B; P = 1), reversible anastomotic changes (0 vs 2; P = 0.309), early stenosis (0 vs 0), bronchopleural fistula (1 vs 0; P = 0.154), bronchovascular fistula (0 vs 0), late stenosis (1 vs 0; P = 0.119) and reoperations (15 vs 5%; P = 0.186). The operative mortality rate was similar (2 vs 3; P = 0.741) without intraoperative deaths.
Conclusions:
Sleeve resections are technically challenging, especially concerning the tension in the suture and size mismatch. In our series, there was no significant difference between the two groups regarding parameters directly related to the anastomosis. The interrupted suture without telescoping is the most cited technique, can be performed in several variations and can universally be used with good ability to compensate size mismatch. The telescoping continuous anastomosis is less time- and material-consuming and is especially valuable for large-calibre bronchi and relevant size mismatch.