Related Experiment Video
Updated: Apr 15, 2026


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
End tidal-to-arterial CO2 and O2 gas gradients at low- and high-altitude during dynamic end-tidal forcing
Michael M Tymko1, Philip N Ainslie1, David B MacLeod2
1Centre for Heart, Lung, and Vascular Health, School of Health and Exercise Science, University of British Columbia, Kelowna, Canada; and.

Abstract:
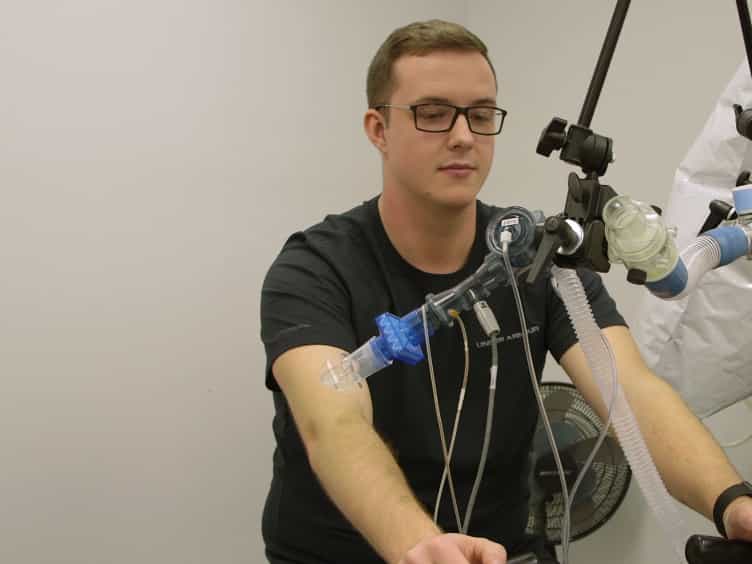
We sought to characterize and quantify the performance of a portable dynamic end-tidal forcing (DEF) system in controlling the partial pressure of arterial CO2 (Pa(CO2)) and O2 (Pa(O2)) at low (LA; 344 m) and high altitude (HA; 5,050 m) during an isooxic CO2 test and an isocapnic O2 test, which is commonly used to measure ventilatory and vascular reactivity in humans (n = 9). The isooxic CO2 tests involved step changes in the partial pressure of end-tidal CO2 (PET(CO2)) of -10, -5, 0, +5, and +10 mmHg from baseline. The isocapnic O2 test consisted of a 10-min hypoxic step (PET(O2) = 47 mmHg) from baseline at LA and a 5-min euoxic step (PET(O2) = 100 mmHg) from baseline at HA. At both altitudes, PET(O2) and PET(CO2) were controlled within narrow limits (<1 mmHg from target) during each protocol. During the isooxic CO2 test at LA, PET(CO2) consistently overestimated Pa(CO2) (P < 0.01) at both baseline (2.1 ± 0.5 mmHg) and hypercapnia (+5 mmHg: 2.1 ± 0.7 mmHg; +10 mmHg: 1.9 ± 0.5 mmHg). This P(a)-PET(CO2) gradient was approximately twofold greater at HA (P < 0.05). At baseline at both altitudes, PET(O2) overestimated Pa(O2) by a similar extent (LA: 6.9 ± 2.1 mmHg; HA: 4.5 ± 0.9 mmHg; both P < 0.001). This overestimation persisted during isocapnic hypoxia at LA (6.9 ± 0.6 mmHg) and during isocapnic euoxia at HA (3.8 ± 1.2 mmHg). Step-wise multiple regression analysis, on the basis of the collected data, revealed that it may be possible to predict an individual's arterial blood gases during DEF. Future research is needed to validate these prediction algorithms and determine the implications of end-tidal-to-arterial gradients in the assessment of ventilatory and/or vascular reactivity.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:20
Gas Exchange and Transport
 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:24
External and Internal Respiration
 01:27
Oxygen Transport in the Blood
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...