Syrinx location and size according to etiology: identification of Chiari-associated syrinx
Related Experiment Video
Updated: Apr 15, 2026

Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Jennifer Strahle1, Karin M Muraszko1, Hugh J L Garton1
1Department of Neurosurgery, University of Michigan, Ann Arbor, Michigan.

Abstract:
OBJECT Syrinx size and location within the spinal cord may differ based on etiology or associated conditions of the brain and spine. These differences have not been clearly defined. METHODS All patients with a syrinx were identified from 14,118 patients undergoing brain or cervical spine imaging at a single institution over an 11-year interval. Syrinx width, length, and location in the spinal cord were recorded. Patients were grouped according to associated brain and spine conditions including Chiari malformation Type I (CM-I), secondary CM (2°CM), Chiari malformation Type 0 (CM-0), tethered cord, other closed dysraphism, and spinal tumors. Syringes not associated with any known brain or spinal cord condition were considered idiopathic. Syrinx characteristics were compared between groups. RESULTS A total of 271 patients with a syrinx were identified. The most common associated condition was CM-I (occurring in 117 patients [43.2%]), followed by spinal dysraphism (20 [7.4%]), tumor (15 [5.5%]), and tethered cord (13 [4.8%]). Eighty-three patients (30.6%) did not have any associated condition of the brain or spinal cord and their syringes were considered idiopathic. Syringes in patients with CM-I were wide (7.8 ± 3.9 mm) compared with idiopathic syringes (3.9 ± 1.0, p < 0.0001) and those associated with tethered cord (4.2 ± 0.9, p < 0.01). When considering CM-I-associated and idiopathic syringes, the authors found that CM-I-associated syringes were more likely to have their cranial extent in the cervical spine (88%), compared with idiopathic syringes (43%; p < 0.0001). The combination of syrinx width greater than 5 mm and cranial extent in the cervical spine had 99% specificity (95% CI 0.92-0.99) for CM-I-associated syrinx. CONCLUSIONS Syrinx morphology differs according to syrinx etiology. The combination of width greater than 5 mm and cranial extent in the cervical spine is highly specific for CM-I-associated syringes. This may have relevance when determining the clinical significance of syringes in patients with low cerebellar tonsil position.
Related Concept Videos
 01:54
The Spinal Cord
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:18
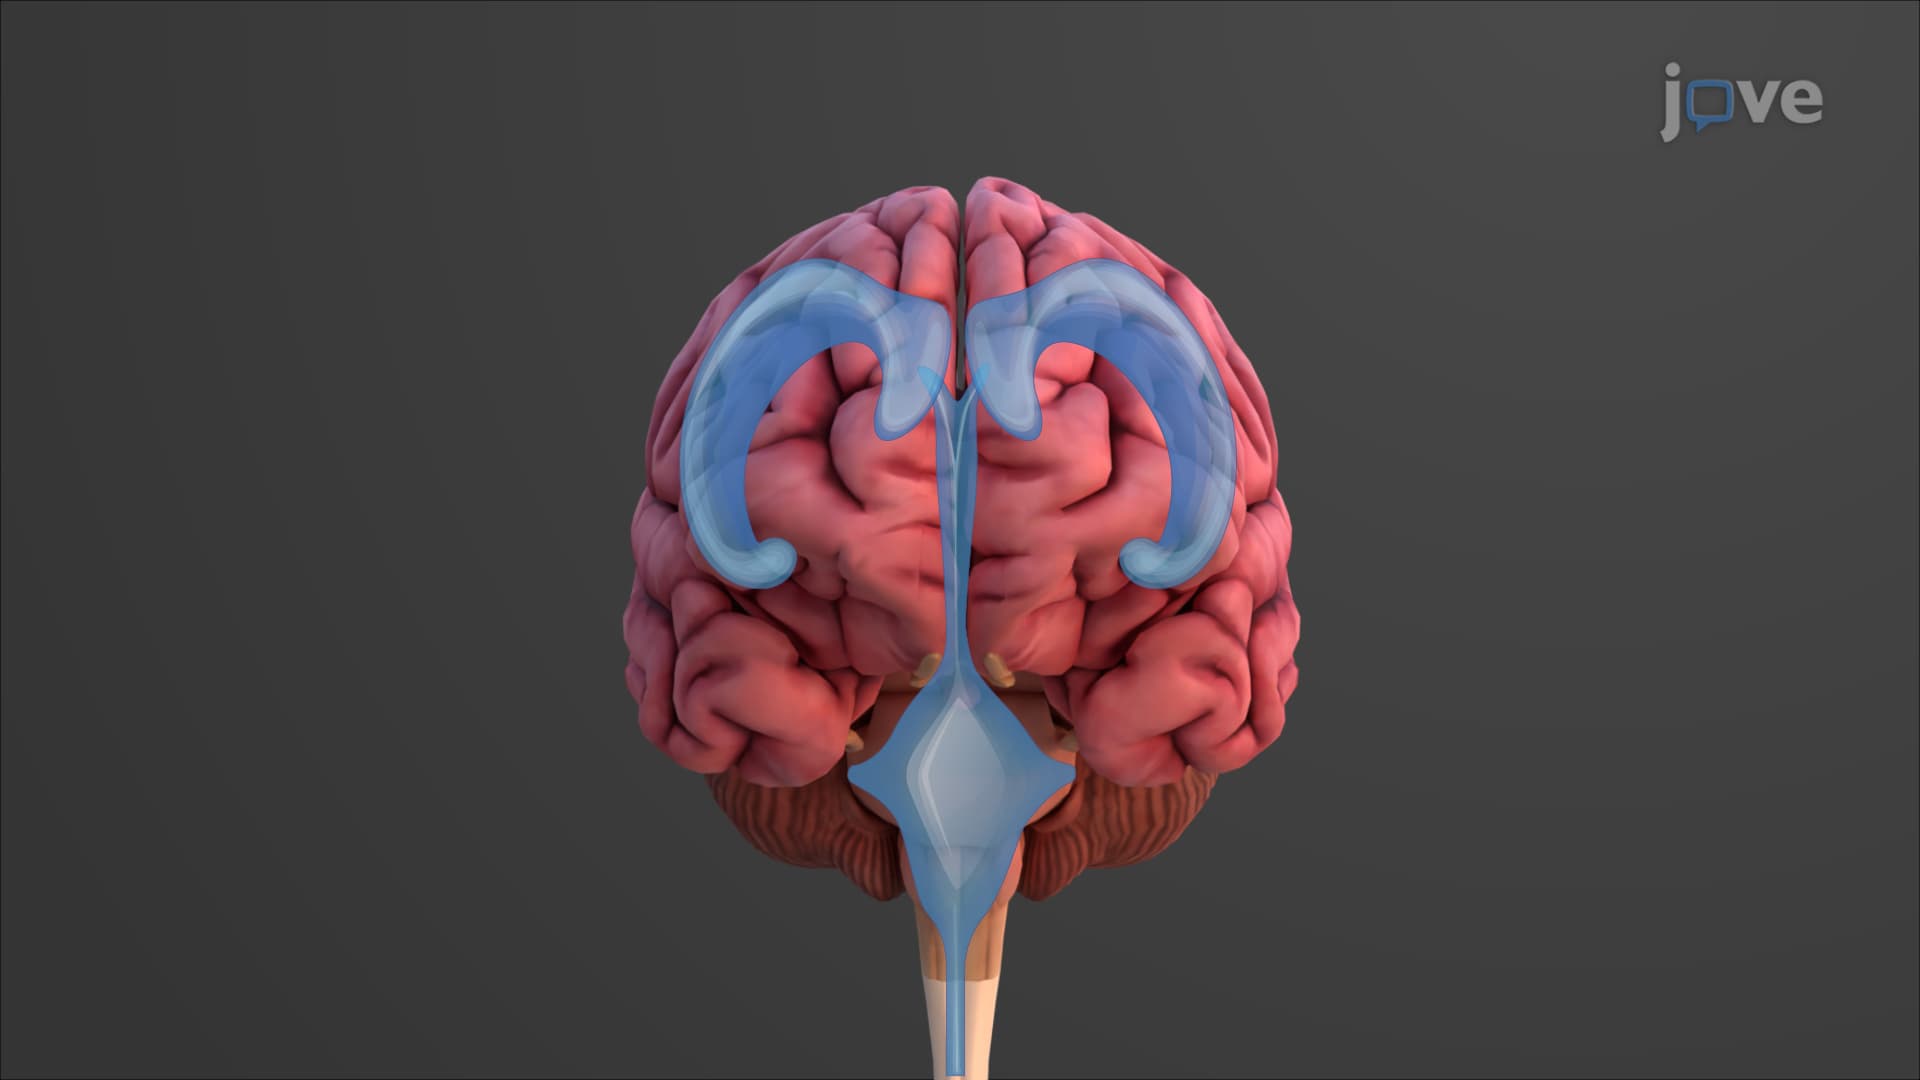
Anatomy of the Brain: Ventricles
 01:16
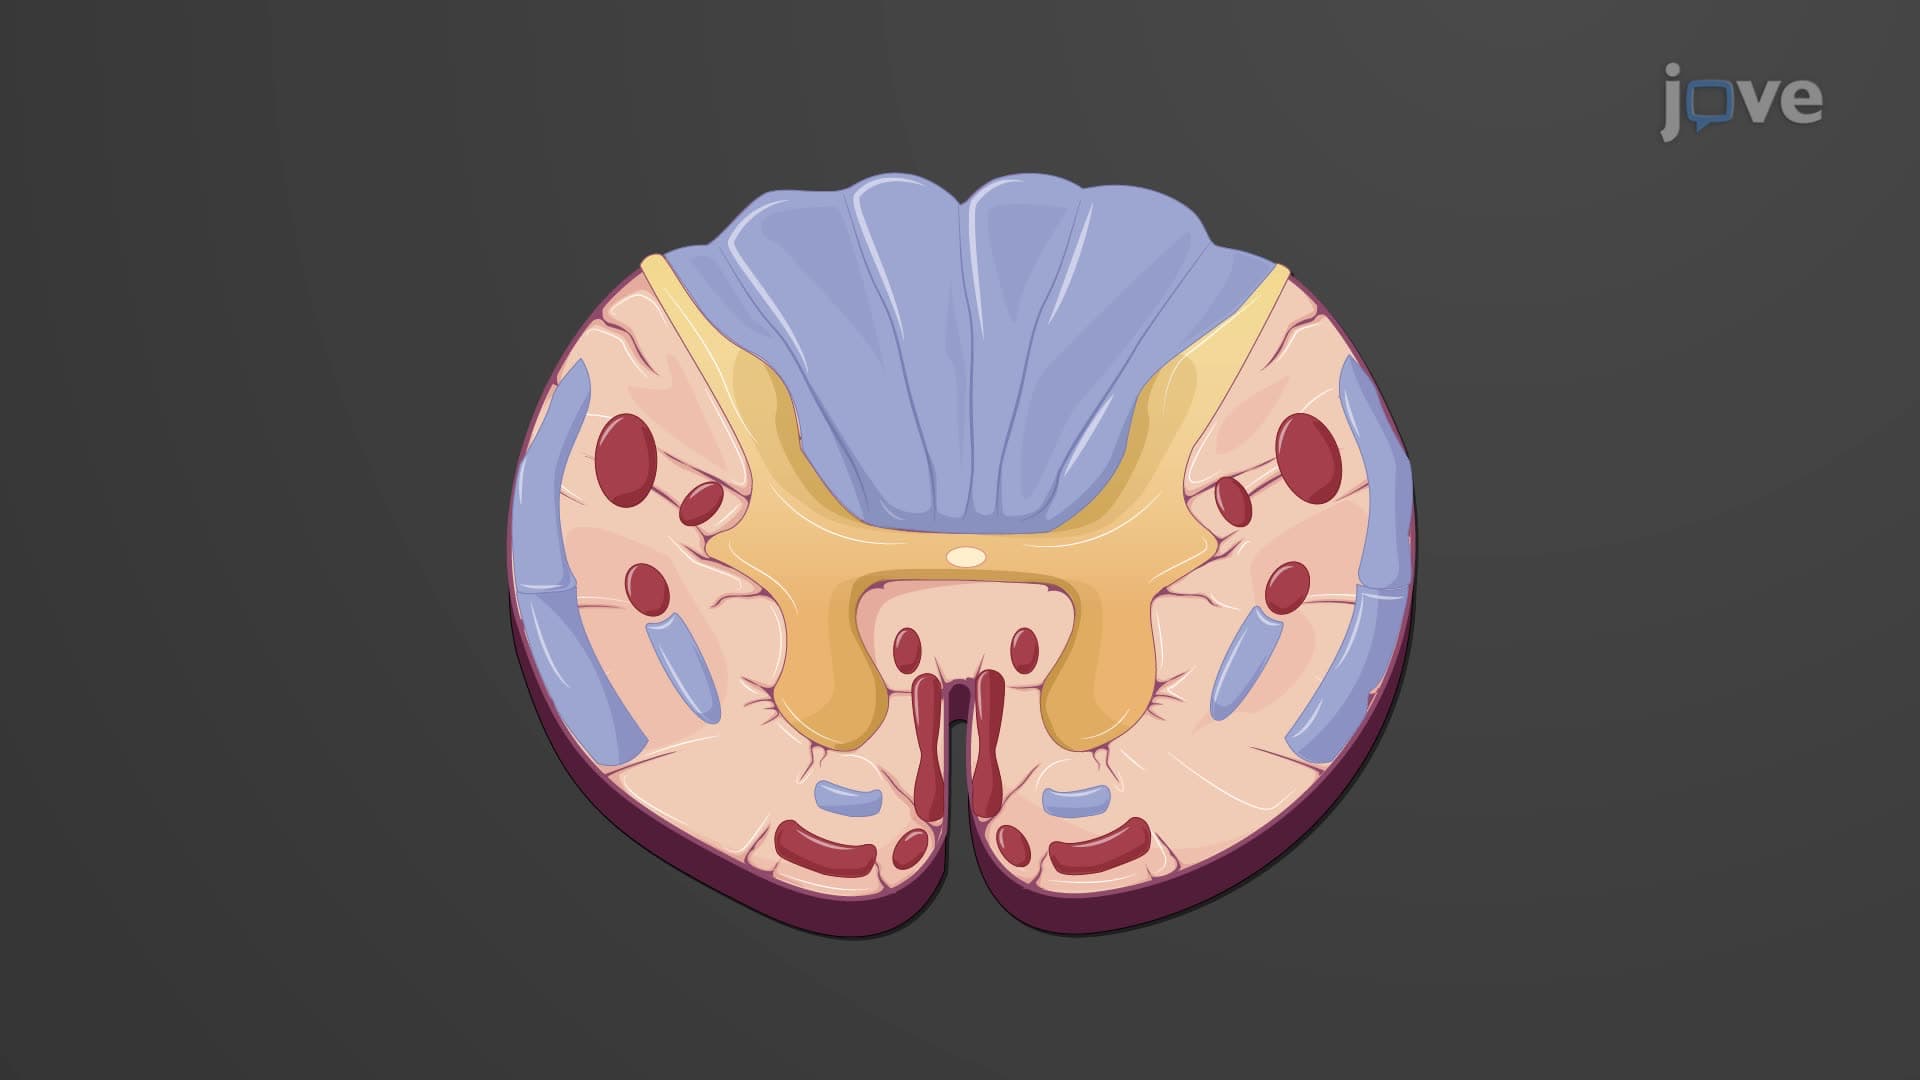
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...