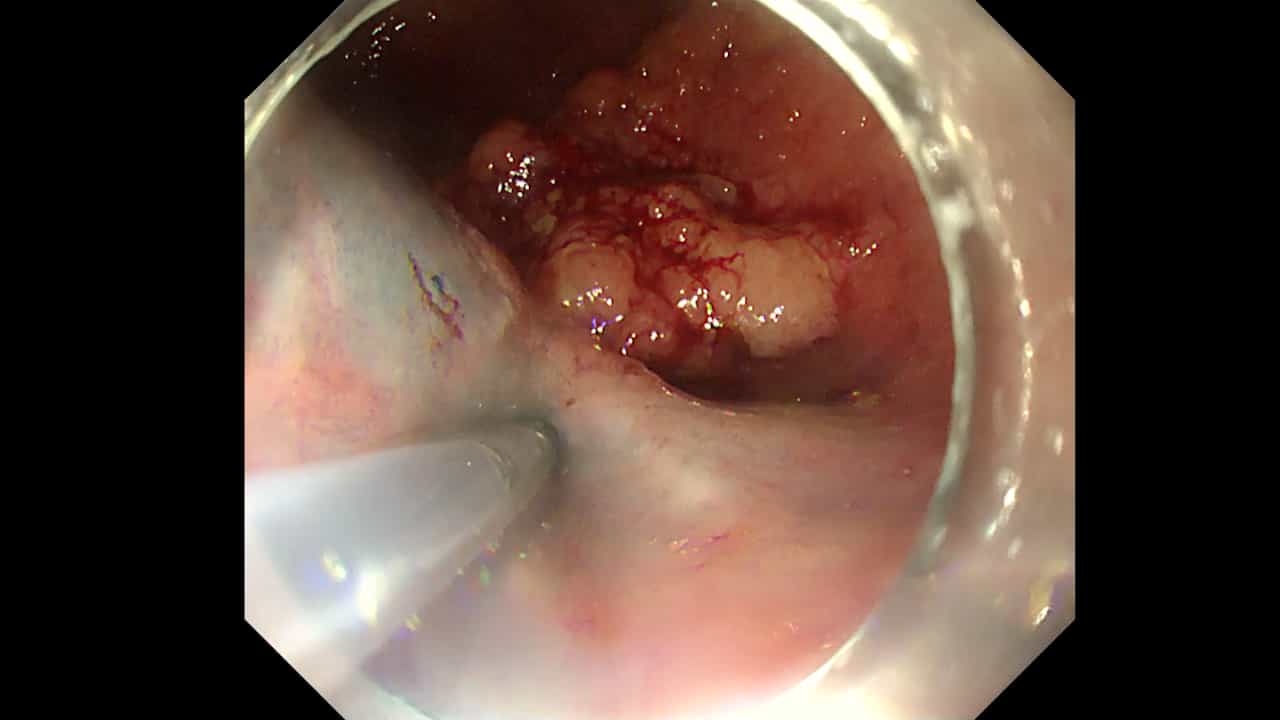
Related Experiment Video
Updated: Apr 15, 2026

Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Chemoradiation therapy for rectal cancer in the distal rectum followed by organ-sparing transanal endoscopic
M Verseveld1, E J R de Graaf, C Verhoef
1Department of Surgery, IJsselland Hospital, Capelle aan den IJssel, Rotterdam, The Netherlands; Division of Surgical Oncology, Department of Surgery, Erasmus MC Cancer Institute, Rotterdam, The Netherlands.

Background:
This prospective multicentre study was performed to quantify the number of patients with minimal residual disease (ypT0-1) after neoadjuvant chemoradiotherapy and transanal endoscopic microsurgery (TEM) for rectal cancer.
Methods:
Patients with clinically staged T1-3 N0 distal rectal cancer were treated with long-course chemoradiotherapy. Clinical response was evaluated 6-8 weeks later and TEM performed. Total mesorectal excision was advocated in patients with residual disease (ypT2 or more).
Results:
The clinical stage was cT1 N0 in ten patients, cT2 N0 in 29 and cT3 N0 in 16 patients. Chemoradiotherapy-related complications of at least grade 3 occurred in 23 of 55 patients, with two deaths from toxicity, and two patients did not have TEM or major surgery. Among 47 patients who had TEM, ypT0-1 disease was found in 30, ypT0 N1 in one, ypT2 in 15 and ypT3 in one. Local recurrence developed in three of the nine patients with ypT2 tumours who declined further surgery. Postoperative complications grade I-IIIb occurred in 13 of 47 patients after TEM and in five of 12 after (completion) surgery. After a median follow-up of 17 months, four local recurrences had developed overall, three in patients with ypT2 and one with ypT1 disease.
Conclusion:
TEM after chemoradiotherapy enabled organ preservation in one-half of the patients with rectal cancer.