
Ultrasound shear wave speed measurements correlate with liver fibrosis in children
Jonathan R Dillman1, Amer Heider, Jacob L Bilhartz
1Department of Radiology, University of Michigan Health System, Section of Pediatric Radiology, C. S. Mott Children's Hospital, 1540 E. Hospital Drive, Ann Arbor, MI, 48109, USA, jonadill@med.umich.edu.

Insights
Ultrasound shear wave speed (SWS) measurements correlate with liver fibrosis in children. Higher SWS values indicate more severe liver fibrosis, offering a noninvasive assessment tool.
Area of Science:
- Pediatric Hepatology
- Medical Imaging
- Noninvasive Diagnostics
Background:
- Limited research exists on noninvasive ultrasound shear wave speed (SWS) measurements and liver fibrosis in pediatric patients.
- Percutaneous liver biopsy is the current standard for assessing fibrosis but is invasive.
Purpose of the Study:
- To evaluate the correlation between liver ultrasound shear wave speed (SWS) measurements and the degree of hepatic fibrosis in children.
- To establish the utility of SWS as a noninvasive biomarker for liver fibrosis in pediatric populations.
Main Methods:
- Sixty-two children underwent same-day ultrasound shear wave elastography (SWE) and percutaneous liver biopsy.
- Ultrasound shear wave speed (SWS) was measured using Virtual Touch Quantification (VTQ) and Virtual Touch IQ (VTIQ) modes.
- Histological fibrosis and inflammation scores from biopsy specimens were correlated with SWS measurements using regression analysis and ROC curves.
Main Results:
- Significant positive correlations were observed between liver histological fibrosis scores and mean SWS measurements from both VTQ (r=0.68) and VTIQ (r=0.73) modes (P<0.0001).
- Histological inflammation scores also showed significant positive correlations with SWS measurements (VTQ: r=0.47, VTIQ: r=0.44).
- VTQ and VTIQ demonstrated good diagnostic performance in distinguishing low from high liver fibrosis, with areas under the ROC curves of 0.84 and 0.86, respectively.
Conclusions:
- Liver ultrasound shear wave speed measurements increase with progressive hepatic fibrosis in children.
- SWS represents a promising noninvasive method for assessing liver fibrosis in pediatric patients.
Background:
Little published research has shown the relationship between noninvasive US shear wave speed (SWS) measurements and degree of liver fibrosis as established by percutaneous biopsy in children.
Objective:
To assess the relationship between liver US shear wave speed (SWS) measurements and parenchymal fibrosis in children.
Materials And Methods:
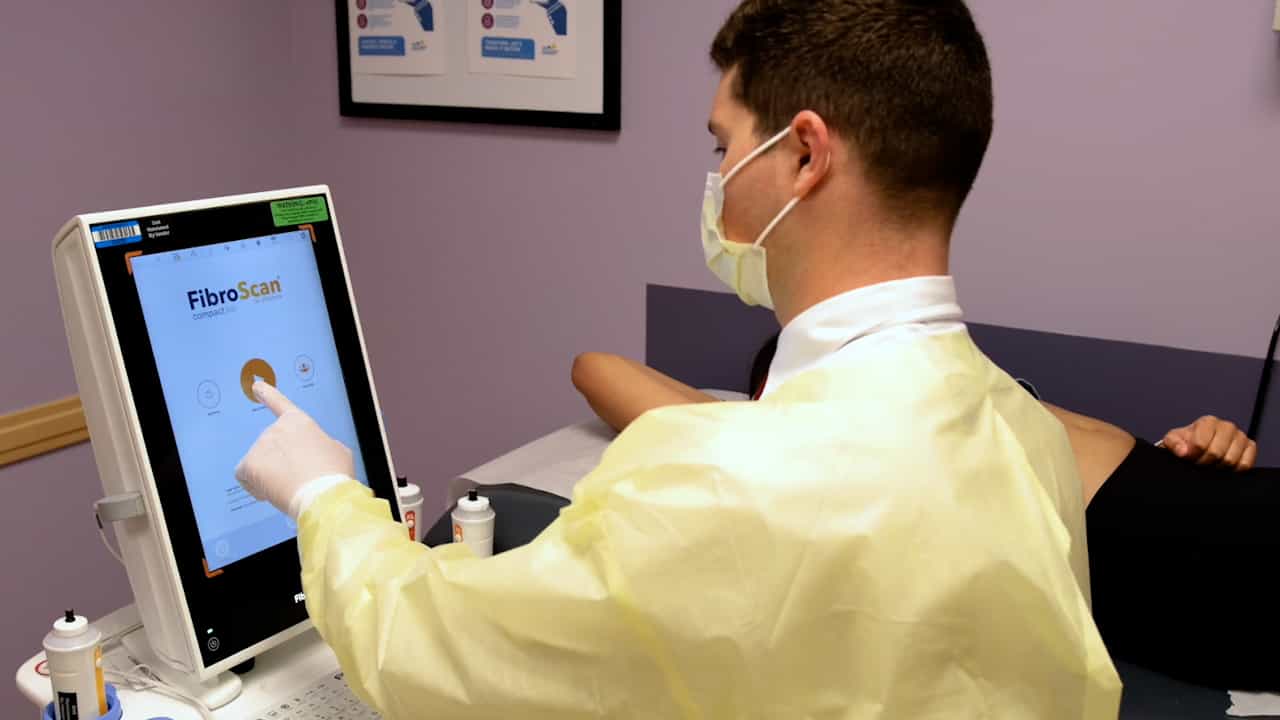
Sixty-two children (0-18 years old) with known or suspected liver disease underwent same-day US shear wave elastography (SWE) and clinically ordered percutaneous core needle biopsy. SWE was performed just before the liver biopsy in the area targeted for sampling, using an Acuson S3000 US system with a 9L4 transducer; six SWS measurements were acquired using Virtual Touch Quantification (VTQ) and Virtual Touch IQ (VTIQ) modes. Biopsy specimens were scored for histological fibrosis and inflammation. Bivariate relationships were assessed using Pearson correlation, while multiple linear regression analysis was used to establish the relationship between SWS and predictor variables. Receiver operating characteristic (ROC) curves were created to assess the abilities of VTQ and VTIQ to discern low vs. high liver fibrosis (histological fibrosis scores 0-2 vs. 3-6).
Results:
There were significant positive correlations between liver histological fibrosis score and VTQ (n = 49) and VTIQ (n = 48) mean shear wave speed measurements (r = 0.68 and r = 0.73; P-values <0.0001). There also were significant positive correlations between liver histological inflammation score and VTQ and VTIQ mean shear wave speed measurements (r = 0.47 and r = 0.44, and P = 0.0006 and P = 0.0016, respectively). For VTQ, both histological fibrosis (P < 0.0001) and inflammation (P = 0.04) scores were significant predictors of shear wave speed (model adjusted R (2) = 0.49). For VTIQ, only histological fibrosis score (P < 0.0001) was a significant predictor of shear wave speed (model adjusted R (2) = 0.56). ROC areas under the curve were 0.84 and 0.86 for VTQ and VTIQ, respectively.
Conclusion:
Liver US shear wave speed measurements increase with increasing parenchymal fibrosis in children.