
Standard dosing of amikacin and gentamicin in critically ill patients results in variable and subtherapeutic
Claire Roger1, Bastian Nucci2, Nicolas Molinari3
1Service des reanimations, Pôle Anesthésie Réanimation Douleur Urgence, CHU Nîmes, Place du Professeur Robert Debré, 30 029 Nîmes Cedex 9, France; EA 2992, Faculté de Médicine Montpellier Nîmes, Avenue JF Kennedy, 30 000 Nîmes, France.

Abstract:
Low peak plasma concentrations (Cmax) of amikacin and gentamicin are reported in intensive care unit (ICU) patients after administration of the first dose. The present study aimed to describe the proportion of ICU patients in whom an adequate Cmax was achieved throughout the course of therapy. Septic ICU patients with an indication for intravenous amikacin or gentamicin were eligible for inclusion in this single-centre observational study. The first and subsequent doses and the corresponding Cmax values were recorded. The target Cmax was ≥60mg/L for amikacin and ≥30mg/L for gentamicin. Amikacin and gentamicin plasma concentrations were available in 66 and 24 patients, respectively (59±17 years; 79±19kg; height 169±12cm; SAPS II score 46±19). Pulmonary, abdominal and urinary tract infections were diagnosed in 64 patients. Culture-positive infection was confirmed in 65 patients (72%). A target first Cmax was achieved in 17/90 patients (19%). For amikacin, the target Cmax was achieved in 16/66 patients (24%) after the initial dose. In the 50 remaining patients, a change in dosing was performed in 14 patients, leading adequate peak plasma level in 2 patients. For gentamicin, the targeted Cmax was achieved in only 1/24 patient (4%) after the initial dose and was never achieved after the third dose. In conclusion, standard dosing of amikacin or gentamicin led to adequate Cmax in only 19% of patients. Subtherapeutic Cmax were not significantly corrected after subsequent doses.
Insights
Standard dosing of amikacin and gentamicin in intensive care unit (ICU) patients frequently fails to achieve therapeutic peak plasma concentrations (Cmax). Most patients did not reach adequate Cmax levels, even with dose adjustments, highlighting a critical need for optimized dosing strategies.
Area of Science:
- Pharmacology
- Critical Care Medicine
- Infectious Diseases
Background:
- Low peak plasma concentrations (Cmax) of amikacin and gentamicin are common in intensive care unit (ICU) patients.
- Achieving adequate Cmax is crucial for effective antibiotic therapy and preventing resistance.
Purpose of the Study:
- To determine the proportion of septic ICU patients achieving adequate Cmax of amikacin or gentamicin throughout therapy.
- To evaluate the effectiveness of standard dosing and dose adjustments in reaching target Cmax levels.
Main Methods:
- Single-centre observational study of septic ICU patients receiving intravenous amikacin or gentamicin.
- Recorded first and subsequent doses and measured Cmax values.
- Target Cmax: ≥60mg/L for amikacin, ≥30mg/L for gentamicin.
Main Results:
- Only 19% of patients achieved the target first Cmax (16/66 for amikacin, 1/24 for gentamicin).
- For amikacin, 24% achieved target Cmax initially; dose adjustments improved levels in only 2/14 patients.
- Gentamicin Cmax was inadequate in 96% of patients, with no improvement after the third dose.
Conclusions:
- Standard amikacin and gentamicin dosing is insufficient for achieving therapeutic Cmax in a majority of ICU patients.
- Subtherapeutic Cmax levels were poorly corrected by subsequent doses, indicating a need for revised dosing protocols in critically ill patients.

Related Concept Videos
 01:15
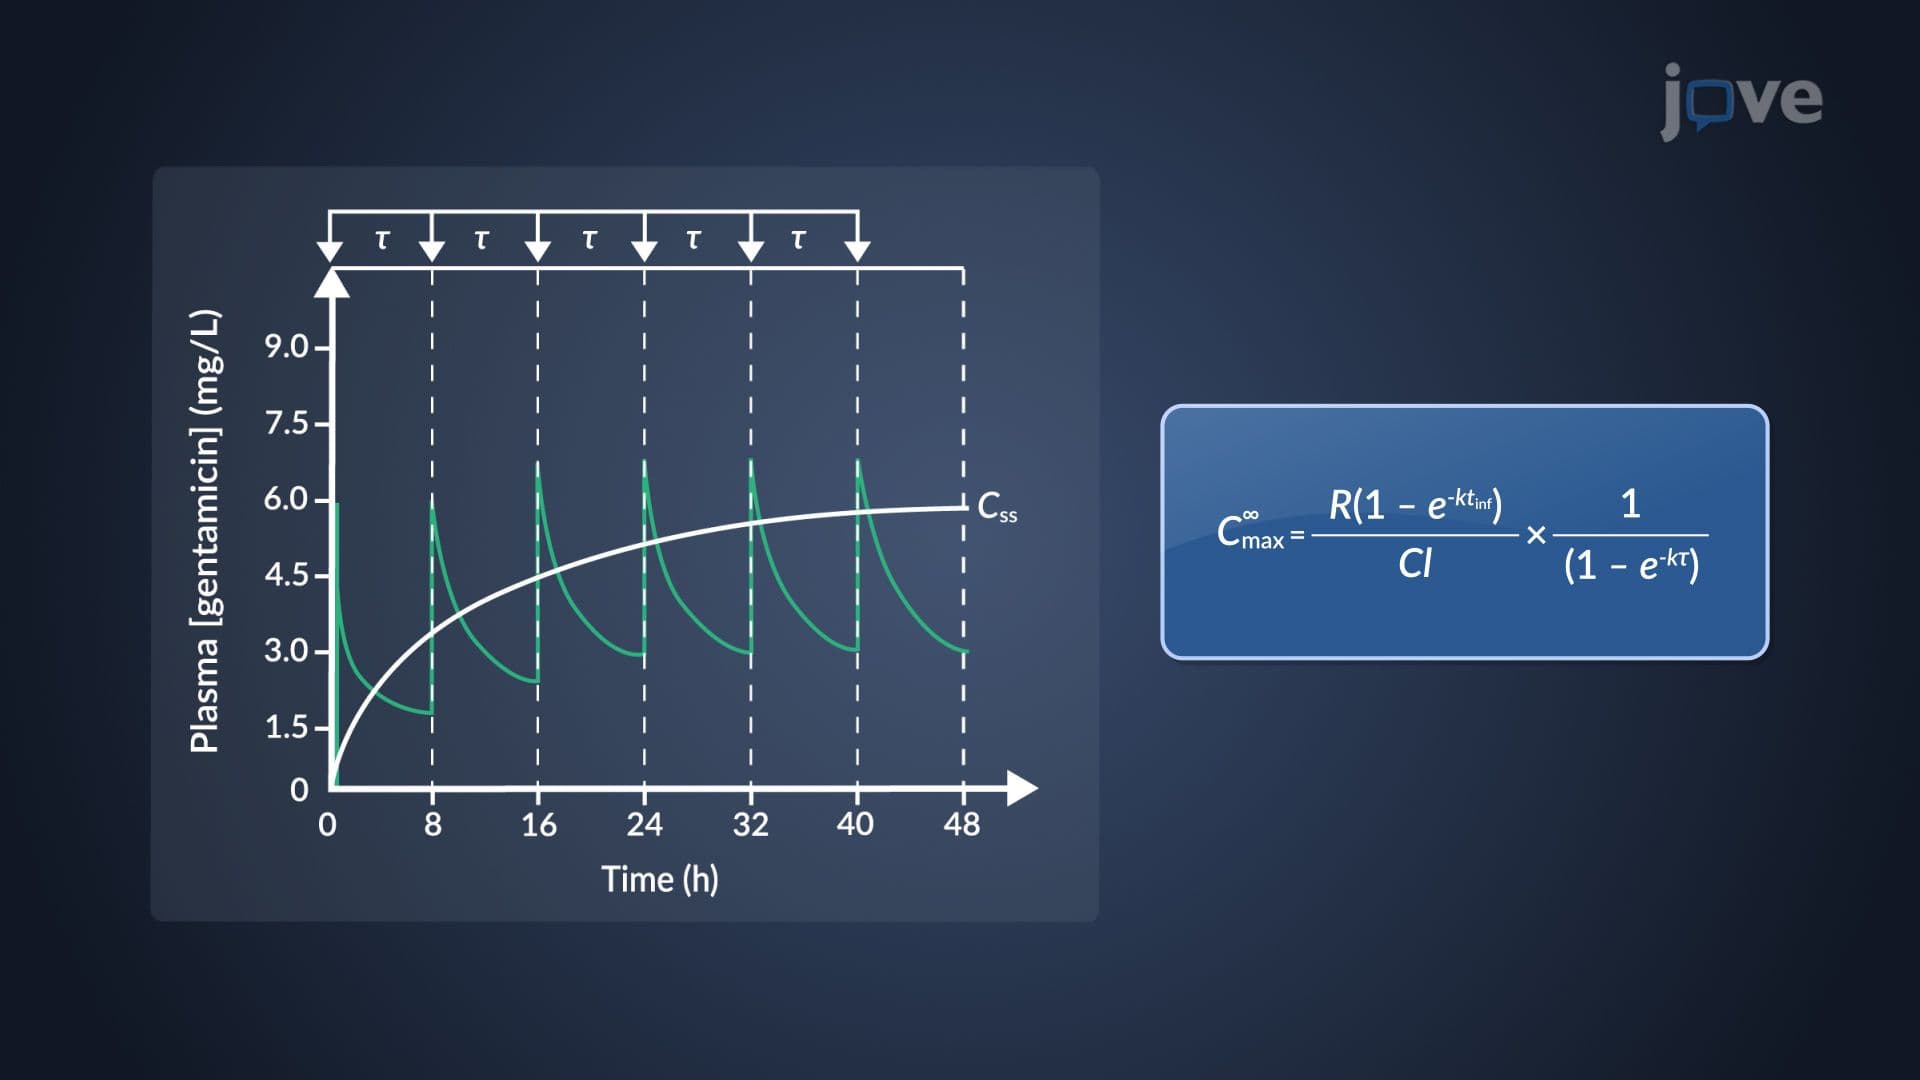
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
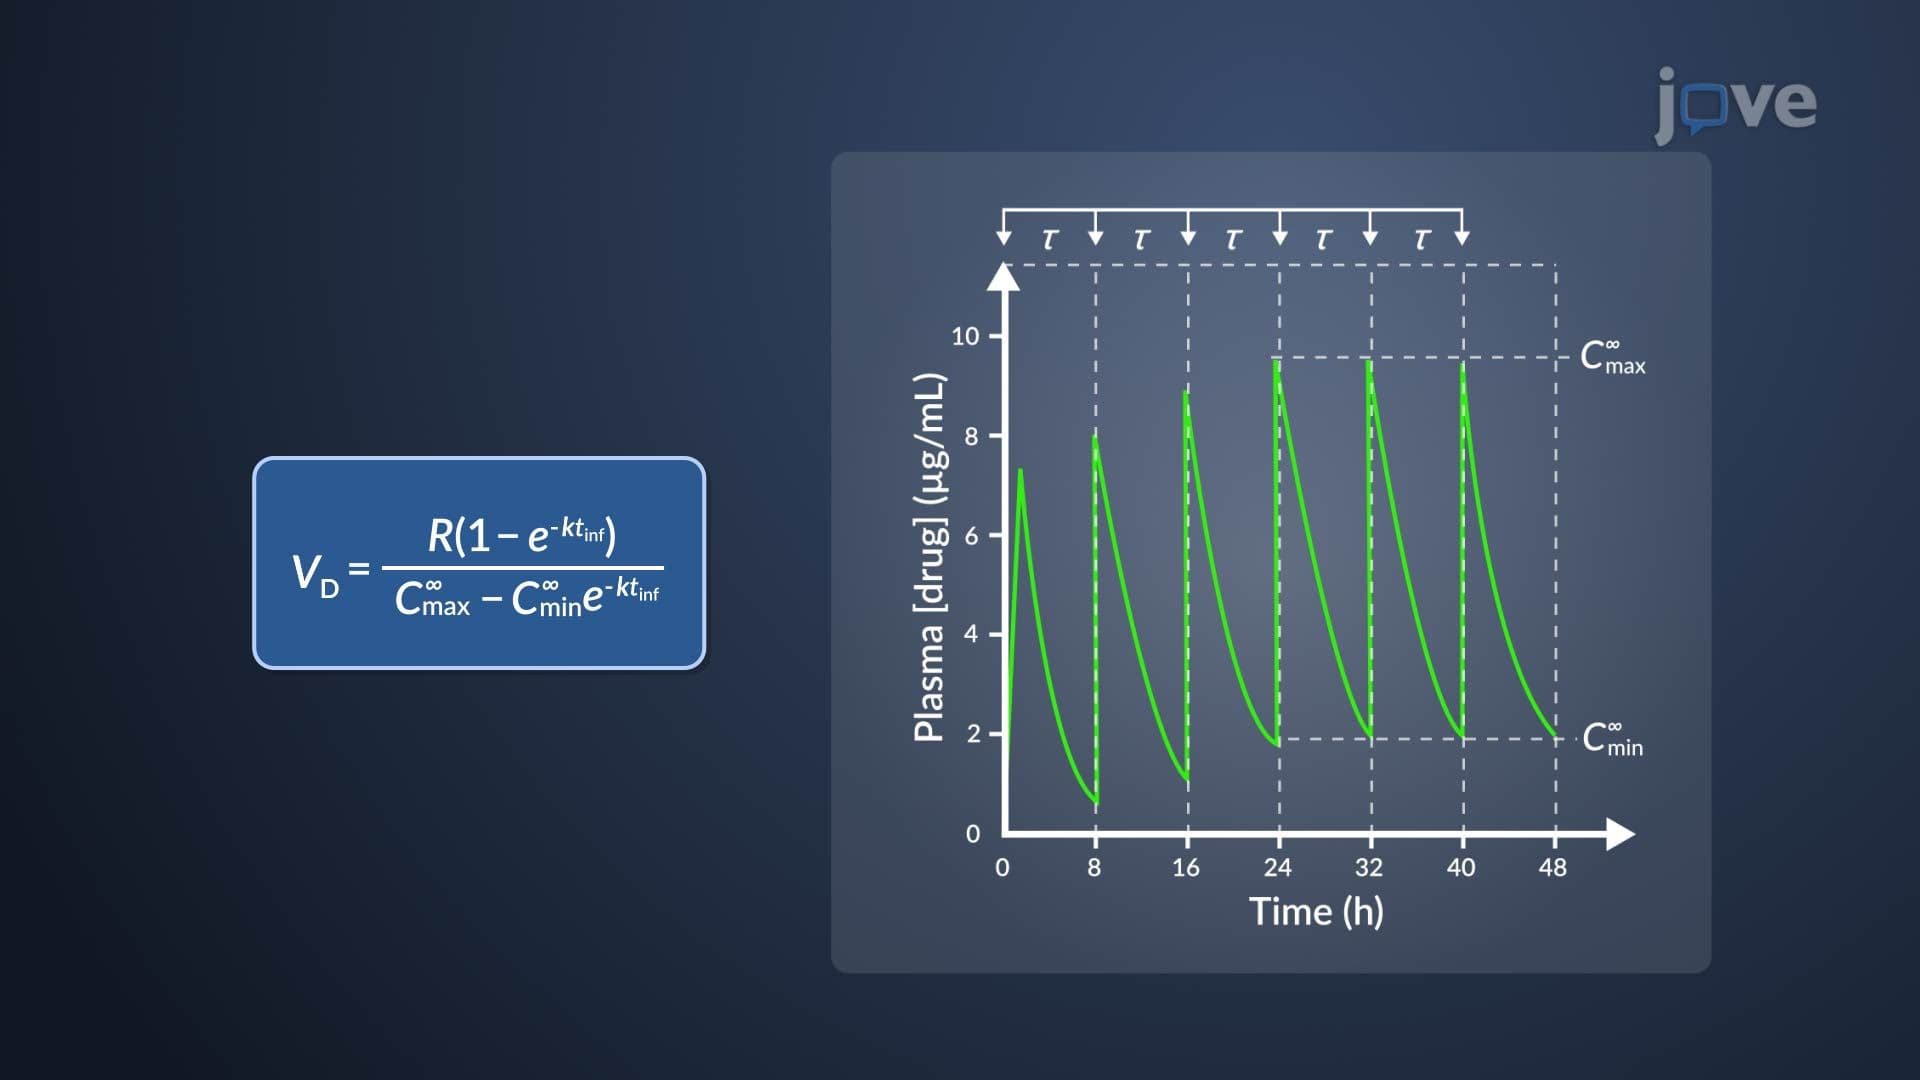
Estimation of k and VD of Aminoglycosides
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:20
Acute Kidney Injury V: Interprofessional Care