Related Experiment Video
Updated: Aug 25, 2026

Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
[Blood flow disturbance in digestive organs--a viewpoint of vascular surgery]
1Department of Surgery, Hamamatsu University, School of Medicine, Japan.

Abstract:
Various blood flow disturbances in intraabdominal digestive organs were studied clinically and experimentally from a viewpoint of vascular surgery. Acute gastric mucosal lesion may occur due to ischemia and reperfusion injury of the gastric mucosa. Bleeding from stomach ulcer may be rarely caused by consumption coagulopathy along with aortic aneurysm. Heparin therapy was successful to interrupt it. Gastrectomy is not indicated for such condition but aneurysm should be repaired. Portal vein reconstruction for the radical resection of hepatic, biliary and pancreatic cancers should be carefully made, because early or late stenosis occurs frequently, and they may connect to early or late morbidities or mortalities. On the other hand, resection and replacement of the suprarenal vena cava invaded by the retroperitoneal malignant tumor may be safely carried out. For the acute mesenteric arterial occlusion, early diagnosis and arterial reconstruction are essential to save catastrophe. Positive Doppler sound on the vasa recta seems to be the most reliable parameter for assessing bowel viability. Approach from the proximal large arteries is recommended for uncontrollable intraperitoneal bleeding.


Related Concept Videos
 01:29
Blood Flow
 01:17
Autoregulation of Blood Flow
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation.
 01:16
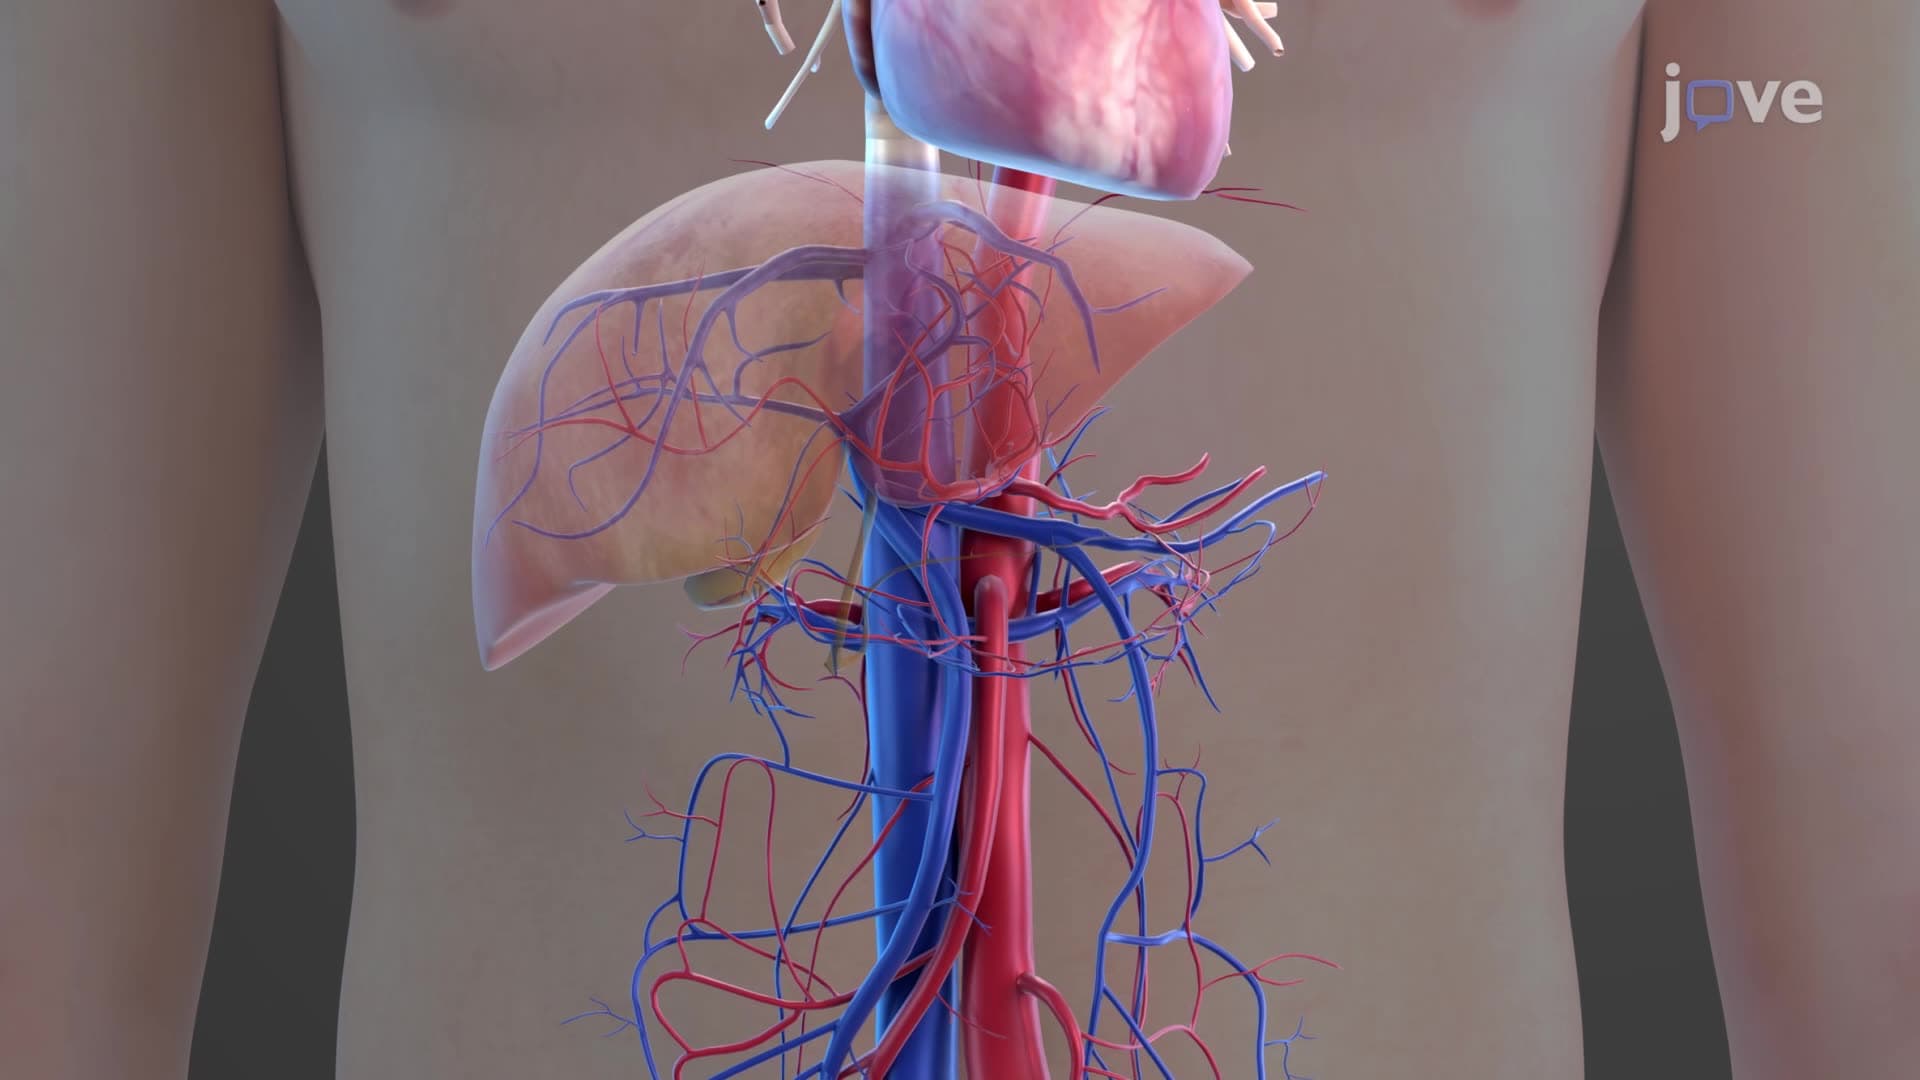
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
Portal Hypertension