Related Experiment Video
Updated: Apr 15, 2026


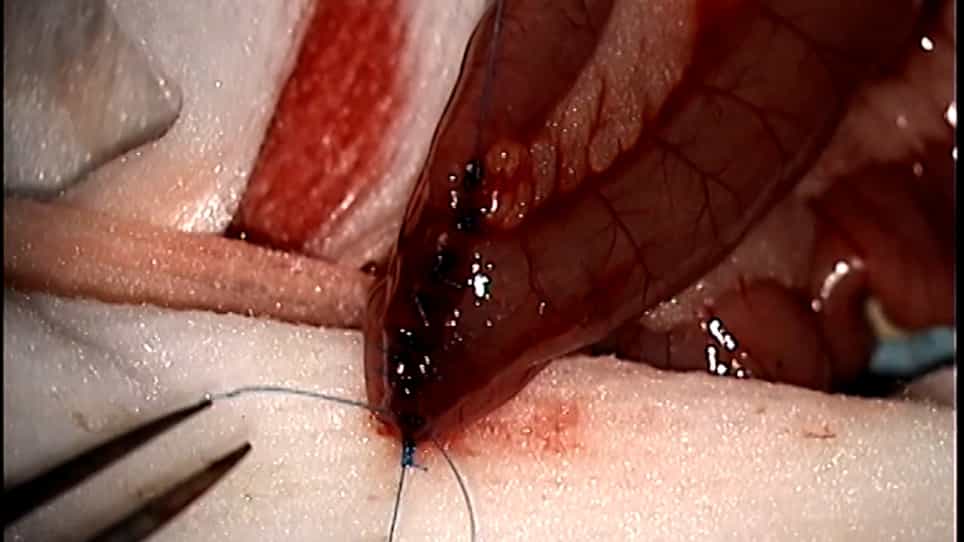
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Mechanisms of improved glycaemic control after Roux-en-Y gastric bypass
Kirstine Nyvold Bojsen-Møller1
1Department of Endocrinology, Hvidovre Hospital, Kettegårds Alle, 2650 Hvidovre. Denmark. kirstine.bojsen-moeller@regionh.dk.

Abstract:
Roux-en-Y gastric bypass (RYGB) surgery induces weight loss of 20-30% that is maintained for 20 years. In patients with type 2 diabetes, the glucose-lowering effect of RYGB is superior to conventional antidiabetic therapy and often occurs within days after surgery. The aim of the thesis was to investigate the physiological mechanisms responsible for improved glycaemic control with special focus on the early postoperative period. We therefore investigated insulin sensitivity, insulin clearance and pancreatic islet-cell function in patients with type 2 diabetes and in glucose tolerant subjects prior to and at 1 week, 3 months and 1 year after RYGB. Hepatic insulin sensitivity measured with a glucose tracer increased already 1 week after RYGB, whereas peripheral insulin sensitivity estimated with the hyperinsulinaemic euglycaemic clamp was unchanged. Concomitant increases in insulin clearance at 1 week further highlights the liver as an important organ responsible for the early effects on glucose metabolism after surgery since insulin predominantly is cleared by the liver. Rapid improvements in hepatic insulin sensitivity is a common observation after calorie restriction in obese patients and has been observed as early as after 48 hours in absence of major weight loss and changes in peripheral insulin sensitivity. Thus, calorie restriction is a likely explanation for our findings of early improvements in hepatic insulin sensitivity and insulin clearance after RYGB. Peripheral insulin sensitivity increased along with weight loss at 3 months and 1 year after RYGB. Beta-cell function increased after RYGB in patients with type 2 diabetes in response to oral glucose, whereas insulin secretion was unchanged in response to an intravenous (iv) glucose-glucagon test throughout the first year after surgery. In glucose tolerant subjects, the insulin response to iv glucose-glucagon declined after RYGB likely as an adaptation to increased insulin sensitivity. The secretion of glucagon-like peptide 1 (GLP-1) increased substantially in both groups in response to oral glucose, whereas the secretion of glucose-dependent insulinotropic poly-peptide (GIP) was largely unchanged postoperatively. The insulinotropic effects of the incretin hormones were preserved after surgery during iv infusion in glucose tolerant subjects. Increased insulin secretion postoperatively was thus linked to the oral and not the iv route of administration highlighting the importance of the changed gastrointestinal anatomy and the exaggerated GLP-1 secretion and not supporting major changes in intrinsic beta-cell function after RYGB. Changes in alpha-cell function did not seem to contribute substantially to the improved glycaemic control after RYGB, as glucagon secretion increased paradoxically after oral glucose, and suppression of glucagon in response to iv infusions of glucose, GIP, GLP-1 and insulin was largely unchanged postoperatively. In conclusion, improved glycaemic control after Roux-en-Y gastric bypass can be explained by early enhancements of hepatic insulin sensitivity and later improvements in peripheral insulin sensitivity in combination with increased postprandial insulin secretion linked to exaggerated postprandial GLP-1 secretion. Surgical changes in gut anatomy are likely to explain the increased GLP-1 secretion and hence the increased postprandial insulin secretion, whereas calorie restriction and subsequent weight loss may be the major cause of improved insulin sensitivity.

Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
 01:19
Oral Hypoglycemic Agents: α-Glucosidase Inhibitors
Acarbose and miglitol are...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:06
Oral Hypoglycemic Agents: Glinides
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution