Related Experiment Video
Updated: Apr 14, 2026

Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Skeletal muscle oxygenation in severe trauma patients during haemorrhagic shock resuscitation
Jerome Duret1, Julien Pottecher2,3, Pierre Bouzat4,5,6
1Pole Anesthésie-Réanimation, Hôpital Michallon, Boulevard de la Chantourne, Grenoble, F-38043, France. JDuret1@chu-grenoble.fr.

Introduction:
Early alterations in tissue oxygenation may worsen patient outcome following traumatic haemorrhagic shock. We hypothesized that muscle oxygenation measured using near-infrared spectroscopy (NIRS) on admission could be associated with subsequent change in the SOFA score after resuscitation.
Methods:
The study was conducted in two Level I trauma centres and included 54 consecutive trauma patients with haemorrhagic shock, presenting within 6 hours of injury. Baseline tissue haemoglobin oxygen saturation (StO2) in the thenar eminence muscle and StO2 changes during a vascular occlusion test (VOT) were determined at 6 hours (H6) and 72 hours (H72) after the admission to the emergency room. Patients showing an improved SOFA score at H72 (SOFA improvers) were compared to those for whom it was unchanged or worse (SOFA non-improvers).
Results:
Of the 54 patients, 34 patients were SOFA improvers and 20 SOFA non-improvers. They had comparable injury severity scores on admission. SOFA improvers had higher baseline StO2 values and a steeper StO2 desaturation slope at H6 compared to the SOFA non-improvers. These StO2 variables similarly correlated with the intra-hospital mortality. The StO2 reperfusion slope at H6 was similar between the two groups of patients.
Conclusions:
Differences in StO2 parameters on admission of traumatic haemorrhagic shock were found between patients who had an improvement in organ failure in the first 72 hours and those who had unchanged or worse conditions. The use of NIRS to guide the initial management of trauma patients with haemorrhagic shock warrants further investigations.

Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:20
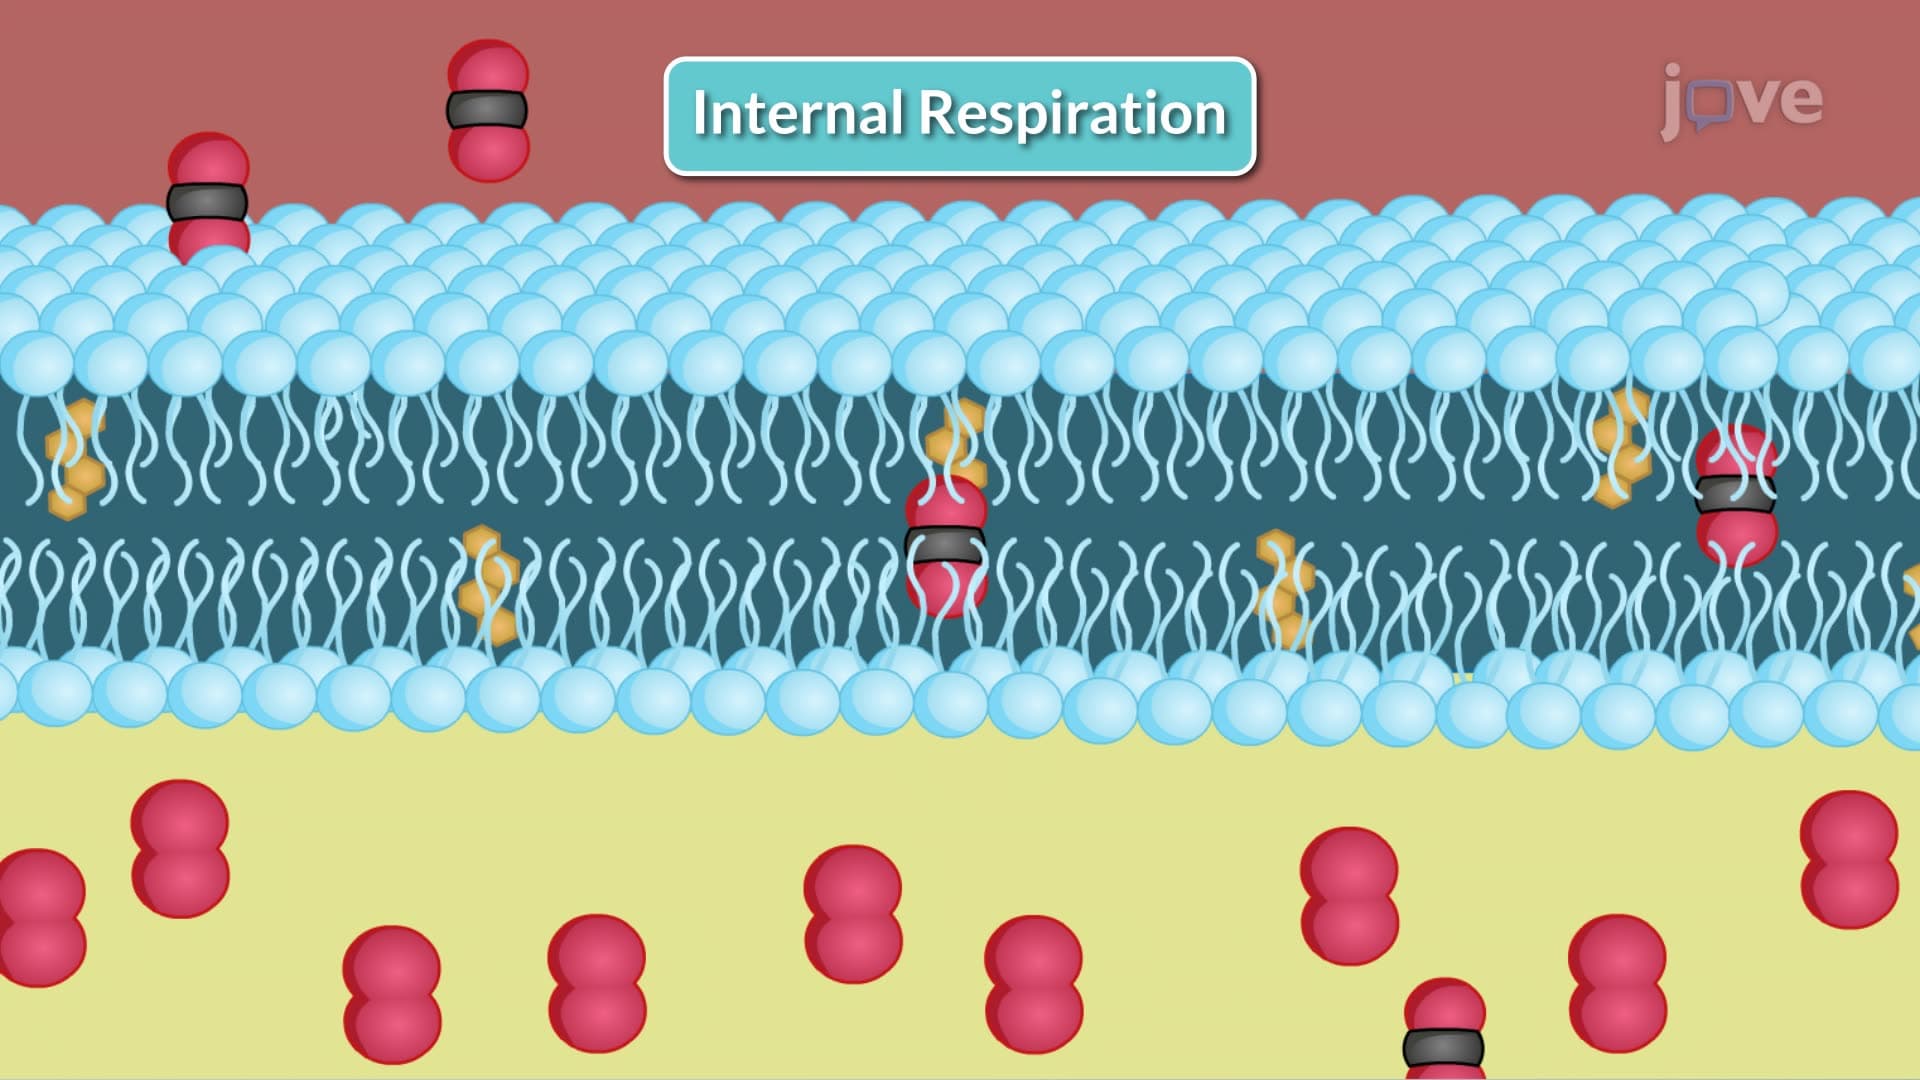
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves...