Related Experiment Video
Updated: Apr 14, 2026
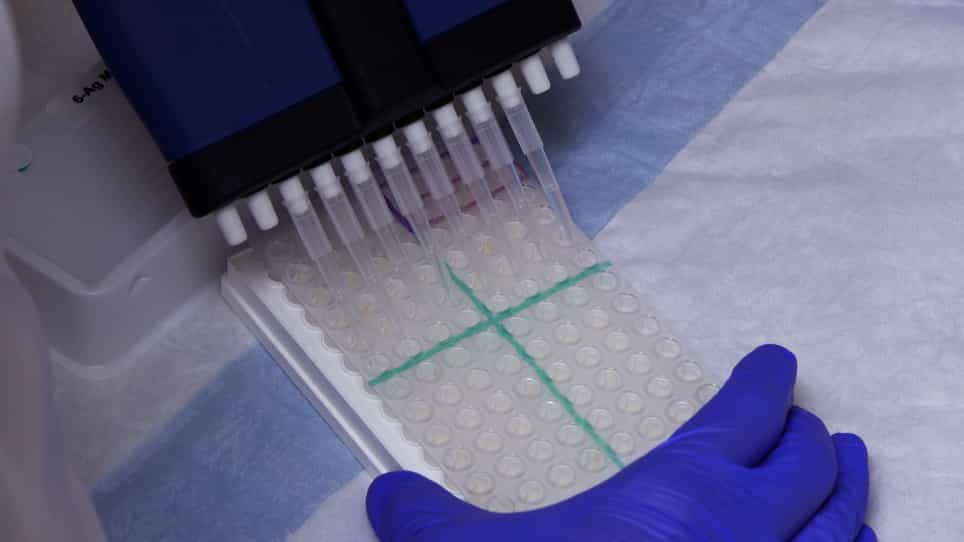

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Screening, diagnosis, and management of gestational diabetes mellitus
1Central City Community Health Center and the University of Utah, Salt Lake City, UT, USA.

Gestational diabetes mellitus (GDM) affects approximately 6% of pregnancies in the United States, and it is increasing in prevalence. Pregnant women without known diabetes mellitus should be screened for GDM after 24 weeks of gestation. Treatment of GDM results in a statistically significant decrease in the incidence of preeclampsia, shoulder dystocia, and macrosomia. Initial management includes glucose monitoring and lifestyle modifications. If glucose levels remain above target values, pharmacologic therapy with metformin, glyburide, or insulin should begin. Antenatal testing is customary for women requiring medications. Induction of labor should not occur before 39 weeks in women with GDM, unless glycemic control is poor or another indication for delivery is present. Unless otherwise indicated, scheduled cesarean delivery should be considered only in women with an estimated fetal weight greater than 4,500 g. Women with a history of GDM are at high risk of subsequently developing diabetes. These patients should be screened six to 12 weeks postpartum for persistently abnormal glucose metabolism, and should undergo screening for diabetes every three years thereafter.
Gestational diabetes mellitus (GDM) affects approximately 6% of pregnancies in the United States, and it is increasing in prevalence. Pregnant women without known diabetes mellitus should be screened for GDM after 24 weeks of gestation. Treatment of GDM results in a statistically significant decrease in the incidence of preeclampsia, shoulder dystocia, and macrosomia. Initial management includes glucose monitoring and lifestyle modifications. If glucose levels remain above target values, pharmacologic therapy with metformin, glyburide, or insulin should begin. Antenatal testing is customary for women requiring medications. Induction of labor should not occur before 39 weeks in women with GDM, unless glycemic control is poor or another indication for delivery is present. Unless otherwise indicated, scheduled cesarean delivery should be considered only in women with an estimated fetal weight greater than 4,500 g. Women with a history of GDM are at high risk of subsequently developing diabetes. These patients should be screened six to 12 weeks postpartum for persistently abnormal glucose metabolism, and should undergo screening for diabetes every three years thereafter.


Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:15
Hypoglycemia and Glucagon