Related Experiment Video
Updated: Apr 14, 2026
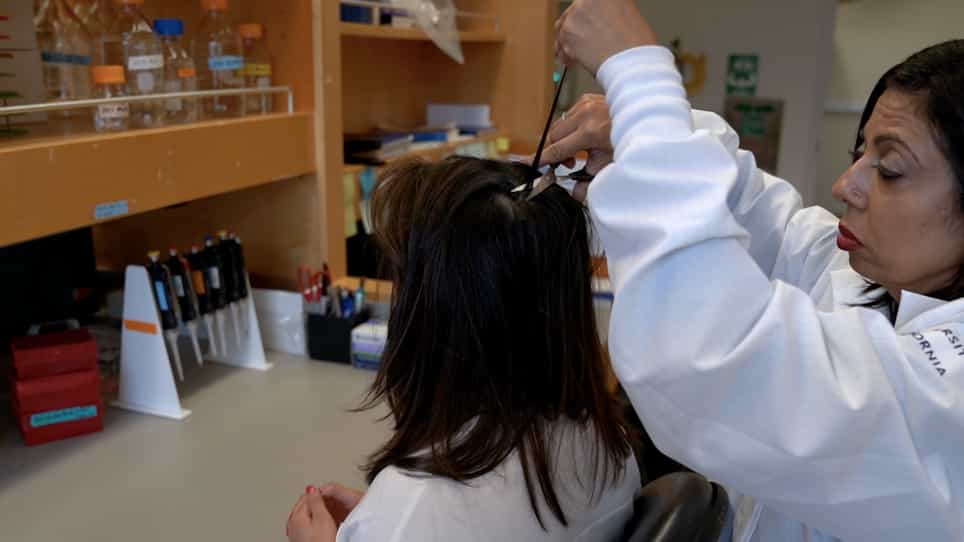
Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Barriers to adherence with tuberculosis contact investigation in six provinces of Vietnam: a nested case-control
Gregory James Fox1,2, Le Phuong Loan3, Nguyen Viet Nhung4
1Woolcock Institute of Medical Research, University of Sydney, 431 Glebe Point Road, Glebe, Sydney, 2037, Australia. gregory.fox@sydney.edu.au.

Background:
Close contacts of patients with tuberculosis (TB) have a substantial risk of developing the disease, particularly during the first year after exposure. Household contact investigation has recently been recommended as a strategy to enhance case detection in high-burden countries. However the barriers to its implementation in these settings remain poorly understood.
Methods:
A nested case-control study was conducted in Vietnam within the context of a large cluster randomised controlled trial of active screening for TB in household contacts of patients with pulmonary TB. The study population comprised contacts (and their index patients) from 12 Districts in six provinces throughout the country. Cases were contacts (and their index patients) that did not attend the scheduled screening appointment. Controls were those who did attend. We assessed relevant knowledge, attitudes and practices in cases and controls.
Results:
The acceptability of contact investigation was high among both cases (n = 109) and controls (n = 194). Both cases (47%) and controls (36%) commonly reported discrimination against people with TB. Cases were less likely than controls to understand that sharing sleeping quarters with a TB patient increased their risk of disease (OR 0.46, 0.27 - 0.78) or recognise TB as an infectious disease (OR 0.65, 0.39 - 1.08). A higher proportion of cases than controls held the mistaken traditional belief that a non-infectious form of TB caused the disease (OR 1.69, 1.02 - 2.78).
Conclusions:
The knowledge, attitudes and practices of contacts and TB patients influence their ongoing participation in contact investigation. TB case detection policies in high-prevalence settings can be strengthened by systematically evaluating and addressing locally important barriers to attendance.
Trial Registration:
Australian New Zealand Clinical Trials Registry, ACTRN12610000600044 .


Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...