Related Experiment Video
Updated: Apr 14, 2026
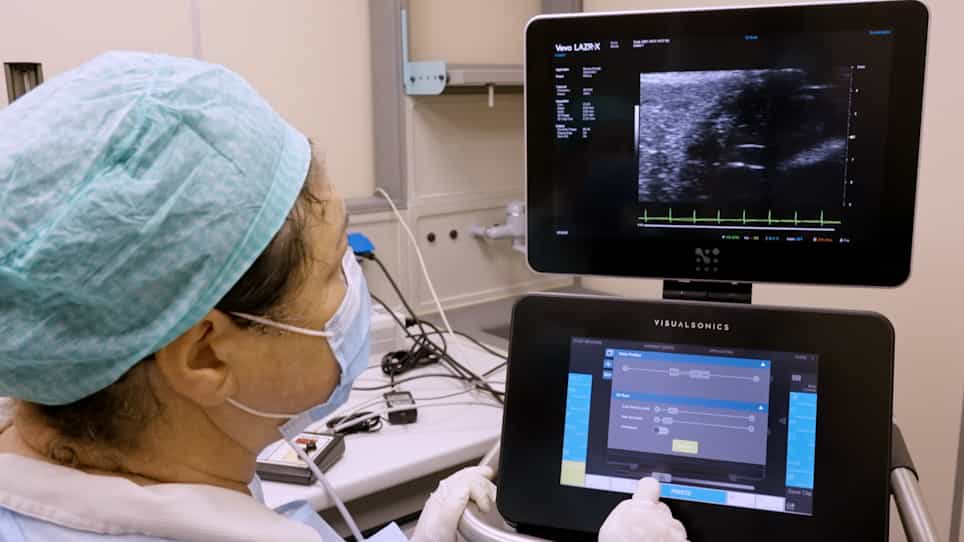
Analysis of Lymph Node Volume by Ultra-High-Frequency Ultrasound Imaging in the Braf/Pten Genetically Engineered Mouse Model of Melanoma
Published on: September 8, 2021
Corticosteroids augment BRAF inhibitor vemurafenib induced lymphopenia and risk of infection
Wiebke Sondermann1, Klaus G Griewank1, Bastian Schilling1
1Department of Dermatology, University Hospital Essen, West German Cancer Center, University Duisburg-Essen and the German Cancer Consortium (DKTK), Essen, Germany.

We have previously demonstrated an impact of the BRAF inhibitor vemurafenib on patient lymphocyte counts. In the current study, the extent to which concomitant use of corticosteroids in BRAF inhibitor treated patients affects lymphocyte counts and predisposes to infection was investigated. A cohort of 102 patients receiving either the selective BRAF inhibitor vemurafenib or dabrafenib was analyzed. The amount of patients receiving either medication with or without systemic corticosteroids (dexamethasone) was determined and lymphocyte counts before and under therapy assessed. Additionally, the number and severity of infections occurring in these groups was analyzed. Vemurafenib treatment led to a considerable decrease in lymphocyte cell counts, with 62.3% of patients having lymphopenia. Dabrafenib treated patients only rarely demonstrated lymphopenia (12.5%). Dexamethasone co-administration further diminished lymphocyte counts. Lymphopenias were observed in 84.6% of patients receiving vemurafenib and dexamethasone. In our cohort, infections were noted in 9 patients, 4 of these were severe and 2 eventually fatal. All 9 cases with infections demonstrated lymphopenia, 8 of these had received dexamethasone and 7 of these a therapy with vemurafenib. Our findings demonstrate a significant lymphopenia in patients treated with the BRAF inhibitor vemurafenib, which is further augmented by dexamethasone and predisposes to infection. If validated in other studies, risk of infection should be considered when applying corticosteroids in combination with BRAF inhibitors, in particular vemurafenib.
We have previously demonstrated an impact of the BRAF inhibitor vemurafenib on patient lymphocyte counts. In the current study, the extent to which concomitant use of corticosteroids in BRAF inhibitor treated patients affects lymphocyte counts and predisposes to infection was investigated. A cohort of 102 patients receiving either the selective BRAF inhibitor vemurafenib or dabrafenib was analyzed. The amount of patients receiving either medication with or without systemic corticosteroids (dexamethasone) was determined and lymphocyte counts before and under therapy assessed. Additionally, the number and severity of infections occurring in these groups was analyzed. Vemurafenib treatment led to a considerable decrease in lymphocyte cell counts, with 62.3% of patients having lymphopenia. Dabrafenib treated patients only rarely demonstrated lymphopenia (12.5%). Dexamethasone co-administration further diminished lymphocyte counts. Lymphopenias were observed in 84.6% of patients receiving vemurafenib and dexamethasone. In our cohort, infections were noted in 9 patients, 4 of these were severe and 2 eventually fatal. All 9 cases with infections demonstrated lymphopenia, 8 of these had received dexamethasone and 7 of these a therapy with vemurafenib. Our findings demonstrate a significant lymphopenia in patients treated with the BRAF inhibitor vemurafenib, which is further augmented by dexamethasone and predisposes to infection. If validated in other studies, risk of infection should be considered when applying corticosteroids in combination with BRAF inhibitors, in particular vemurafenib.


Related Concept Videos
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:24
Drugs for Treatment of Crohn's Disease in IBD Using Biologic Agents: Anti-TNF
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:27
Tumor Immunotherapy
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
02:49Cancer Therapies